



The timely article by Sequí-Canet et al highlights the potential harms of the common practice of placing a newborn in the sun behind a window at home to prevent or treat jaundice.1 The authors rightly acknowledged the important distinction between direct sunlight exposure and filtered sunlight phototherapy (FSPT), which blocks harmful ultraviolet rays while allowing therapeutic blue light through, thereby providing a safe and effective alternative for treating neonatal hyperbilirubinemia, especially in low-resource settings.2 This distinction is crucial because conventional electric-powered phototherapy is not accessible in many low-income countries due to unreliable power supplies in health care facilities. For example, at least 15% of health care facilities in sub-Saharan Africa and 12% in South Asia lack electricity, with even lower rates in rural areas.3 Moreover, only about half of the hospitals in sub-Saharan Africa have a reliable power supply.
Most clinical guidelines for neonatal hyperbilirubinemia, including the widely referenced guidelines from the American Academy of Pediatrics (AAP), acknowledge that direct exposure to sunlight decreases total serum or plasma bilirubin (TSB) concentrations, but do not consider sunlight a reliable therapy due to the practical difficulties involved in safely exposing infants to sunlight while preventing sunburn and dehydration.4 Direct sunlight is therefore not recommended, consistent with the findings of Sequí-Canet et al.1 However, AAP guidelines acknowledge the emerging evidence on the utility of FSPT to address safety concerns related to hyperthermia, sunburn, and dehydration in resource-constrained settings where electric-powered phototherapy is not readily available.4
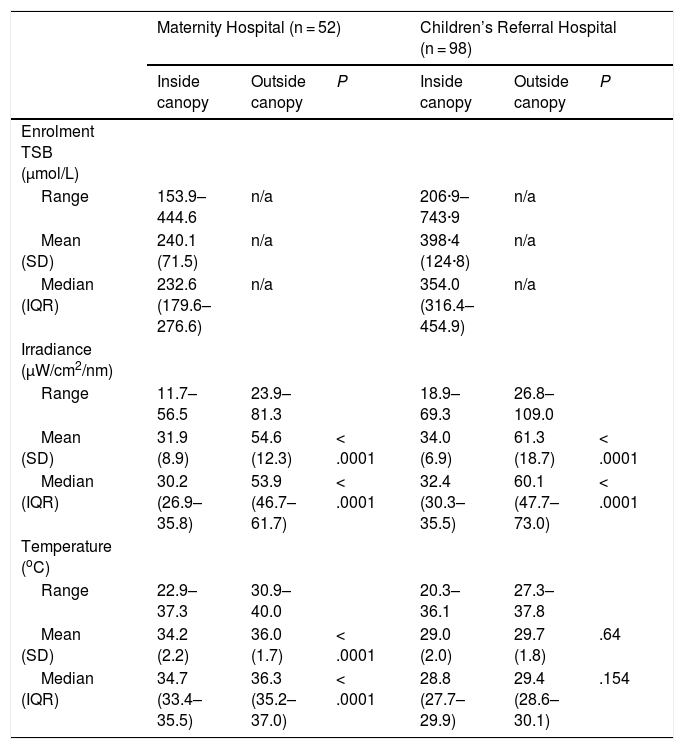
A secondary analysis of two randomized controlled trials of filtered sunlight phototherapy for newborns with severe to hazardous hyperbilirubinemia (153.9–743.9 µmol/L), with or without acute bilirubin encephalopathy,2 is presented in Table 1 and demonstrates how the therapeutic benefits of sunlight exposure can be safely and effectively harnessed. The trials were conducted in a maternity hospital and a children’s referral hospital. Filtered sunlight phototherapy was delivered inside a custom-made canopy that can accommodate up to six mother-infant pairs at any time. A comparison of irradiance and temperature inside and outside the canopy shows that the filter not only blocks UV radiation but also significantly reduces irradiance and temperature within safe, therapeutic ranges.
Environmental data inside and outside FSPT canopies for infants with severe hyperbilirubinemia.
| Maternity Hospital (n = 52) | Children’s Referral Hospital (n = 98) | |||||
|---|---|---|---|---|---|---|
| Inside canopy | Outside canopy | P | Inside canopy | Outside canopy | P | |
| Enrolment TSB (µmol/L) | ||||||
| Range | 153.9–444.6 | n/a | 206·9–743·9 | n/a | ||
| Mean (SD) | 240.1 (71.5) | n/a | 398·4 (124·8) | n/a | ||
| Median (IQR) | 232.6 (179.6–276.6) | n/a | 354.0 (316.4–454.9) | n/a | ||
| Irradiance (μW/cm2/nm) | ||||||
| Range | 11.7–56.5 | 23.9–81.3 | 18.9–69.3 | 26.8–109.0 | ||
| Mean (SD) | 31.9 (8.9) | 54.6 (12.3) | < .0001 | 34.0 (6.9) | 61.3 (18.7) | < .0001 |
| Median (IQR) | 30.2 (26.9–35.8) | 53.9 (46.7–61.7) | < .0001 | 32.4 (30.3–35.5) | 60.1 (47.7–73.0) | < .0001 |
| Temperature (oC) | ||||||
| Range | 22.9–37.3 | 30.9–40.0 | 20.3–36.1 | 27.3–37.8 | ||
| Mean (SD) | 34.2 (2.2) | 36.0 (1.7) | < .0001 | 29.0 (2.0) | 29.7 (1.8) | .64 |
| Median (IQR) | 34.7 (33.4–35.5) | 36.3 (35.2–37.0) | < .0001 | 28.8 (27.7–29.9) | 29.4 (28.6–30.1) | .154 |
Abbreviations: FSPT, filtered sunlight phototherapy; n/a, not applicable; TSB, total serum or plasma bilirubin.
TSB was measured using a BR2 Bilirubin Stat-Analyzer (Advanced Instruments; Norwood, MA, USA). Indoor and outdoor temperatures and irradiance were recorded daily every 30 min between 9 am and 5 pm. Irradiance was measured with a BiliBlanket Light Meter II (GE HealthCare, Chicago, IL, USA). The maternity hospital data reflect the profile of hyperbilirubinemia among newborns in the first 48 h from birth prior to discharge, while the children’s hospital data refer primarily to newborns readmitted due to hyperbilirubinemia.
Despite the recommendations by various clinical guidelines, the practice of placing newborns under the early morning sun outdoors or inside the home behind the window to prevent or treat severe hyperbilirubinemia persists worldwide, with or without advice from health workers. The dilemma and ethical challenge for clinicians is what to do when conventional electric phototherapy is not available, even in remote settings in some developed countries. Lack of timely and effective phototherapy places a newborn with severe hyperbilirubinemia at risk of premature death or long-term neurologic damage and needs to be balanced with the potential harms/benefits of sunlight exposure. The choice is not between sunlight exposure and conventional phototherapy but between community-based FSPT and direct sunlight exposure or exposure through residential glazing, particularly where reliable electricity cannot be guaranteed. Practice guidelines must clarify and reflect these realities to curtail avoidable adverse outcomes of severe neonatal hyperbilirubinemia in any setting.
Author contributionsAll authors contributed equally to this letter.
FundingNone.
The authors declare no competing interests.



