




Complementary feeding (CF) or beikost is defined as the introduction of liquid, semisolid or solid foods other than breast milk or formula in the infant’s diet.1,2 Starting at a certain stage when the kidneys, immune system, gastrointestinal tract, and nervous system of the baby have matured to a certain extent—approximately between 4 and 6 months—breast milk, or formula, as a substitute, may no longer be sufficient to meet the nutritional needs of the infant. Therefore, other foods need to be introduced to provide the essential nutrients required for adequate growth and development.3 The best-known and most widely used method is the standard or traditional approach (using purees and baby food), which is implemented directly by parents or caregivers in the early stages of introducing solid foods. A new CF method known as baby-led weaning (BLW), which was developed in England by Gill Rapley, emerged in 2008. It is an alternative approach based on letting infants feed themselves with their hands rather than being fed by caregivers, allowing them to experience a broader range of textures and foods and promoting the development of motor skills.4,5 In theory, this could promote the development of healthier dietary habits, contribute to the prevention of childhood obesity, and facilitate and improve motor skill acquisition.6 This method, however, raises concerns among some health care professionals, parents, and caregivers, particularly regarding the risk of choking, insufficient intake of iron and certain essential nutrients, changes in the gut microbiota, and potential growth faltering.7 This motivated a modification to the method in 2015, resulting in an approach known as baby-led introduction to solids (BLISS).8 It has been proposed as a safer method, addressing the potential risks of BLW (by offering foods with optimal texture and size, fewer foods considered to pose a high choking risk, and more foods with a higher energy density and iron content).9 These methods have spread worldwide, and are most prevalent in the United Kingdom and New Zealand (30%), with a low prevalence in Spain as of 2020 (2%),10 although it is expected to increase.
The various CF methods used in recent years and their effects on health are of great interest to health care professionals, caregivers, and parents; therefore, comprehensive research should be promoted to enable evidence-based decision-making. For this reason, we conducted this review to provide an updated summary of the current evidence on the risks and health effects of different CF methods.
Material and methodsTo map the available evidence, we conducted a scoping review in accordance with the methodological guidelines of the Joanna Briggs Institute (JBI) and the Preferred Reporting Items for Systematic Reviews and Meta-Analyses extension for Scoping Reviews (PRISMA-ScR). We searched the PubMed database for meta-analyses, systematic reviews, clinical trials, observational studies, and literature review articles published over the past 11 years (December 31, 2014 to December 31, 2025) in English or Spanish. The following search terms were used: “Baby-Led Weaning” OR “BLW” OR “Baby-Led” OR “BLISS” OR “Baby-Led Introduction to Solids,” and the following filters were applied: English, Spanish, Humans, Child: birth-18 years. We also included relevant sources that were not obtained directly from that search, such as clinical practice guidelines and institutional recommendations. These documents were deliberately selected for their clinical relevance to enrich the background and discussion of the review. Two reviewers conducted the search and selection of sources independently to control for potential biases in the selection and data extraction process, and discrepancies were thereafter resolved; both reviewers, together with the other members of the Nutrition Committee of the Asociación Española de Pediatría (AEP), subsequently reached a consensus.
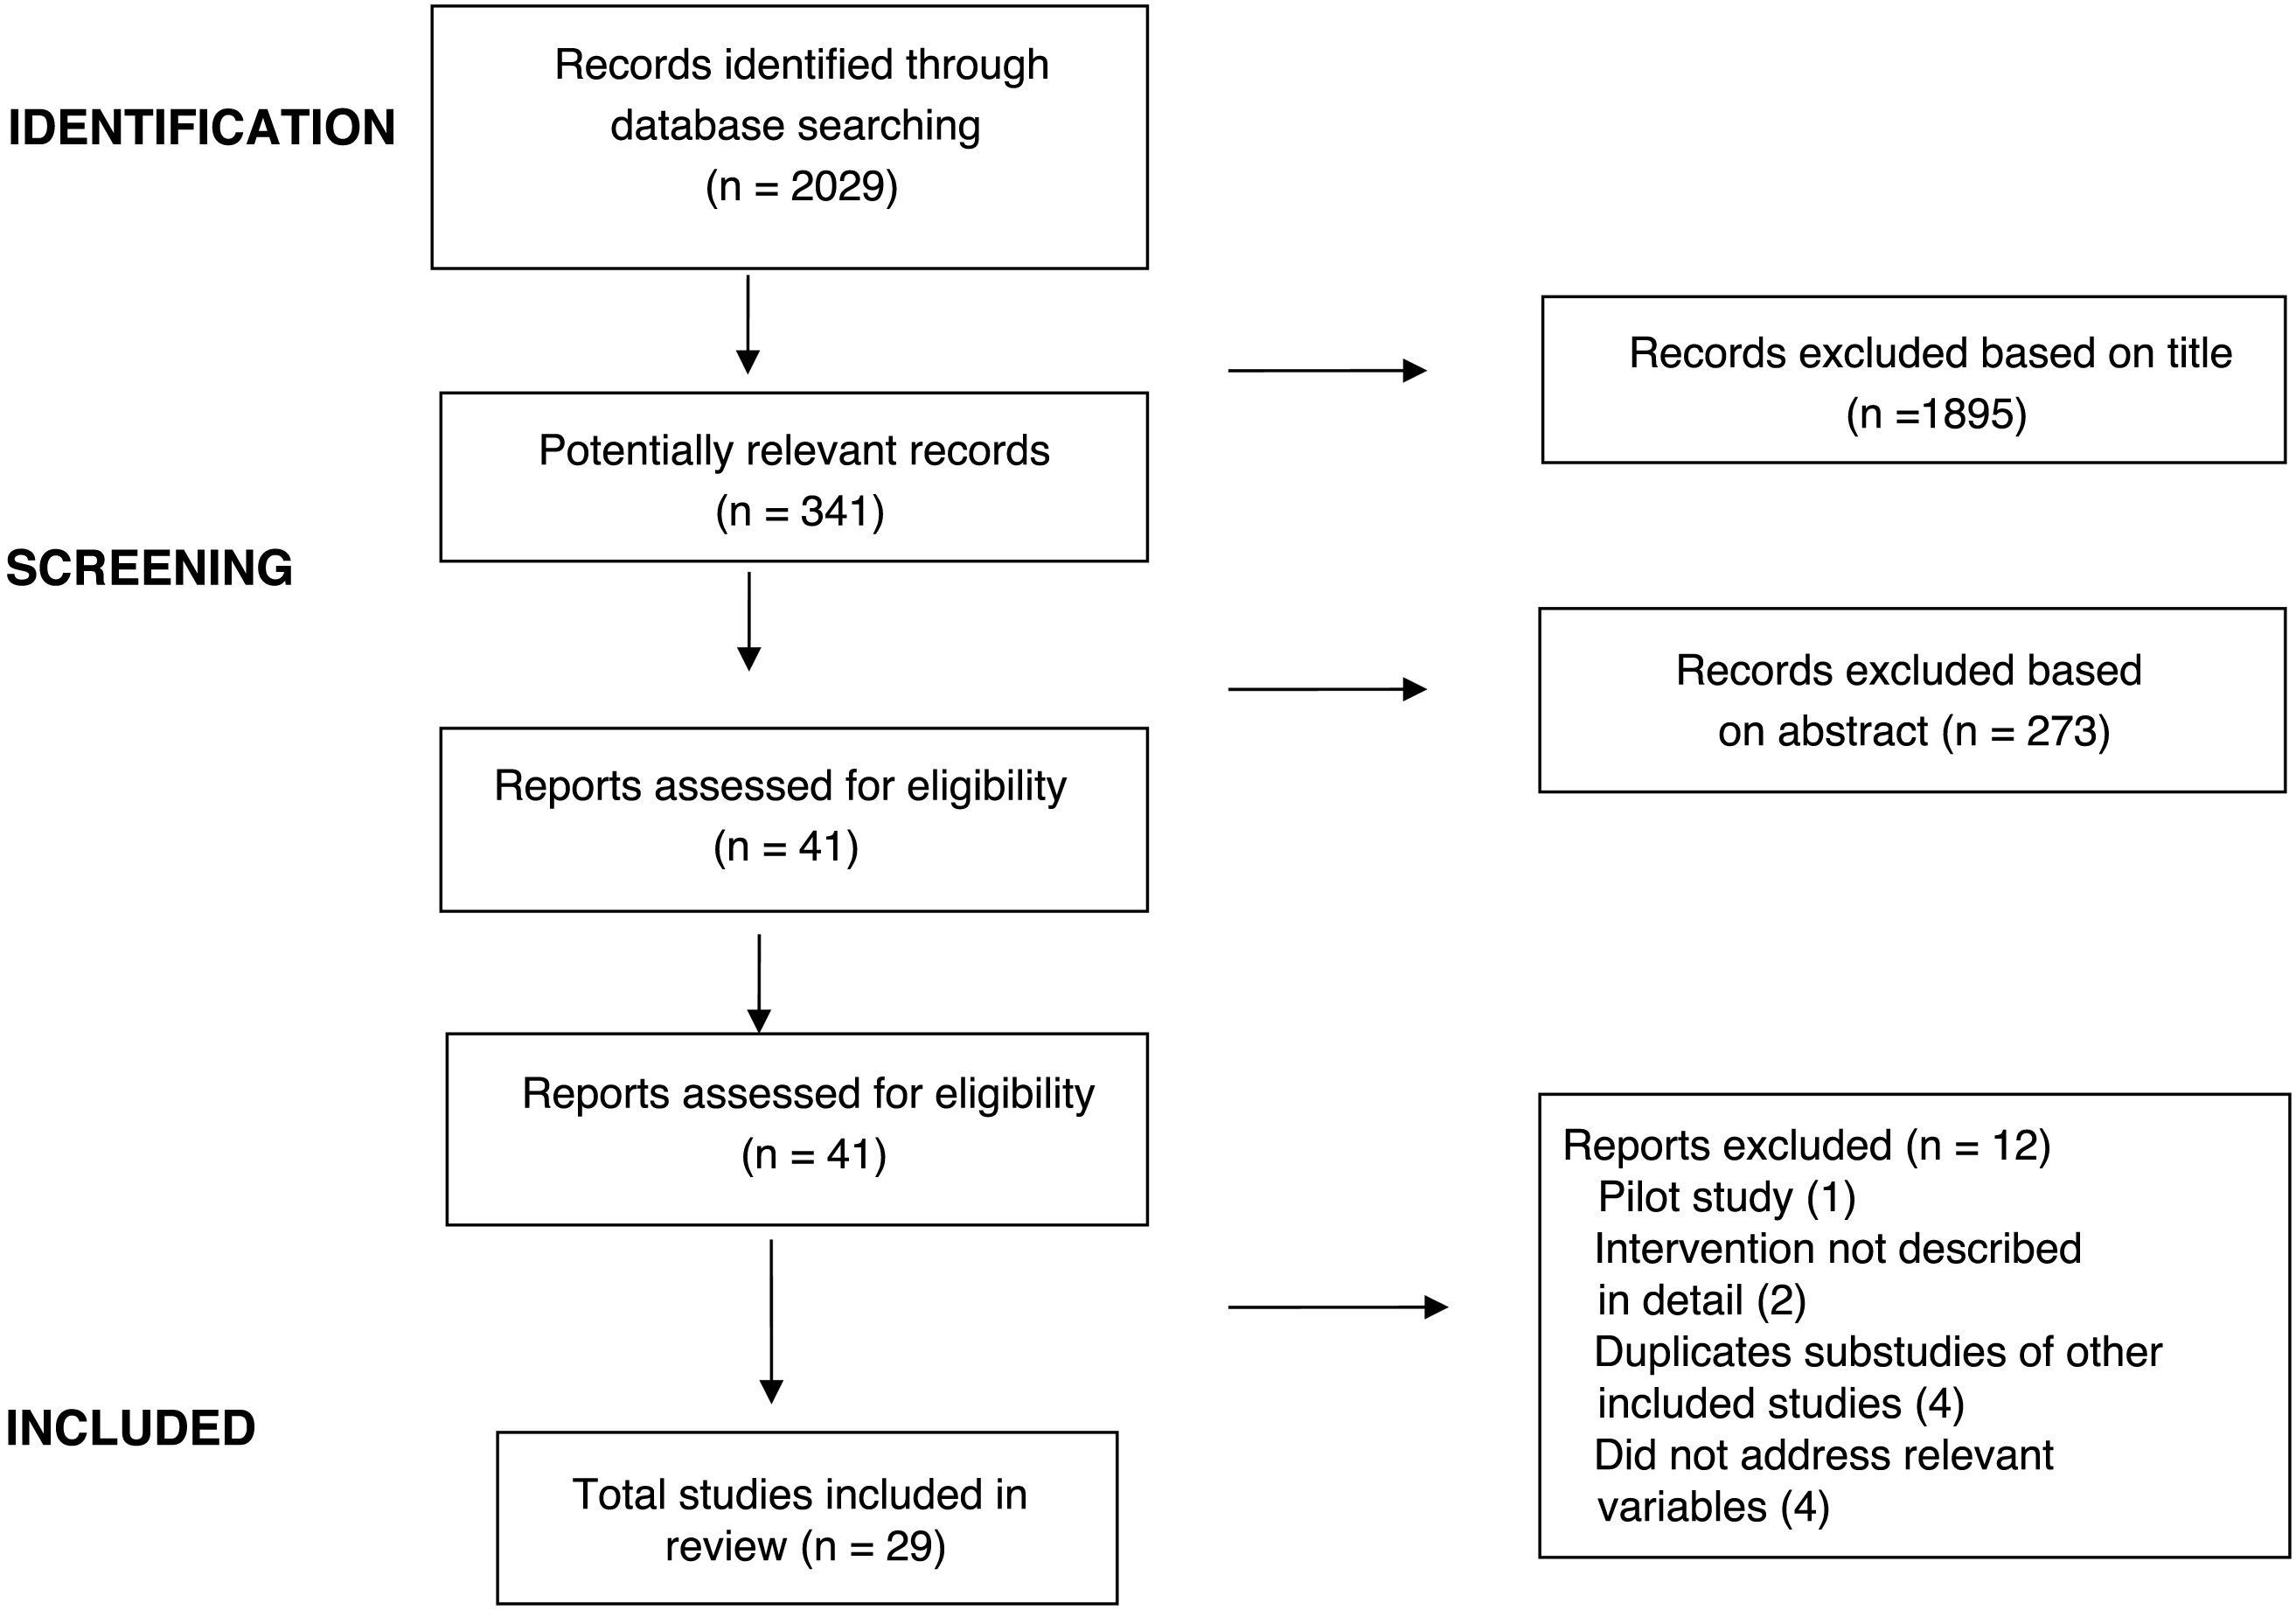
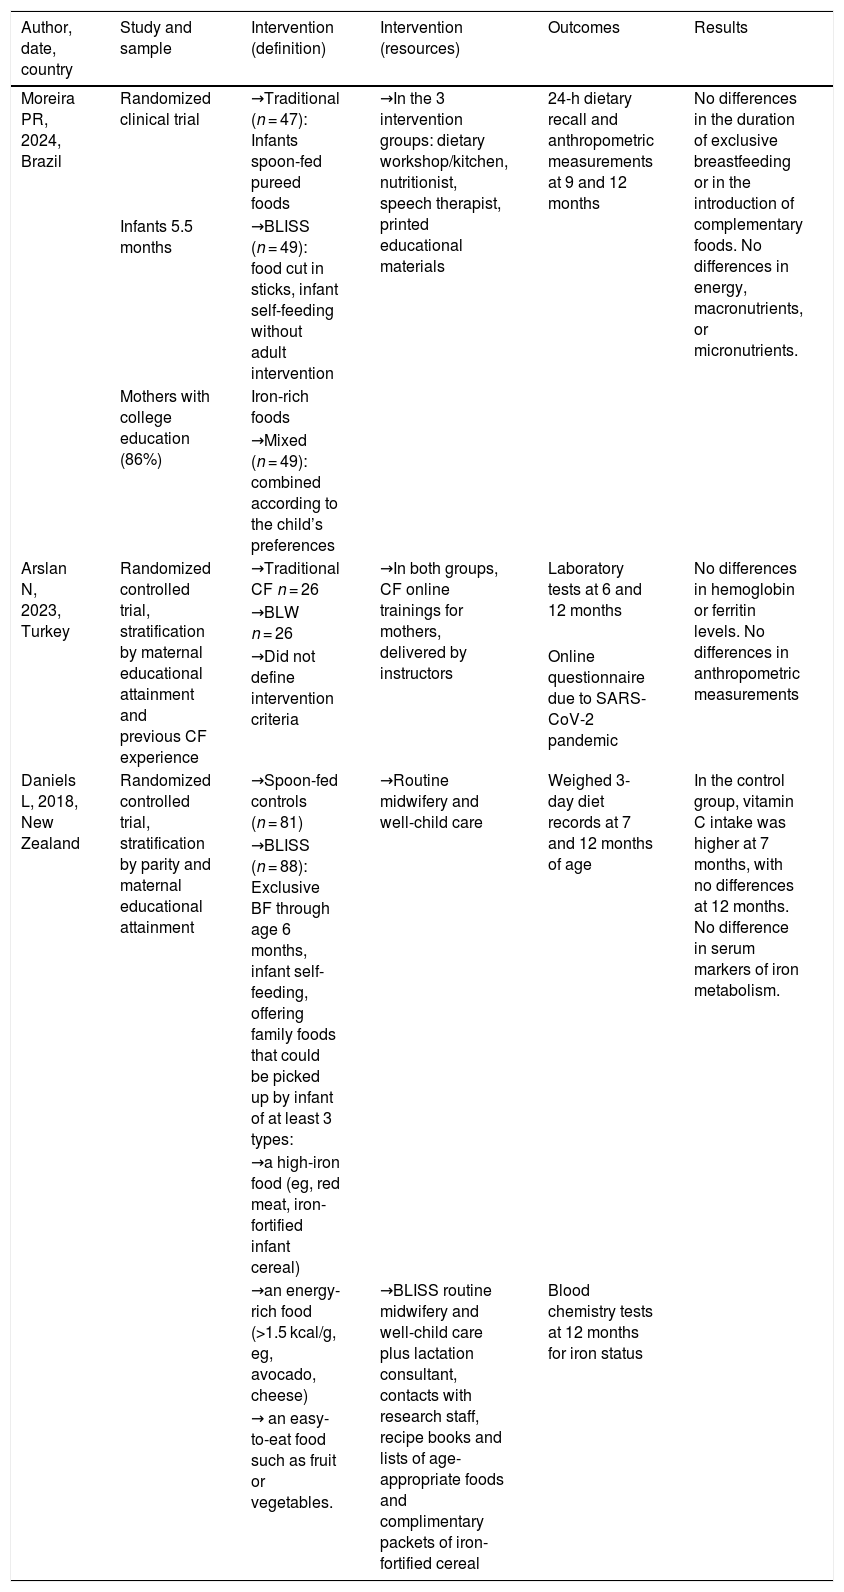
ResultsA total of 2209 articles were evaluated, of which 29 were ultimately selected: 10 clinical trials, 10 observational studies, 7 reviews (4 systematic and 5 narrative), and 2 meta-analyses (Appendix B, Supplementary material 1). Only studies whose results focused on the safety and efficacy of the specific type of CF were included; duplicates and studies that did not clearly define the types of CF or were pilot studies were excluded. Fig. 1 shows the flow diagram for the literature review, which conformed to the guidelines of the PRISMA statement (Appendix B, Supplementary material 2). Table 1 summarizes the results of clinical trials concerning the efficacy of the CF methods.

Characteristics of the included clinical trials on different complementary feeding methods.
| Author, date, country | Study and sample | Intervention (definition) | Intervention (resources) | Outcomes | Results |
|---|---|---|---|---|---|
| Moreira PR, 2024, Brazil | Randomized clinical trial | →Traditional (n = 47): Infants spoon-fed pureed foods | →In the 3 intervention groups: dietary workshop/kitchen, nutritionist, speech therapist, printed educational materials | 24-h dietary recall and anthropometric measurements at 9 and 12 months | No differences in the duration of exclusive breastfeeding or in the introduction of complementary foods. No differences in energy, macronutrients, or micronutrients. |
| Infants 5.5 months | →BLISS (n = 49): food cut in sticks, infant self-feeding without adult intervention | ||||
| Mothers with college education (86%) | Iron-rich foods | ||||
| →Mixed (n = 49): combined according to the child’s preferences | |||||
| Arslan N, 2023, Turkey | Randomized controlled trial, stratification by maternal educational attainment and previous CF experience | →Traditional CF n = 26 | →In both groups, CF online trainings for mothers, delivered by instructors | Laboratory tests at 6 and 12 months | No differences in hemoglobin or ferritin levels. No differences in anthropometric measurements |
| →BLW n = 26 | |||||
| →Did not define intervention criteria | Online questionnaire due to SARS-CoV-2 pandemic | ||||
| Daniels L, 2018, New Zealand | Randomized controlled trial, stratification by parity and maternal educational attainment | →Spoon-fed controls (n = 81) | →Routine midwifery and well-child care | Weighed 3-day diet records at 7 and 12 months of age | In the control group, vitamin C intake was higher at 7 months, with no differences at 12 months. No difference in serum markers of iron metabolism. |
| →BLISS (n = 88): Exclusive BF through age 6 months, infant self-feeding, offering family foods that could be picked up by infant of at least 3 types: | |||||
| →a high-iron food (eg, red meat, iron-fortified infant cereal) | |||||
| →an energy-rich food (>1.5 kcal/g, eg, avocado, cheese) | →BLISS routine midwifery and well-child care plus lactation consultant, contacts with research staff, recipe books and lists of age-appropriate foods and complimentary packets of iron-fortified cereal | Blood chemistry tests at 12 months for iron status | |||
| → an easy-to-eat food such as fruit or vegetables. |
BF, breastfeeding; BLISS, baby-led introduction to solids; BLW, baby-led-weaning; CF, complementary feeding.
The progressive introduction of different textures (purees, semisolid foods, and solid foods that are easy to chew), which is the traditional approach led by the caregivers, theoretically offers several advantages. One of them is the lower risk of nutritional deficiencies.11 On the other hand, there is evidence that suggests that in this caregiver-led feeding approach, infants consume a greater amount of fortified cereals (rich in certain micronutrients), which are not typically used in other methods, such as BLW.3,12 In addition, caregivers typically try to ensure a minimum intake by feeding infants fixed amounts, without prioritizing the infant’s satiety cues.13 Observational studies have found higher intakes of nutrients such as zinc, iodine, and vitamins B12 and D compared to the other CF methods.12 However, other studies, including clinical trials, which primarily compared the traditional approach to BLISS, found no differences in either total energy intake or the macronutrient and micronutrient distributions.7
As with other micronutrients, it appears that iron intake is higher with the traditional approach compared to alternative CF methods.3,9,12,13 This could be explained by the fact that in the traditional CF approach, babies consume more meat and other foods fortified with iron, like cereal. However, the literature does not evince differences in the intake of these nutrients based on the CF method, and there is heterogeneity in reported blood ferritin levels, suggesting that other factors may be at play.5,13–15
On the other hand, it appears that traditionally fed infants tend to consume larger amounts of food, particularly of protein, and this could be associated with a higher risk of obesity in the long term.3 There is controversy regarding the impact of the CF method on body composition.5,14–16 In fact, some authors point out that children seem to consume more saturated fat with methods like BLW, which could be related to the offering of foods that are easy to chew or process.12
As regards neurodevelopment, and considering the characteristics of this CF method, which primarily involves passive feeding by caregivers, it would be reasonable to assume that skills such as chewing/swallowing coordination, acceptance of textures, and other aspects would be acquired later compared to other methods where the child is more independent and actively involved.4,9 However, given that each infant has a different level of maturity, and within the limits of what is considered normal, it is important to assess chewing, coordination of swallowing, food handling, and overall neurodevelopment. These aspects will determine the pace at which the child progresses from drinking fluids and pureed foods to solid foods. The use of the traditional method should not delay the introduction of different textures or foods, and repeated exposure to them should be provided to gradually advance this process according to the skills of the child.17 Educating parents on this subject is essential; the pediatrician must know and explain to parents how to gradually introduce different textures and when to do so, the appropriate portion sizes, how to tell when the child has eaten enough, and the importance of this process for establishing healthy habits and the future wellbeing of the child.
Baby-led weaningIn the BLW method, the baby sets the pace for feeding and is allowed to choose among different foods and textures.3 The method is based on offering foods that are easy to grasp (chopped foods, finger foods) to encourage self-feeding and help children recognize when they are full.18 Parents or caregivers decide what to offer, but the infant chooses the foods to consume among those available as well as the amounts. As is the case with any method, the offered foods should be healthy and varied.
Semi-solid or solid foods with textures that the infant can handle should be chosen according to the infant’s maturity and preferences to ensure adequate intake in terms of both quantity and quality. The BLW method encourages self-feeding, which infants start doing with their own hands, eventually progressing to the correct use of cutlery or other utensils. Several studies suggest that BLW promotes neurodevelopment, as it affords babies greater autonomy, allowing them to decide how to manipulate or eat foods and to control their intake.4,9 This approach may also promote more appropriate behavior at mealtimes, with a lower frequency of food fussiness or picky eating, or better satiety responsiveness.2,19,20 Before initiating CF with this approach, it is essential to ensure that the baby can hold his or her head, has a good grip, and can sit up unsupported, as well as having adequate control of chewing and especially swallowing.8,9 In this regard, studies comparing different methods have not yielded evidence that would allow for an assessment of differences in motor skill development based on the selected approach, as they are based on subjective data collection methods, such as surveys of mothers.4
Families who choose this method are often more aware of the importance of teaching healthy habits and are more likely to exclusively breastfeed infants in the first months of life12 and, later on, to offer more fruits and vegetables, and reduce the intake of refined sugars or processed foods. Furthermore, the emphasis on infant exploration and autonomy in BLW also appears to favor the intake of whole foods, since infants tend to select and successfully self-feed on foods that are visually appealing (e.g., more colorful fruits) and that have a texture they are able to grip and bring to their mouth on their own.4 However, there is a risk that the intake of fruits and vegetables may replace the consumption of iron-rich foods, such as those of animal origin.9 It should be noted that the choice of these new CF approaches may be associated with the consumption of vegetarian and vegan diets, so that certain observed micronutrient deficiencies may be associated with this choice.1,21 Therefore, in these cases, supervision by a pediatrician is necessary to avoid these risks, which are not directly associated with the method. Thus, the health care professional involved in the process of introducing complementary foods must have adequate and updated information to provide guidance for the different approaches the family may choose.
Another factor to consider is that, since the infant is self-feeding, he or she may get more tired or frustrated (especially in infants with motor skills below the average for age), which could result in a lower energy intake,22 spitting, or gagging.20 In fact, one of the biggest concerns regarding baby-led weaning is the risk of a diet deficient in certain nutrients or a deficient energy intake. Some studies have reported lower levels of hemoglobin, ferritin, and serum transferrin in infants with the use of BLW compared to traditional weaning,1 although with contradictory results, as we noted above.14 Deficiencies in iron or other nutrients, like zinc or vitamin B12, are likely due to an insufficient overall dietary intake3,9,12 or failure to offer a broad variety of foods or foods containing those nutrients, which, once again, are not necessarily related to the chosen method.
One of the greatest fears parents and caregivers have about this method is the potential risk of choking or asphyxiation to the infant from self-feeding solid foods (especially raw fruits and vegetables, such as apples or grapes, or whole nuts).23 However, the available evidence, although based on subjective tools such as questionnaires, seems to indicate that BLW does not pose a significant risk.6,20 The studies included in a recent systematic review did not find significant differences in the risk of choking in babies in relation to the use of traditional CF, BLW, or BLISS.24 This risk appears to be related mainly to how well the infant manages different textures, and to parental knowledge of how to minimize the risk (offering foods in sizes and shapes appropriate for the age of the baby, avoiding hard, round, or sticky foods that could cause obstruction, constant supervision while the infant eats, and ensuring that the infant eats while seated and free of distractions).25
Baby-led introduction to solidsThe BLISS method is a version of complementary feeding (CF) based on baby-led weaning (BLW) that was designed to address the potential risks for infants when they begin complementary feeding (choking, iron deficiency, and reduced food intake) and was evaluated, at least initially, through clinical trials.8,9 The characteristics of this method are: (a) choosing foods with the right texture and shape (soft, easy to chew, and in pieces that can be grasped by the infant, such as sticks or strips); (b) ensuring the intake of foods rich in iron (chicken, red meat, fish) and with an adequate energy content (providing more than 1.5 kcal/g), and (c) avoiding foods associated with a high risk for choking (apples and raw vegetables, nuts, etc).9
The authors who propose the BLISS method indicated that the protein intake using this method is 14.7%, meeting the recommended level, compared to BLW, which only reaches 10.8%.8 However, other authors26 have reported a decreased intake of lipids with the BLISS method (7%) on infants aged 12 months or consumption of an average of 2 more fruit or vegetable portions a day compared to BLW.12,27,28 Yet others have found that the gut microbiota is less diverse in infants fed with the BLISS method compared to traditional CF, in association with a lower intake of fiber, fruit and vegetables.29–31 Foods that are easier to manipulate are not necessarily healthier, and this could explain the differences between studies, as the inclusion of fruits and vegetables is usually guaranteed in the purees fed to the infant in traditional caregiver-led CF, at least in the first year. However, this issue has yet to be clarified; a recent clinical trial found no differences in macronutrient or micronutrient intake or in other variables, such as BMI, based on the use of BLISS versus other CF approaches,32 in agreement with the original clinical trials,8,9 so the factors that give rise to these differences may be extrinsic to the methods themselves.33,34
In relation to iron intake or serum iron test values, there is no evidence of differences between BLW and BLISS. However, the consumption of foods rich in iron,9,26 zinc, vitamin C and vitamin B12 seems to be higher in children fed with the BLISS approach compared to BLW, and, by ensuring intake of these nutrients, its health benefits may be greater. However, some studies have found a higher intake of added sugars and sodium in association with traditional CF and BLISS compared to BLW.26 The higher salt intake in the BLISS method appears to be due to greater consumption of high-salt dairy products and processed meats, as well as family foods, which were consumed in greater quantities in this modified version of baby-led weaning. In fact, there were no significant differences between parental responses in each group regarding the use of added salt.35
Motor skill outcomes are similar in BLISS and BLW, as they both promote infant self-feeding. However, by promoting a higher iron intake, the BLISS approach could contribute to the prevention of anemia and, therefore, have a protective effect in long-term neurodevelopment.36,37
With regard to risks, as we already noted, this modification of the BLW method aims to reduce the potential risk of choking by preventing access to foods that pose a higher risk. In fact, it has been reported that in BLW infants are given, on average, 3.24 times more foods that pose a high risk of choking compared to BLISS,9 although this result probably depends more on parental knowledge and caution and has not been confirmed in clinical trials.24,38 Specifically, the BLISS method proposes a list of foods to avoid because they are considered high-risk (raw vegetables, raw fruit, rice crackers, whole nuts, cherries, grapes, peas, etc). It also emphasizes the need to strictly control the size and texture of offered foods (safe and easy to handle, finger foods or food cut in strips to facilitate grasping) and to educate caregivers on how to distinguish the physiological gag reflex (gagging) from an actual choking episode. Based on the results described above, it can be concluded that the theoretical benefits and risks of the new CF methods compared to the traditional method are not yet supported by robust scientific evidence. There was significant heterogeneity in study methodology and limited information on the intervention used in some studies. This made it difficult to compare results and draw accurate conclusions.
Since 2008, when the BLW method first began to be mentioned in the medical literature, the number of publications on the subject has grown exponentially. In the early years, research primarily consisted of observational studies. In 2015, BLISS was introduced with the aim of addressing some of the concerns identified in certain early studies on BLW, particularly regarding safety and the challenges involved in meeting micronutrient and macronutrient requirements. Since then, in addition to observational studies, several clinical trials have been published comparing these methods to traditional CF. In general, these trials had a structured design, and the intervention groups typically benefited from a multidisciplinary care team (dietitians, speech-language pathologists, pediatricians, lactation consultants, etc), with additional support such as home visits, informational materials, and, in some cases, donations of fortified foods. In some cases, these conditions also extended to the traditional CF group, giving rise to an ideal study environment that does not always reflect everyday reality, which limits the external validity of the findings. On the other hand, some of them were conducted in countries such as the United States, Canada, the United Kingdom, New Zealand,16 Brazil,32 or Turkey,5 that is, in very different cultural contexts which are not always comparable to Spain. Therefore, it is essential to interpret the results with caution and to avoid inappropriate generalization.39,40
In addition, there is significant conceptual and methodological overlap between BLW and its variant, BLISS, which complicates the interpretation of the available evidence. Although the literature formally defines BLISS as a modification designed to address the risks of conventional BLW (through specific guidelines regarding iron intake and choking prevention),8,9 both approaches share the core principle of self-feeding guided by the infant. The analysis of the included studies revealed that practically all of the data on the BLISS method come from a single randomized controlled trial or refer to modified versions of it.8,9,14,16,26,28 In contrast, the evidence on BLW primarily comes from observational studies. Therefore, it is methodologically challenging to determine whether the clinical effects of the BLISS method can be attributed to the method itself or simply reflect the results of implementing BLW with a higher level of education, supervision, and nutritional guidance—so that perhaps both should be integrated as parts of the same process.
For all these reasons, the available evidence has inherent methodological limitations that call for caution when interpreting the results. In particular, we ought to underscore the predominance of observational studies based on self-administered questionnaires, small sample sizes in various studies, and the presence of sociocultural and selection biases. Furthermore, the profile of participating families is often heterogeneously associated with a higher socioeconomic status and educational attainment, which act as confounders. Finally, it is extremely difficult to objectively assess critical events such as choking, the measurement of which depends on the perception and recall of caregivers, with the risk that the gag reflex may even be confused with actual choking.
In conclusion, at this time, there is no evidence that methods based on BLW and BLISS offer any advantages over traditional CF methods based on the progressive introduction of different food textures. All of these methods provide benefits once the child reaches the age when breast milk should be gradually replaced by other foods, improving the diversity of the microbiota and preventing nutritional deficiencies. In light of these results, the Committee on Breastfeeding and Nutrition of the AEP proposes that CF recommendations be individualized, as opposed to a one-size-fits-all approach, and that the choice between traditional CF and BLW-BLISS be tailored to the needs of the baby and the family, always ensuring a varied, balanced, and safe diet. Pediatricians and other professionals involved in the CF process should be familiar with these methods in order to provide appropriate guidance based on the best available scientific evidence for each case.
The following are Supplementary data to this article:





