



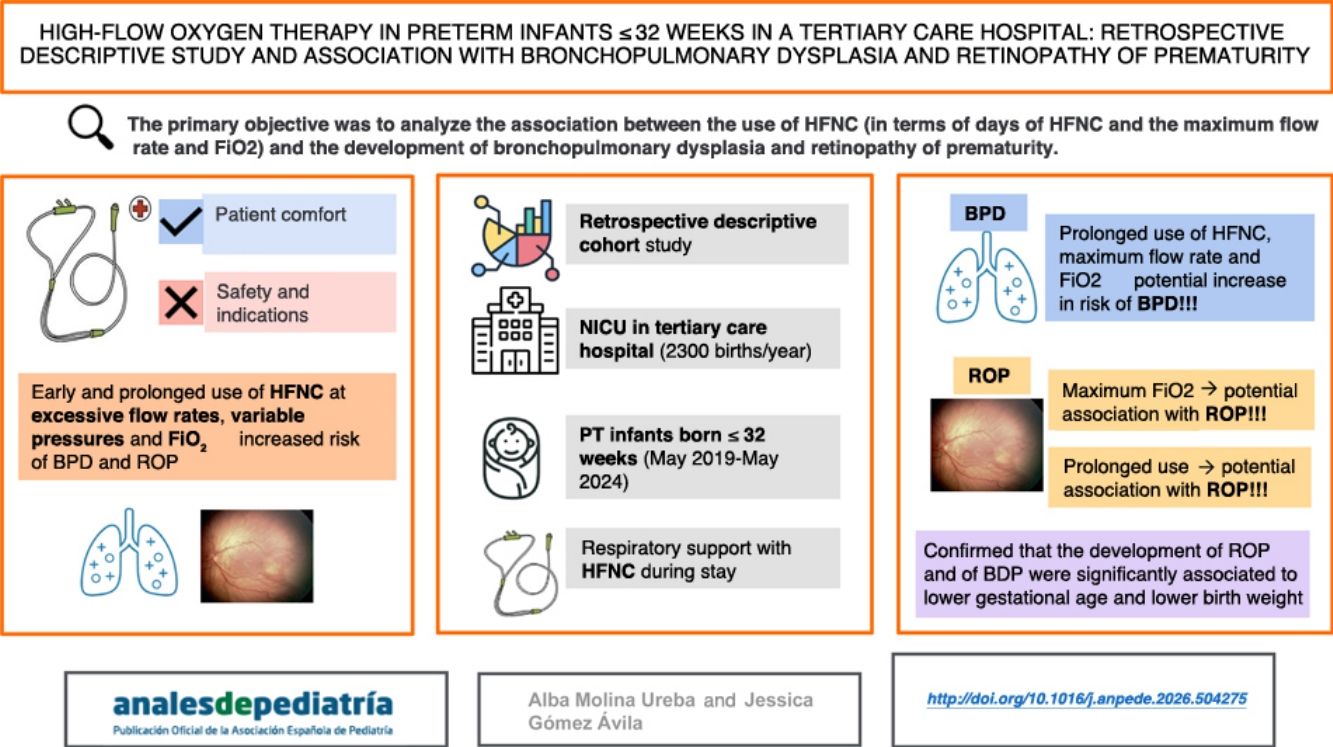
High-flow oxygen therapy (HFOT) is increasingly used for respiratory support in preterm newborns (PTNBs). However, there is still limited evidence regarding the impact of its early and prolonged use in this population, as well as its association with clinical outcomes such as bronchopulmonary dysplasia (BPD) and retinopathy of prematurity (ROP). The aim of our study was to describe our experience with the use of HFOT in PTNBs and to analyze its association with the prevalence of BDP and ROP.
Material and methodsRetrospective descriptive study conducted in a cohort of PTNBs born between May 2019 and May 2024 with gestational age ≤ 32 weeks who received HFOT during their stay in the neonatal intensive care unit of a tertiary care hospital. We analyzed data on variables related to HFOT exposure (duration, maximum flow, and FiO2) and the presence of BPD and ROP.
ResultsIn the analyzed cohort, we found a potential association between HFOT exposure parameters (days of use, maximum flow, and FiO2) and the presence of BPD. Likewise, we found evidence of a potential negative impact, as the duration of HFOT and the FiO2 were associated with the presence of ROP. The frequency of both complications increased with lower gestational age and lower birth weight.
ConclusionsIn this cohort, we observed a possible negative impact of the use of HFNC on the development of BPD and ROP, which was more evident in infants with lower gestational ages and birth weights. These findings should be interpreted with caution due to the descriptive design of the study and the lack of a comparison group, and analytical studies with appropriate control groups are required to further investigate these associations.
Las cánulas nasales de alto flujo (CNAF) se están consolidando como una modalidad creciente de soporte respiratorio en recién nacidos pretérmino (RNPT). Sin embargo, la evidencia actual es limitada en cuanto a las repercusiones de su implementación precoz y prolongada en estos pacientes y a su relación con resultados clínicos como la displasia broncopulmonar (DBP) y la retinopatía de la prematuridad (ROP). El objetivo de este estudio es describir la experiencia en el uso de CNAF en RNPT y analizar su asociación con la prevalencia de estas complicaciones.
Material y métodosEstudio descriptivo retrospectivo de una cohorte de RNPT con edad gestacional igual o inferior a 32 semanas, nacidos entre mayo de 2019 y mayo de 2024, que recibieron CNAF durante su ingreso, en una Unidad de Cuidados Intensivos Neonatales de un hospital de tercer nivel. Se recogieron variables relacionadas con la exposición a CNAF (duración, flujo máximo y FiO2) y la presencia de DBP y ROP.
ResultadosEn la cohorte analizada, se encuentra una posible asociación entre entre los parámetros de exposición a CNAF (días de uso, flujo máximo y FiO2) y la presencia de DBP. Asimismo, se observó un potencial impacto negativo entre los días de administración y la FiO2 con la presencia de ROP. La aparición de ambas complicaciones fue más frecuente en RNPT con menor edad gestacional y menor peso al nacimiento.
ConclusionesEn esta cohorte se observó una posible repercusión negativa del uso de CNAF con respecto al desarrollo de DBP y ROP, siendo más evidente a menor edad gestacional y peso al nacimiento. Estos hallazgos deben interpretarse con cautela, debido al diseño descriptivo del estudio y la ausencia de grupo comparador, requiriendo estudios analíticos con grupos de comparación adecuados para profundizar en estos resultados.

Over the past decade, the use of optimized noninvasive ventilation compared to mechanical ventilation has achieved decreases in mortality and length of stay in preterm (PT) infants. However, oxygen therapy is considered a potential risk factor for complications of preterm birth, such as retinopathy of prematurity (ROP) or bronchopulmonary dysplasia (BPD).1
Hyperoxia could result in abnormal development of the retina in its early stages, as it disrupts the normal growth of blood vessels and may result in vessel obliteration.2–4 At the pulmonary level, it can trigger cytokine-mediated inflammatory responses that interfere with the normal development of lung tissue, preventing the proper formation of the bronchioloalveolar structure and contributing to the development of BPD.4 Fluctuations in oxygen levels, damage caused by excessive flow rates, and variable airway pressure, which are characteristic of high-flow nasal cannula (HFNC), could contribute to the development of hyperoxia and, subsequently, ROP or BPD.
The use of HFNC in neonatal units is becoming widespread.5 This respiratory support modality involves delivering a high and constant flow of oxygen to the airway in order to reduce respiratory effort, improve mucociliary clearance, reduce nasopharyngeal dead space (increasing CO2 clearance), and generate pressure in the airway. However, there is variation in the generated pressure, as it depends on the age and weight of the patient, the administered flow rate, leaks around the nasal cannula, and the mouth opening.6 As a result, HFNC may fail to generate sufficient pressure to achieve functional residual capacity and maintain alveolar recruitment, so it is not the ideal respiratory support modality for preterm infants born at or before 28 weeks or with moderate-to-severe respiratory distress.7,8
Current indications of HFNC include its use as an alternative to CPAP following extubation and during weaning from respiratory support in infants born after 28 weeks; it is not recommended for extremely preterm infants. Some studies have also described its use in patients with mild-to-moderate respiratory distress and apnea of prematurity.5,7,9,10
The rise in its use is justified by the advantages it offers in terms of patient comfort, as it facilitates the initiation and escalation of enteral nutrition, reduces nasal trauma, and improves sensory stimulation, as nasal prongs allow increased eye contact with family members, thereby promoting developmental-centered care.5,7,9
There is no consensus regarding the implementation, indications and potential impact of the early and prolonged use of HFNC. Previous studies have found that it may be associated with increases in the days of supplemental oxygen and the incidence of BPD.1,5,7,8 Some studies have also found an increased risk of ROP, although the results are unclear.1,8,11
Most of the evidence on the subject focuses on comparing CPAP and HFNC for weaning patients from invasive ventilation in terms of clinical outcomes and potential repercussions, and the findings are contradictory.12 We did not find studies focused on the potential impact of aspects directly related to the characteristics of HFNC, like the delivery excessive flow rates or the maximum FiO2 used in PT infants. Given the growing use of HFNC, it is important to study the potential repercussions on these patients, since maintaining cardiorespiratory and hemodynamic stability is essential to avoid complications related to their inherent immaturity.13
We propose the hypothesis that the use of HFNC could increase the exposure to supplemental oxygen and uncontrolled pressures, which could have a negative impact by promoting the development of complications such as BPD and ROP. The primary objective of the study was to analyze the association of HFNC with the development of BPD and ROP, taking into account the specific characteristics of this respiratory support modality (days of use, maximum flow rate, and delivered FiO2). Another objective was to analyze and describe the baseline characteristics of the sample.
Material and methodsWe conducted a retrospective descriptive cohort study in the neonatal intensive care unit of a tertiary care hospital that manages 2300 births a year.
The sample consisted of PT infants born at or before 32 weeks of gestation over a 5-year period (May 2019–May 2024) who received respiratory support with HFNC during their hospital stay. We excluded infants born between 33 and 36 weeks, infants born at or before 32 weeks who only received respiratory support via conventional mechanical ventilation or noninvasive ventilation, and patients transferred from other health care facilities more than 2 days post birth.
We collected data on the baseline clinical characteristics of the patients, including sex, gestational age, birth weight, mode of delivery, administration of antenatal corticosteroids for lung maturation, and use of noninvasive ventilation and mechanical ventilation. Regarding HFNC, we recorded the duration in days, the maximum flow rate in liters per minute (L/min), and the maximum fraction of inspired oxygen (FiO2). We dichotomized the outcome variables (<6 L/min, ≥6 L/min; ≤25%, >25%), as the established categories represent clinically relevant cutoff points and the most widely used ranges in Spanish neonatal units.2
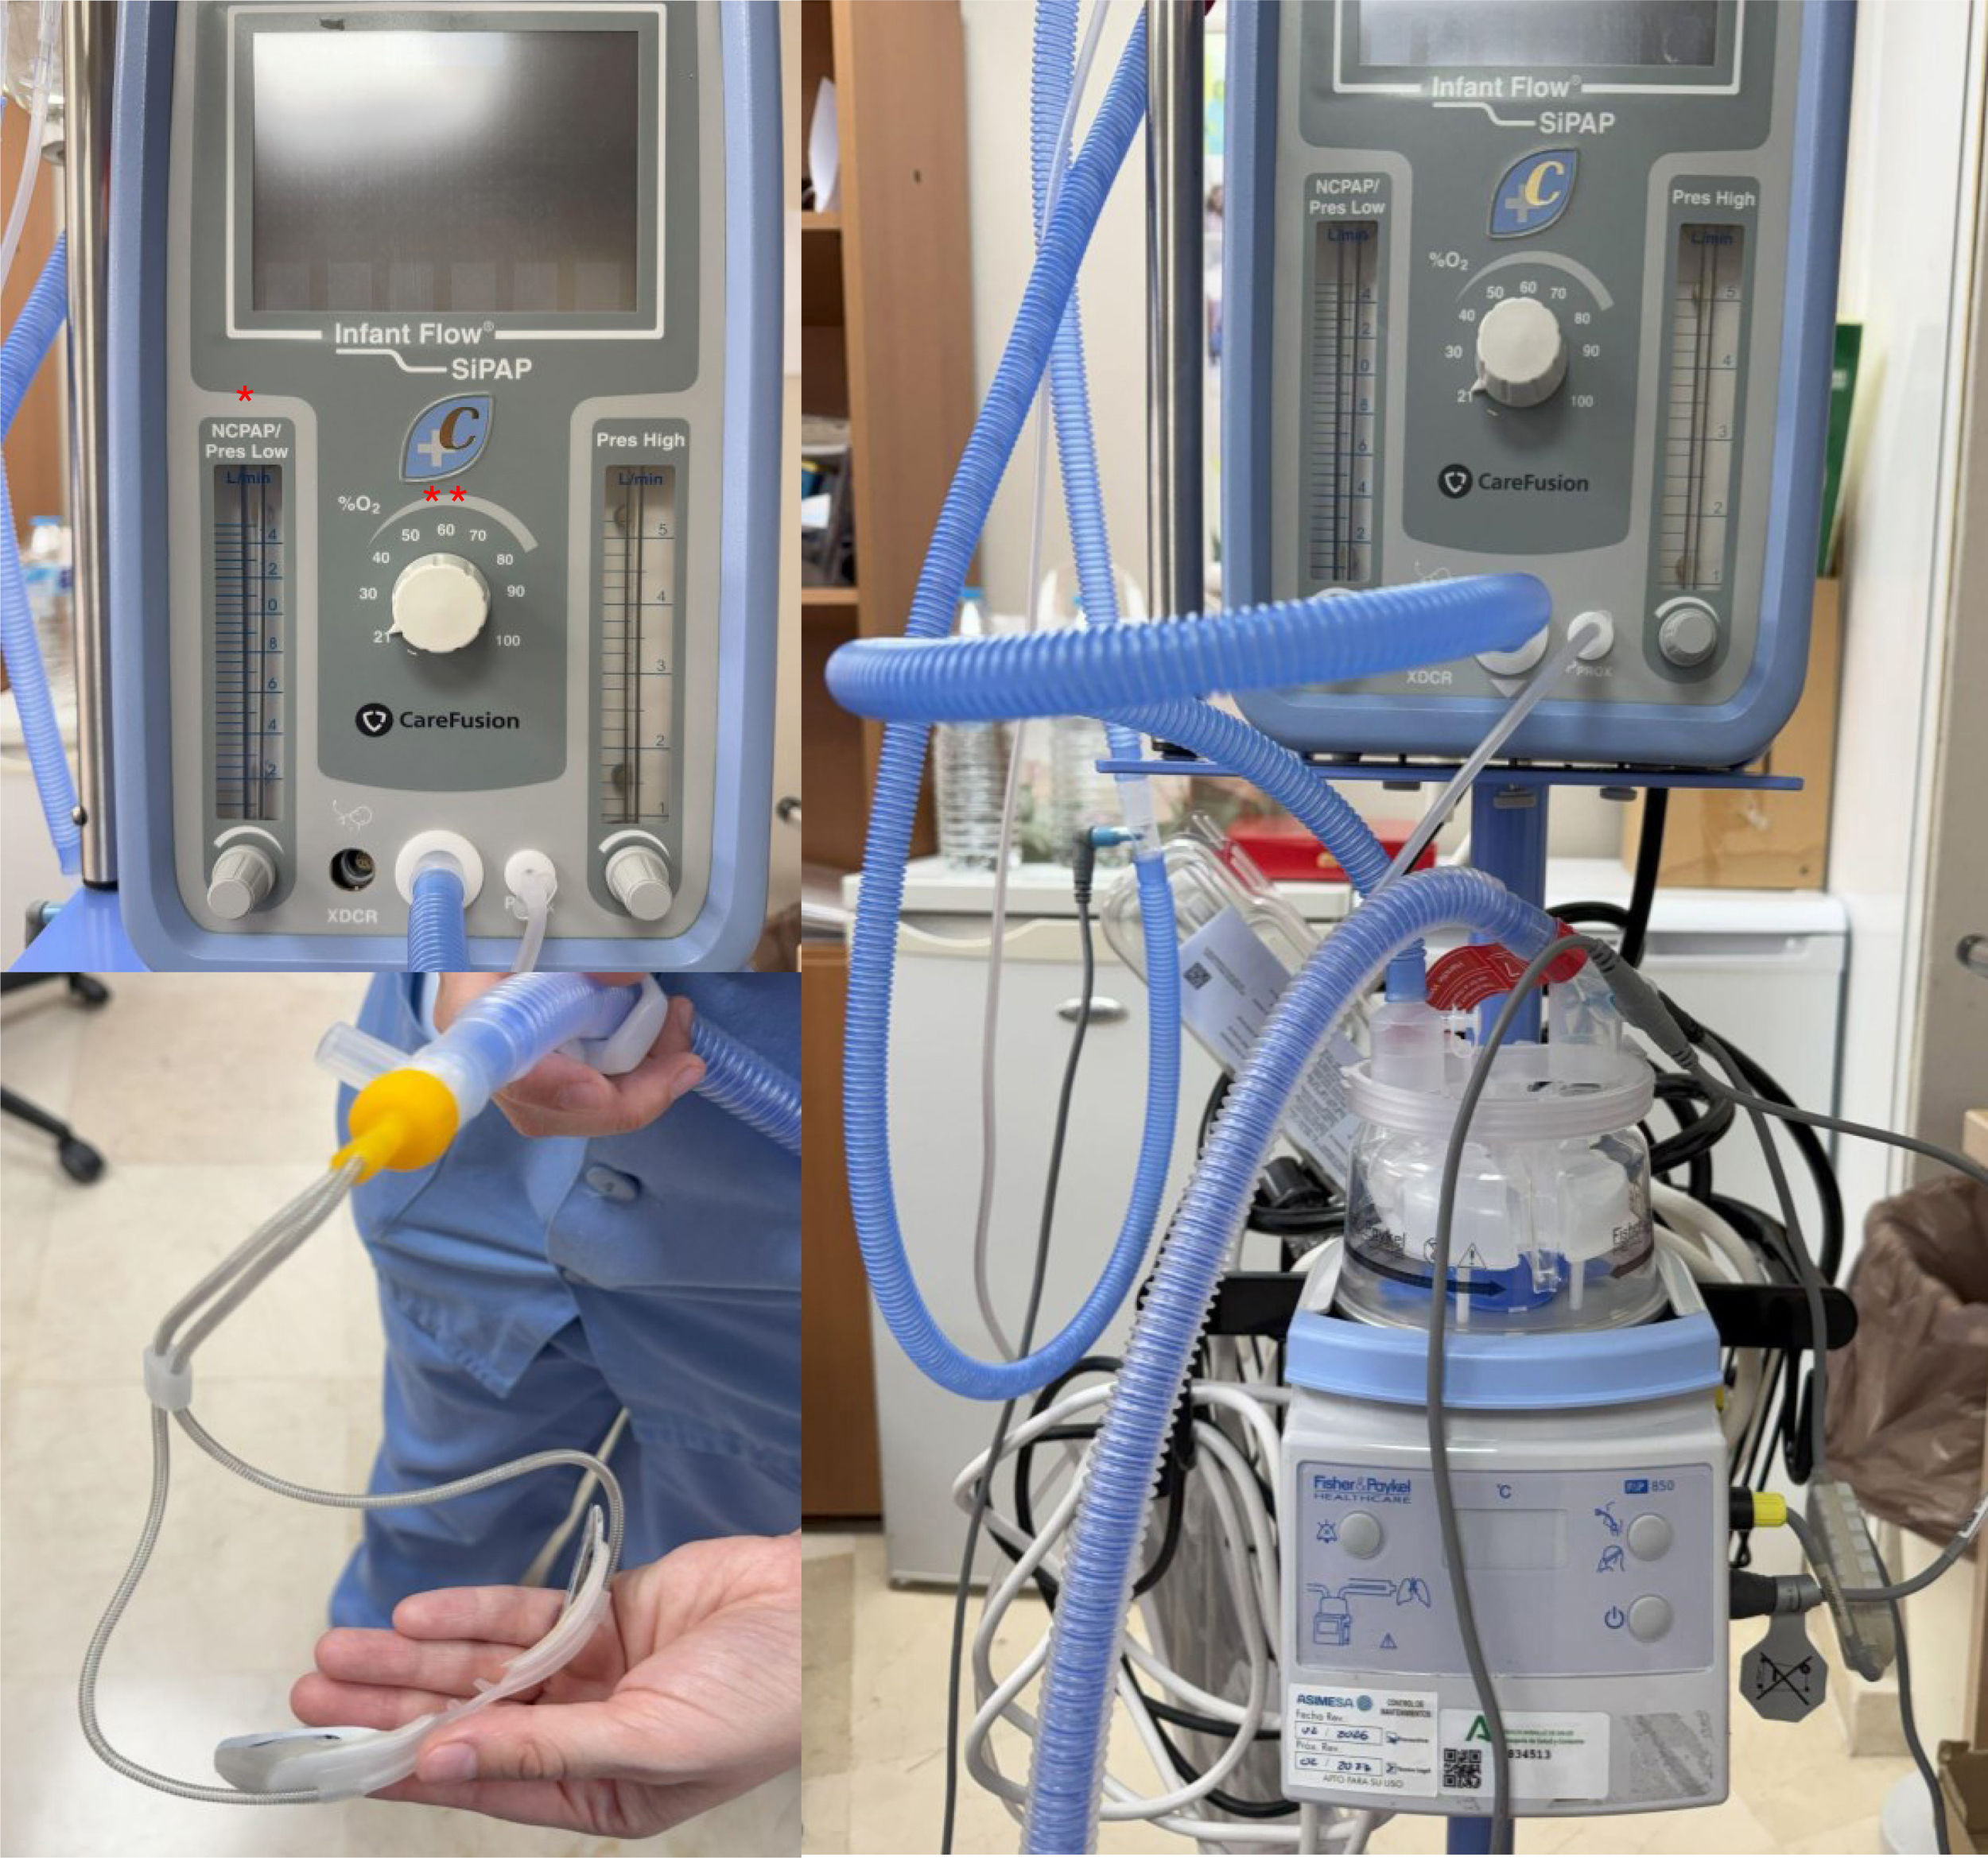
High-flow nasal cannula (HFNC) therapy was delivered using the Infant Flow system (Fig. 1) or an air-oxygen blender with Optiflow nasal cannulas selected based on the weight of the patient. In our unit, HFNC is chiefly used for three indications: (a) as an alternative to noninvasive ventilation (CPAP) following extubation or weaning from CPAP; (b) for hypoxemia and mild respiratory distress in patients with normal ventilation and a pattern indicative good aeration on pulmonary ultrasound; (c) for recurrent apnea in preterm infants. It is implemented with a flow rate ranging from a minimum of 2 L/min to a maximum of 12 L/min, and a FiO2 ranging from 21% to 60%. The flow rate is adjusted based on the patient’s clinical condition, limiting its use and escalating respiratory support in patients with respiratory acidosis, worsening respiratory distress, increasing oxygen requirements (up to a maximum FiO2 of 60%), or a lung ultrasound score (LUS) of 8 points or higher. There is no specific protocol for the implementation of HFNC, and the need to clarify how it should be used was another reason to conduct this study.

The diagnosis of BPD is based on an assessment of respiratory support needs and an oxygen reduction test at 36 weeks postmenstrual age to determine the severity of BPD, according to the 2017 Dysplasia Classification by Meyer et al., and the diagnosis of ROP on a fundus examination performed by the ophthalmology team, per the specific protocol of our unit, at 31 weeks postmenstrual age (gestational age < 28 weeks) or 4 weeks of chronological age (gestational age ≥ 28 weeks).
Statistical analysisThe analysis was performed with the software package SPSS, version 29.
Quantitative variables were described using measures of central tendency and dispersion, and qualitative variables using absolute and relative frequencies. In the case of qualitative variables, we tested the assumption of normality by means of the Shapiro-Wilk test. We compared quantitative variables in two groups using the nonparametric Mann-Whitney U test, as the data did not follow a normal distribution. Therefore, we report the median and the interquartile range (IQR, expressed as a single value).
The associations between qualitative variables were analyzed by means of contingency tables and the chi-square test or non-asymptotic methods.
We fitted univariate logistic regression models for the variables that were significantly associated with the outcomes of interest (ROP or BPD). All significant variables identified in the univariate analysis were included in the multivariate logistic regression model. The goodness-of-fit of the multivariate model was assessed with the Hosmer-Lemeshow test.
Statistical significance was defined as a P value of less than .05.
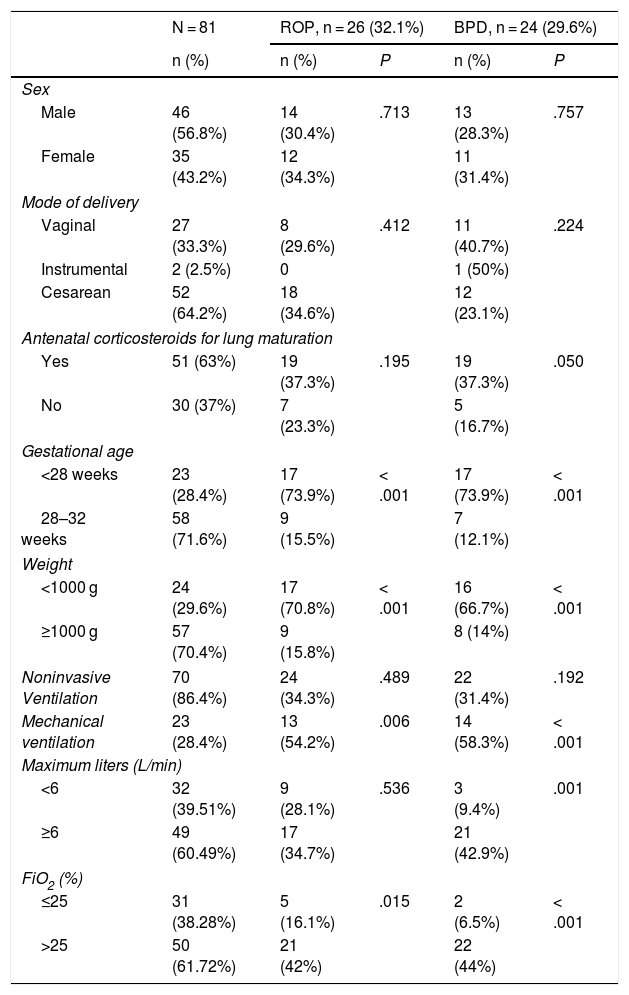
ResultsThe analysis included 81 patients born at or before 32 weeks of gestation who received respiratory support with HFNC. Forty-six were male, and the mean gestational age was 206 days (SD, 15.5), or 29+3 weeks, with a mean birth weight of 1247 g (SD, 410.6). In addition, 64.2% were delivered by cesarean section, and 63% had received a complete course of antenatal corticosteroids (Table 1).
Analysis of the study variables in relation to HFNC use, gestational age, and birth weight and the development of ROP and BPD.
| N = 81 | ROP, n = 26 (32.1%) | BPD, n = 24 (29.6%) | |||
|---|---|---|---|---|---|
| n (%) | n (%) | P | n (%) | P | |
| Sex | |||||
| Male | 46 (56.8%) | 14 (30.4%) | .713 | 13 (28.3%) | .757 |
| Female | 35 (43.2%) | 12 (34.3%) | 11 (31.4%) | ||
| Mode of delivery | |||||
| Vaginal | 27 (33.3%) | 8 (29.6%) | .412 | 11 (40.7%) | .224 |
| Instrumental | 2 (2.5%) | 0 | 1 (50%) | ||
| Cesarean | 52 (64.2%) | 18 (34.6%) | 12 (23.1%) | ||
| Antenatal corticosteroids for lung maturation | |||||
| Yes | 51 (63%) | 19 (37.3%) | .195 | 19 (37.3%) | .050 |
| No | 30 (37%) | 7 (23.3%) | 5 (16.7%) | ||
| Gestational age | |||||
| <28 weeks | 23 (28.4%) | 17 (73.9%) | < .001 | 17 (73.9%) | < .001 |
| 28–32 weeks | 58 (71.6%) | 9 (15.5%) | 7 (12.1%) | ||
| Weight | |||||
| <1000 g | 24 (29.6%) | 17 (70.8%) | < .001 | 16 (66.7%) | < .001 |
| ≥1000 g | 57 (70.4%) | 9 (15.8%) | 8 (14%) | ||
| Noninvasive Ventilation | 70 (86.4%) | 24 (34.3%) | .489 | 22 (31.4%) | .192 |
| Mechanical ventilation | 23 (28.4%) | 13 (54.2%) | .006 | 14 (58.3%) | < .001 |
| Maximum liters (L/min) | |||||
| <6 | 32 (39.51%) | 9 (28.1%) | .536 | 3 (9.4%) | .001 |
| ≥6 | 49 (60.49%) | 17 (34.7%) | 21 (42.9%) | ||
| FiO2 (%) | |||||
| ≤25 | 31 (38.28%) | 5 (16.1%) | .015 | 2 (6.5%) | < .001 |
| >25 | 50 (61.72%) | 21 (42%) | 22 (44%) | ||
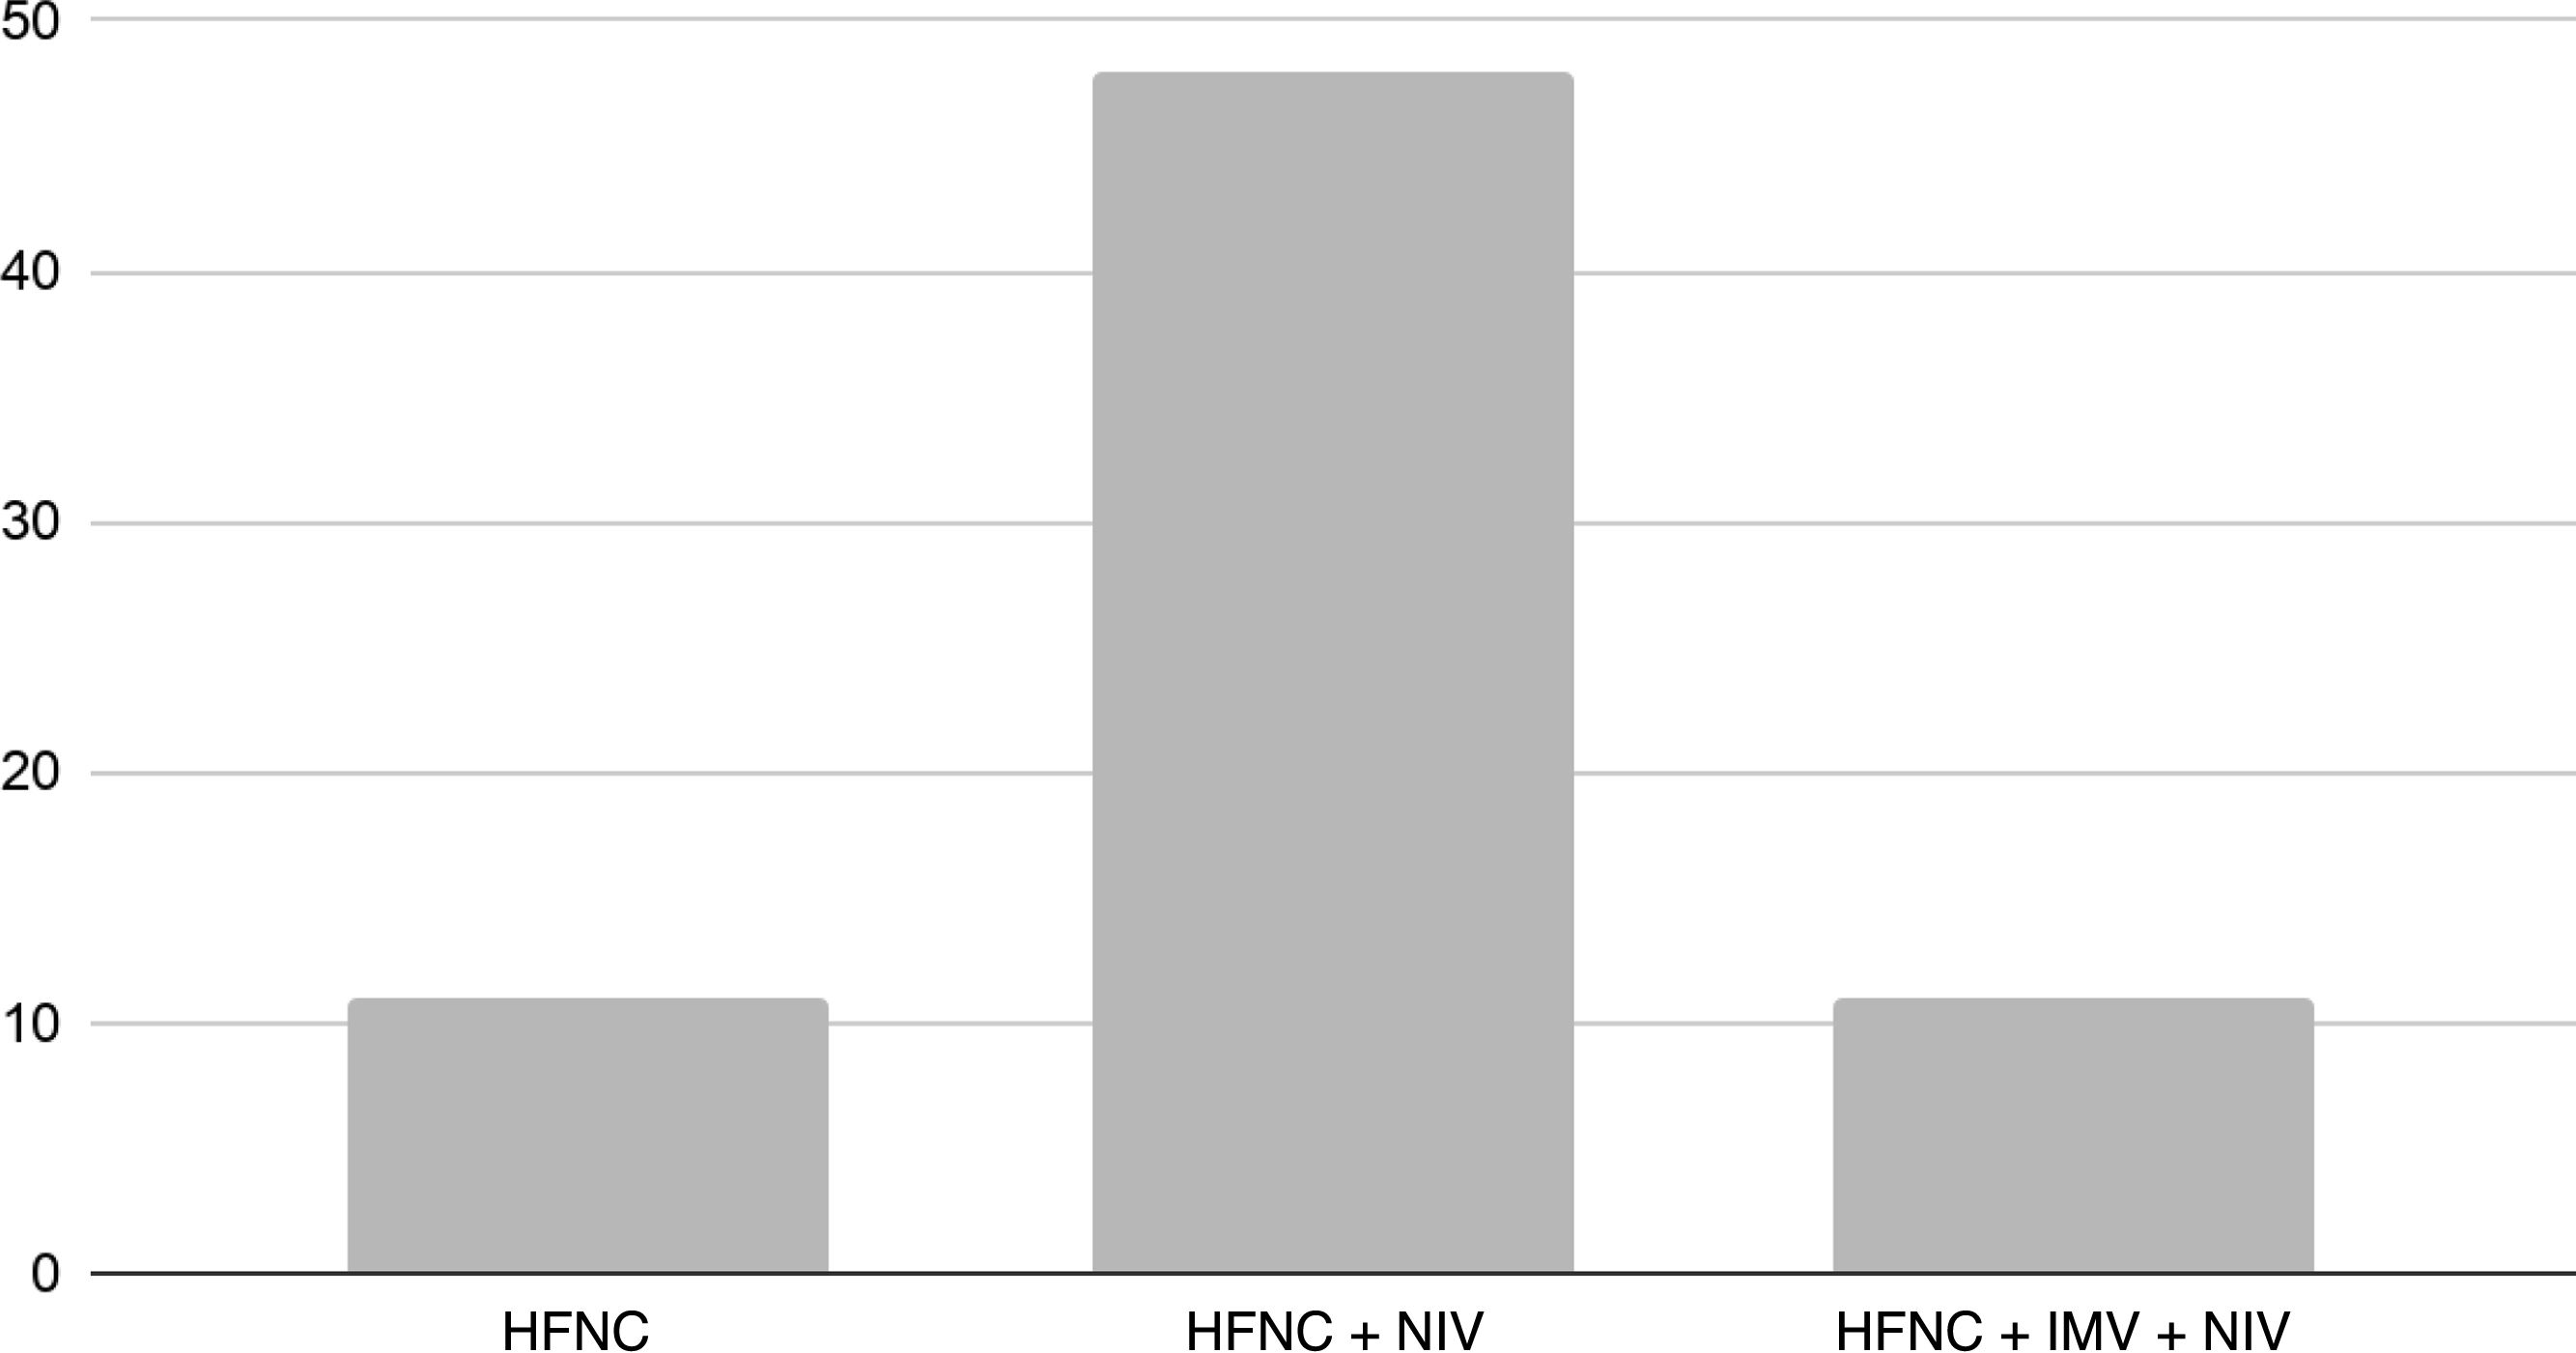
All patients in the sample received respiratory support via HFNC for a median of 32.50 days (IQR, 29). In 60.49% of patients, the maximum flow rate was 6 L/min, and the mean FiO2 was 27%. In addition, 86.4% of patients received noninvasive ventilation, used in 34.3% of ROP cases and in 31.4% of BPD cases. Mechanical ventilation was used in 28.4% of the sample, including 54.2% of patients with ROP and 58.3% of patients with BPD. Only 11 patients received HFNC alone (Table 1 and Fig. 2).

Bronchopulmonary dysplasia occurred in 29.6% of patients. Of this total, 54.2% had mild BPD, 29.2% had moderate BPD, and 16.7% had severe BPD.
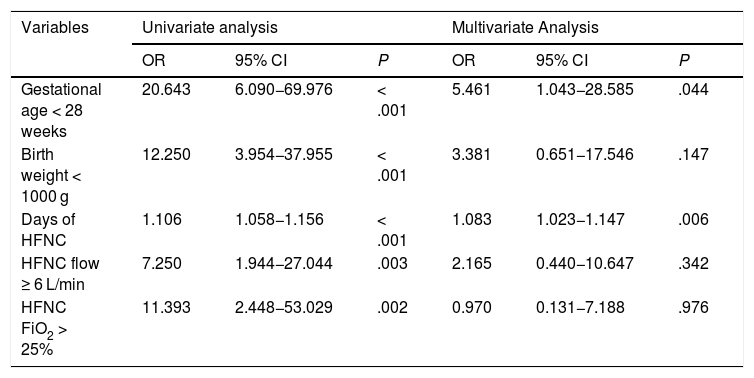
It occurred in 73.9% of patients born before 28 weeks and 66.7% of patients with birth weights below 1000 g, and the associations of BPD with lower gestational age and with birth weight were confirmed in the univariate analysis (Table 2).
Logistic regression. Univariate and multivariate analysis of study variables in relation to BPD.
| Variables | Univariate analysis | Multivariate Analysis | ||||
|---|---|---|---|---|---|---|
| OR | 95% CI | P | OR | 95% CI | P | |
| Gestational age < 28 weeks | 20.643 | 6.090−69.976 | < .001 | 5.461 | 1.043−28.585 | .044 |
| Birth weight < 1000 g | 12.250 | 3.954−37.955 | < .001 | 3.381 | 0.651−17.546 | .147 |
| Days of HFNC | 1.106 | 1.058−1.156 | < .001 | 1.083 | 1.023−1.147 | .006 |
| HFNC flow ≥ 6 L/min | 7.250 | 1.944−27.044 | .003 | 2.165 | 0.440−10.647 | .342 |
| HFNC FiO2 > 25% | 11.393 | 2.448−53.029 | .002 | 0.970 | 0.131−7.188 | .976 |
We found that the use of HFNC could have a negative impact in terms of the development of BPD. The median days of HFNC was higher in patients who developed BPD (32.50 days; IQR, 29) compared to patients who did not (4 days; IQR, 12). On the other hand, 44% of patients who received a FiO2 of 25% or greater developed BPD, corresponding to a 11.39 greater risk to develop BPD compared to patients managed with FiO2 of less than 25%. In addition, the risk of BPD was 7.25 times greater in patients managed with flow rates of 6 L/min or greater compared to lower flow rates (Table 2).
In the multivariate analysis, the variables that were significantly associated with BPD were gestational age and the use of HFNC. The risk to develop BDP was 5.46 times higher in preterm infants born before 28 weeks. Furthermore, in our cohort, we found that the risk of BPD increased by 8.3% with each additional day of HFNC (Table 2).
Retinopathy of prematurity occurred in 32.1% of the total sample. It was classified as stage 1 in 34.6% of cases, stage 2 in 50% and stage 3 in 15.4%. None of the patients developed stage 4 or 5 ROP.
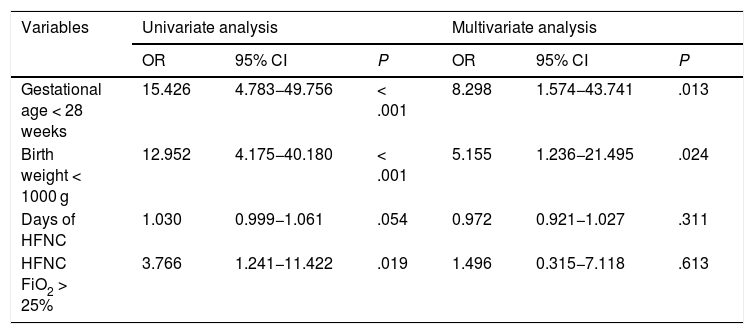
This complication ocurred in 73.9% of patients born before 28 weeks, with a statistically significant association between lower gestational age and ROP. The univariate analysis corroborated this association, showing that the risk of ROP in this gestational age group was 15.43 times higher compared to patients born between 28 and 32 weeks. In addition, we found a significant association between lower birth weight and the development of ROP, which occurred in 70.8% of patients with birth weights of less than 1000 g. In the univariate analysis, the risk of ROP was 12.95 times higher in patients with birth weights under 1000 g compared to birth weights of 1000 or greater. These associations were confirmed in the multivariate analysis (Table 3).
Logistic regression. Univariate and multivariate analysis of study variables in relation to ROP.
| Variables | Univariate analysis | Multivariate analysis | ||||
|---|---|---|---|---|---|---|
| OR | 95% CI | P | OR | 95% CI | P | |
| Gestational age < 28 weeks | 15.426 | 4.783−49.756 | < .001 | 8.298 | 1.574−43.741 | .013 |
| Birth weight < 1000 g | 12.952 | 4.175−40.180 | < .001 | 5.155 | 1.236−21.495 | .024 |
| Days of HFNC | 1.030 | 0.999−1.061 | .054 | 0.972 | 0.921−1.027 | .311 |
| HFNC FiO2 > 25% | 3.766 | 1.241−11.422 | .019 | 1.496 | 0.315−7.118 | .613 |
In relation to the use of HFNC, the duration of HFNC was longer in patients who developed ROP compared to those who did not (median, 18 days [IQR, 24] vs 4 days [IQR, 21]). In the univariate analysis, the P value neared the threshold of significance, and this finding may be clinically relevant, as the risk of ROP increased by 3% with each additional day of HFNC in this cohort. In patients treated with a FiO2 of 25% or greater, the proportion of patients who developed ROP was greater (42%), with a 3.77-fold risk of developing this complication compared to those treated with lower FiO2 (Table 3). However, when we compared this outcome based on the maximum flow rate, we did not find a statistically significant association.
We conducted another multivariate analysis including mechanical ventilation as a variable, which did not change the results of the previous analyses.
DiscussionThis retrospective study found a potential association between the use of HFNC and the development of complications of prematurity, such as BPD and ROP.
We found an association between the maximum FiO2 and the development of ROP. This finding was consistent with previous evidence on the role of hyperoxia, the duration of oxygen therapy, and fluctuations in oxygen levels as factors that affect retinal vascularization in the infant.4 Although we found a direct association between prolonged use of HFNC and the risk of ROP, the P value only neared the threshold for statistical significance in the univariate analysis. This could be explained by the small sample size. However, we did not identify a direct association between the maximum flow rate and the occurrence of this complication, although most patients who developed ROP received flow rates of 6 L/min or greater.
These findings were consistent with the heterogeneity of the results reported in the available literature. A meta-analysis published in 20248 that included 7 clinical trials and a total of 781 preterm infants born before 37 weeks of gestation did not find a significant association between the use of HFNC vs CPAP and the development of ROP or BPD. On the other hand, Mena et al.1 conducted an observational and analytical case-control study to investigate the association between HFNC and the development of complications and found a statistically significant association with the risk of both ROP and BPD. Similarly, two studies published in 2016 and 20198,13 found an increased incidence of ROP in preterm infants after the introduction of HFNC compared to weaning with CPAP, as well as an increased severity of ROP and increased need of surgical management. These findings support a potential link between the use of HFNC and ROP, although other intercurrent factors and the baseline characteristics of the patients also need to be taken into account.
In our study, we found that longer use of HFNC, higher FiO2, and higher flow rates could have a negative impact on lung development, increasing the risk of BPD.
There is growing evidence that the use of HFNC increases the days of respiratory support.7,8 A randomized controlled trial published in 201614 studied the use of HFNC as primary respiratory support in preterm infants born before 28 weeks with respiratory distress syndrome. The proportion of treatment failure was higher in the HFNC group compared to the CPAP group (25.5% vs 13.3%; P < .001), with a longer duration of respiratory support in the HFNC group. Longer duration could itself explain the increased risk of BPD, although other hypotheses need to be considered as well. Since HFNC generates variable airway pressures that depend on the individual characteristics of the patient, it could give rise to more distended or collapsed areas, or result in inconsistent alveolar recruitment, which could lead to atelectrauma in a poorly recruited and immature lung. In addition, HFNC may not have the beneficial effect of positive airway pressure on the maturation of the bronchioloalveolar structure.8,11
Our findings were confirmed in the univariate analysis, and we ought to highlight the days of HFNC as a significant variable in the multivariate analysis for the potential development of this complication. In a retrospective study published in 2016, Taha et al.7 found that the use of HFNC in preterm infants was associated with an increase in the combined outcome of BPD or death compared to the use of CPAP (56.8% vs 50.4%; P < .05). Similarly, Healey et al.12 conducted a retrospective study comparing the use of HFNC as an alternative to CPAP for weaning preterm infants (< 30 weeks gestational age or birth weights < 1500 g) and found an increased incidence of BPD after the introduction of HFNC (35.3%; P < .001). The aforementioned study published in 20248 found a significant and clinically relevant association between increased duration of oxygen therapy, increased incidence of BDP and the use of HFNC in PT infants.
Our unit does not have a specific protocol for HFNC, as occurs in other neonatal units in Spain. A study conducted with the aim of clarifying the adequate use of HFNC in neonatal units was published in 2021. It concluded that, while flow rates of 2 L/min/kg may be described, there is broad variation in actual practice, with delivery of flow rates ranging between 1 and 15 L/min, which evinces the need for further research to guide the development of consensus recommendations to standardize the use of HFNC.5 The lack of guidelines on the indication and adequate settings of HFNC could be a source of confounding by indication, given that the decision to use HFNC is based on individual clinical judgment, and therefore hinders the generalization of results and conclusions.
In agreement with the previous literature,4,8,12 we found an association between the development of ROP and BPD and lower gestational age and birth weight.
ConclusionsAlthough the current evidence suggests that HFNC could be an effective alternative to CPAP for respiratory support in preterm infants, caution should be exerted. At present, there is no conclusive evidence of its efficacy and safety, especially in extremely PT infants. It has been suggested that the use of HFNC in these patients, especially when it is prolonged or involves high flow rates and FiO2, could contribute to the risk of BDP. Furthermore, it has been hypothesized that it may have a negative impact in terms of the risk of ROP.
However, the small sample size, the potential for confounding by indication, and the retrospective and descriptive design of the study precluded the establishment of causality or ruling out the presence of unmeasured factors that may have affected the results. Therefore, these findings must be interpreted with caution and highlight the need for prospective studies with adequate comparison groups, ideally including controls, to confirm causality and define the indications, optimal settings and potential adverse effects of HFNC more clearly, in order to ensure the safe implementation of HFNC in neonatal units.
FundingThis research did not receive any external funding.
The authors have no conflicts of interest to declare.



