



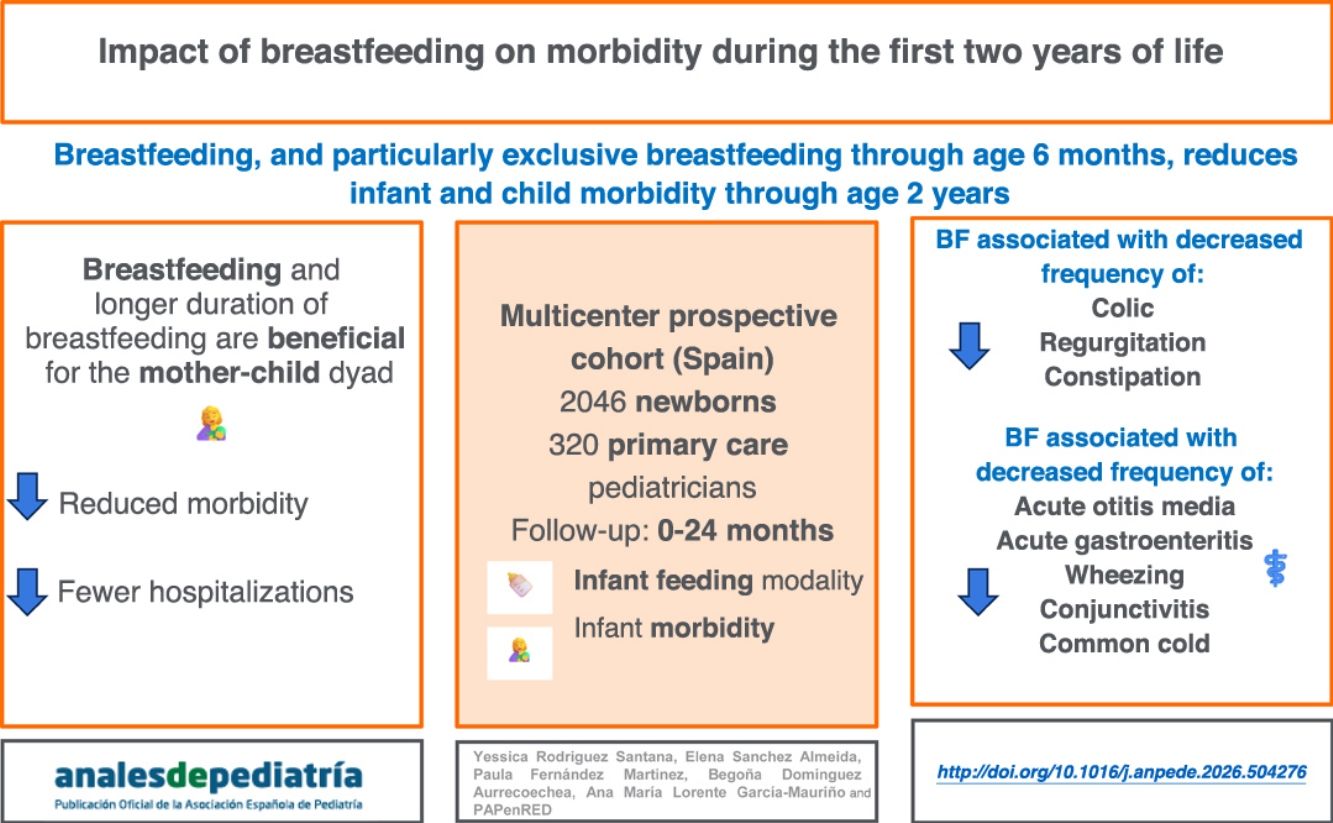
Breastfeeding (BF) has demonstrated multiple benefits for the mother-infant dyad, including immunological protection for the child. This study assessed the relationship between breastfeeding patterns and morbidity during the first two years of life.
MethodsWe conducted a secondary analysis of data from the LAYDI study. This study was a single-cohort trial to analyze the association between breastfeeding and child development carried out by the Primary Care Pediatric Research Network (PAPenRed) and involving 320 pediatricians. Each pediatrician recruited one newborn per month over one year and followed them up to age 24 months. Demographic, feeding, and morbidity data were collected over seven visits (<15 days, and at 1, 2, 6, 12, 18, and 24 months).
ResultsThe sample included 2046 infants. We found that BF had a protective effect against common conditions such as constipation in the early visits (P < .001), and against infectious diseases after adjusting for confounders (“having siblings” and “enrolment in child care center”) (P < .001 at 12 and 18 months). Breastfeeding also offered specific protection against the most frequent acute infections, including otitis media, conjunctivitis, bronchiolitis, gastroenteritis, and wheezing episodes, which remained statistically significant after adjustment (P < .005). Exclusive breastfeeding (EBF) through age 6 months conferred long-term protection, particularly against acute otitis media (at 12, 18, and 24 months [P < .001, P < .004, and P < .036]).
ConclusionsBreastfeeding has a protective effect against common gastrointestinal disorders in infancy (constipation, colic, regurgitation) and against infectious diseases. Exclusive BF in the first 6 months provides sustained protection (12–24 months) against the 19 conditions under study, particularly the most prevalent ones. These results support the association between breastfeeding and reduced morbidity extending through at least the age two years.
La lactancia materna (LM) se asocia a beneficios para la salud infantil, incluida la reducción de la morbilidad infecciosa. El objetivo de este estudio fue analizar la asociación entre el tipo de lactancia y la morbilidad durante los dos primeros años de vida.
MétodosAnálisis secundario de un estudio amplio sobre lactancia de una cohorte prospectiva multicéntrica desarrollada por una red española de pediatras investigadores de Atención Primaria (AP). Participaron 320 pediatras, que reclutaron un recién nacido al mes durante un año, con seguimiento hasta los 24 meses. Se recogieron datos demográficos, tipo de lactancia y morbilidad en siete visitas (<15 días, 1, 2, 6, 12, 18 y 24 meses). Se analizaron procesos habituales del lactante y 19 patologías agudas y crónicas prevalentes. Todas las asociaciones se estimaron mediante modelos ajustados por variables confusoras (tener hermanos y asistencia a centro infantil).
ResultadosSe incluyeron 2046 niños. La LM se asoció a menor frecuencia de procesos habituales del lactante, como el estreñimiento, especialmente en las primeras visitas (p < 0,001). Asimismo, se observó una menor morbilidad infecciosa en los niños que recibieron LM, particularmente a los 12 y 18 meses (p < 0,001). La LM se asoció a un menor riesgo de las infecciones agudas más frecuentes, incluyendo otitis media aguda, conjuntivitis, bronquiolitis, gastroenteritis y episodios de sibilancias, con significación estadística ajustada (p < 0,005). Recibir lactancia materna exclusiva durante los primeros 6 meses se asoció a una menor morbilidad global a medio plazo frente al conjunto de las 19 patologías estudiadas a los 12, 18 y 24 meses, manteniéndose un efecto protector específico en las patologías más prevalentes.
ConclusionesLa LM, especialmente cuando es exclusiva durante los primeros 6 meses de vida, se asocia a una menor morbilidad infantil frecuente durante los dos primeros años, con un efecto protector que se mantiene a medio plazo.

There is ample evidence of the benefits of breastfeeding.1–4 Exclusive breastfeeding is recommended for the first 6 months of life, in addition to continued breastfeeding combined with complementary foods until age 2 years or older.5,6
In Spain, as in other developed countries, BF rates remain low and,7 despite slight improvement in recent years, far from the targets proposed by the World Health Organization (WHO).8 A systematic review by the WHO published in 2013 concluded that BF was associated with a decrease in mortality and infectious diseases, a lower prevalence of anemia, obesity and atopic diseases, and better cognitive outcomes in childhood.2 Breastfeeding has been consistently found to confer protection against infectious diseases in early childhood and infant and child mortality in countries at every level of development.9–18
A subsequent systematic review estimated that scaling up BF to a universal level could prevent up to 823 000 child deaths and 20 000 deaths from breast cancer in women each year.4 Breastfeeding is associated with a reduction in infant and child morbidity and mortality and is even considered a key intervention for child survival, particularly in infants younger than 6 months, with a protective effect throughout the first 2 years of life.18 In this regard, studies in developed countries have found an association between lack of breastfeeding and an increase in morbidity from common early childhood illnesses, such as acute otitis media (AOM), acute gastroenteritis (AGE), respiratory infections, atopic dermatitis, asthma, obesity, diabetes, leukemia, sudden infant death syndrome, and necrotizing enterocolitis.19 Even any form of BF appears to reduce the risk of AOM in the first 2 years of life.10,20–22
Several studies have demonstrated a dose-response effect, so that a longer duration of BF during the first 6 months is associated with a lower risk of otitis,15 diarrhea,16 and respiratory infections,11,23,24 as well as a reduction in the rate of hospitalization due to infection in the first year of life.25
These findings support current recommendations to promote exclusive breastfeeding for the first 6 months of life, although further studies are needed to assess its medium-term impact. The primary objective of our study was to analyze the association between infant feeding modality in the first 6 months and child morbidity during the first 2 years of life. As a secondary objective, we analyzed the association between continued breastfeeding of any type after the introduction of complementary foods and child morbidity up to age 24 months.
Material and methodsWe conducted a secondary analysis of data acquired in a large-scale prospective multicenter cohort study on BF26–29 whose general objective was to describe the characteristics of BF in Spain and the factors associated to its initiation and maintenance for the purpose of developing BF promotion strategies and contributing to adequate child growth and development and disease prevention.
Design and settingLongitudinal, prospective, multicenter cohort study in newborns monitored at the primary care level through age 24 months. The participating pediatricians were members of a Spanish primary care pediatrics research network of that comprises 320 pediatricians employed in the national public health system, with proportional representation of all the autonomous communities of Spain.
Study sample and periodIn 2015, there were 426 303 births in Spain. For a margin of error of 2.2% and a confidence level of 95%, we estimated that we needed a minimum sample size of 1500 children. The study included infants born between April 2017 and March 2018, who were followed up until March 2020.
Inclusion and exclusion criteriaFor one year, the first infant aged less than 15 days seen each month by each participating pediatrician was selected for inclusion. The exclusion criteria were: preterm birth (<37 weeks), low birth weight (<2400 g for boys and <2100 g for girls), multiple birth, stay longer than 5 days in postpartum or neonatal unit, malformation or severe neonatal disease, clinically significant maternal illness, language barriers, refusal to participate, and circumstances precluding follow-up.
Data collectionVisits were scheduled at less than 15 days and at 1, 2, 4, 6, 12, 18, and 24 months post birth. Primary care pediatricians recorded the data in a dedicated database. At each visit, the pediatrician documented the infant feeding modality implemented in the past 7 days, classified as:
- •
EBF
- •
Formula feeding from birth (FF_frombirth)
- •
Formula feeding after BF discontinuation (FF_afterBF)
- •
Mixed milk feeding (MMF)
From age 6 months, we used the term “continued BF” to refer to continuation of BF along with complementary feeding, and “FF” to refer to formula feeding combined with other foods.
MorbidityTo minimize the seasonal effect, providers included one newborn per month throughout the year. Morbidity data were not collected at the 4-months visit. Parents provided the information, which was supplemented with data from the electronic health records kept by the collaborating pediatricians in charge of the patients. The providers documented episodes of common conditions in infants (“conditions”), hospital admissions and chronic diseases, as well as the most prevalent acute illnesses according to 2012 data from the Primary Care Health Records System (BDCAP). In the case of skin diseases (contact or atopic dermatitis), we collected information on the number of flare-ups. The pediatricians used standardized diagnostic definitions based on recent clinical guidelines, the International Classification of Primary Care (ICPC-2), and the International Classification of Diseases ninth and tenth revisions (ICD-9 and ICD-10).
Other study variables were having siblings, attending a childcare center (childcare attendance), and morbidity at ages 12, 18, and 24 months, documented in relation to whether the infant had been exclusively breastfed through age 6 months (EBF_6m).
Statistical analysisWe performed a descriptive analysis, calculating absolute and relative frequencies for the different variables, overall and by type of breastfeeding. The type of breastfeeding was assessed at each visit, and morbidity at 12, 18, and 24 months in relation to maintenance of EBF through age 6 months. We fitted logistic regression models in which the feeding modality was the independent variable, both on a visit-by-visit basis and in the long-term (EBF_6m), and calculated odds ratios (ORs) for each of the outcomes. Relative risks (RRs) were also calculated for each of the conditions using Poisson regression, with infant feeding modality as the independent variable. We fitted univariate models for each disease, which were subsequently adjusted for the “having siblings” and “childcare attendance” confounding variables. Statistical significance was defined as a p value of less than 0.05. All the analyses were performed with the R software, version 4.4.2 (R Foundation for Statistical Computing; Vienna, Austria).
Ethical considerationsThe study was conducted in adherence to the principles of the Declaration of Helsinki and approved by the Ethics Committees of Aragon (Minute 19/2013; C.P.-C.I. PI13/00154) and the principality of Asturias (study no. 213/16), as well as the committees in the corresponding autonomous communities. The data were pseudonymized in accordance with EU Regulation 2016/679, and we obtained informed consent from the parents.
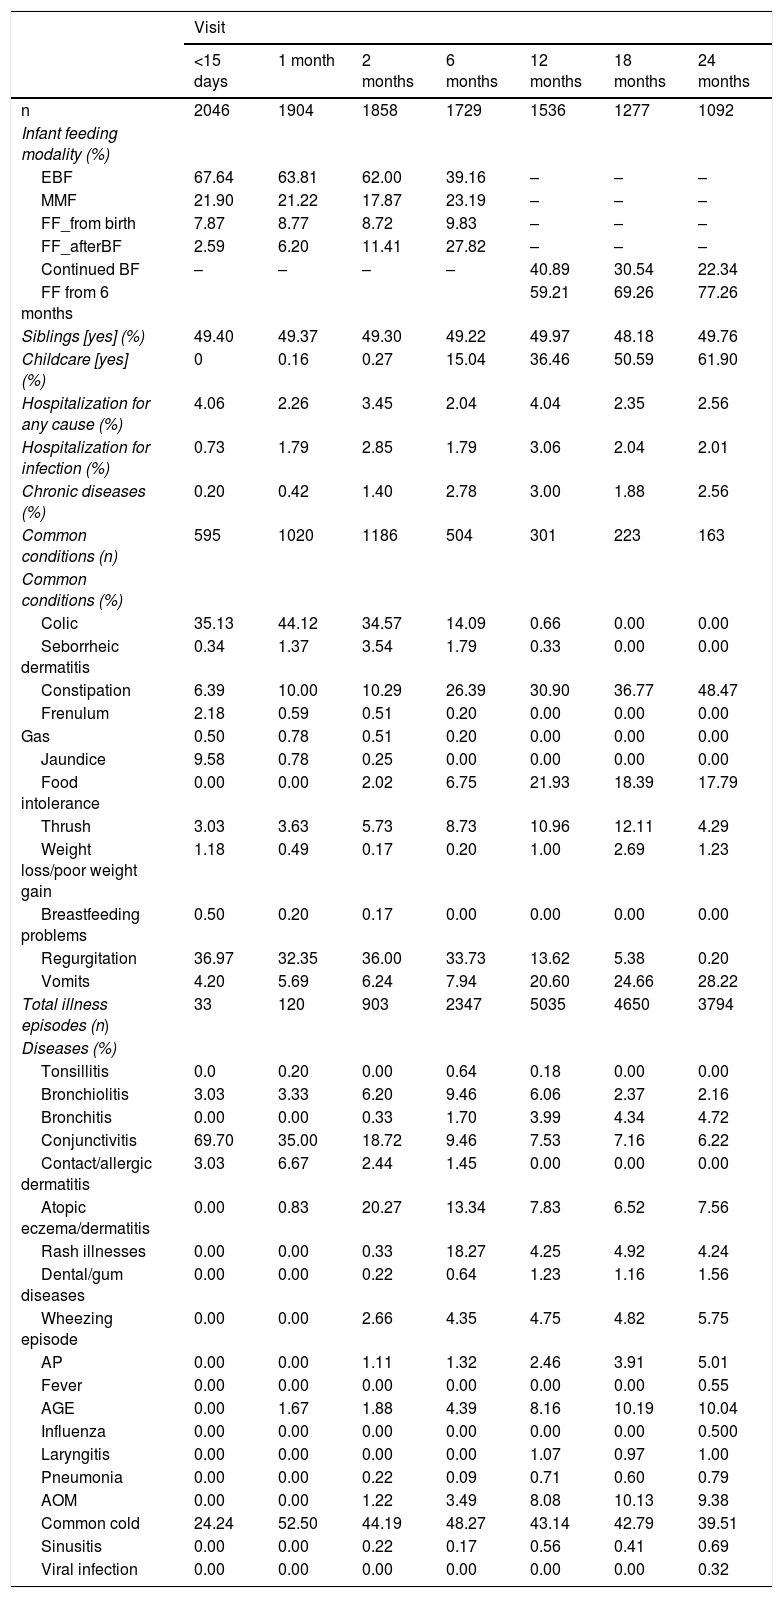
ResultsGeneral results (Table 1)A total of 2046 newborns were included during their first primary care checkup visit (<15 days), and 1092 completed the follow-up through age 24 months. Of the total infants, 50.2% were only children. Childcare attendance increased progressively from age 12 months (Table 1).
Descriptive analysis of the variables documented at each visit.
| Visit | |||||||
|---|---|---|---|---|---|---|---|
| <15 days | 1 month | 2 months | 6 months | 12 months | 18 months | 24 months | |
| n | 2046 | 1904 | 1858 | 1729 | 1536 | 1277 | 1092 |
| Infant feeding modality (%) | |||||||
| EBF | 67.64 | 63.81 | 62.00 | 39.16 | – | – | – |
| MMF | 21.90 | 21.22 | 17.87 | 23.19 | – | – | – |
| FF_from birth | 7.87 | 8.77 | 8.72 | 9.83 | – | – | – |
| FF_afterBF | 2.59 | 6.20 | 11.41 | 27.82 | – | – | – |
| Continued BF | – | – | – | – | 40.89 | 30.54 | 22.34 |
| FF from 6 months | 59.21 | 69.26 | 77.26 | ||||
| Siblings [yes] (%) | 49.40 | 49.37 | 49.30 | 49.22 | 49.97 | 48.18 | 49.76 |
| Childcare [yes] (%) | 0 | 0.16 | 0.27 | 15.04 | 36.46 | 50.59 | 61.90 |
| Hospitalization for any cause (%) | 4.06 | 2.26 | 3.45 | 2.04 | 4.04 | 2.35 | 2.56 |
| Hospitalization for infection (%) | 0.73 | 1.79 | 2.85 | 1.79 | 3.06 | 2.04 | 2.01 |
| Chronic diseases (%) | 0.20 | 0.42 | 1.40 | 2.78 | 3.00 | 1.88 | 2.56 |
| Common conditions (n) | 595 | 1020 | 1186 | 504 | 301 | 223 | 163 |
| Common conditions (%) | |||||||
| Colic | 35.13 | 44.12 | 34.57 | 14.09 | 0.66 | 0.00 | 0.00 |
| Seborrheic dermatitis | 0.34 | 1.37 | 3.54 | 1.79 | 0.33 | 0.00 | 0.00 |
| Constipation | 6.39 | 10.00 | 10.29 | 26.39 | 30.90 | 36.77 | 48.47 |
| Frenulum | 2.18 | 0.59 | 0.51 | 0.20 | 0.00 | 0.00 | 0.00 |
| Gas | 0.50 | 0.78 | 0.51 | 0.20 | 0.00 | 0.00 | 0.00 |
| Jaundice | 9.58 | 0.78 | 0.25 | 0.00 | 0.00 | 0.00 | 0.00 |
| Food intolerance | 0.00 | 0.00 | 2.02 | 6.75 | 21.93 | 18.39 | 17.79 |
| Thrush | 3.03 | 3.63 | 5.73 | 8.73 | 10.96 | 12.11 | 4.29 |
| Weight loss/poor weight gain | 1.18 | 0.49 | 0.17 | 0.20 | 1.00 | 2.69 | 1.23 |
| Breastfeeding problems | 0.50 | 0.20 | 0.17 | 0.00 | 0.00 | 0.00 | 0.00 |
| Regurgitation | 36.97 | 32.35 | 36.00 | 33.73 | 13.62 | 5.38 | 0.20 |
| Vomits | 4.20 | 5.69 | 6.24 | 7.94 | 20.60 | 24.66 | 28.22 |
| Total illness episodes (n) | 33 | 120 | 903 | 2347 | 5035 | 4650 | 3794 |
| Diseases (%) | |||||||
| Tonsillitis | 0.0 | 0.20 | 0.00 | 0.64 | 0.18 | 0.00 | 0.00 |
| Bronchiolitis | 3.03 | 3.33 | 6.20 | 9.46 | 6.06 | 2.37 | 2.16 |
| Bronchitis | 0.00 | 0.00 | 0.33 | 1.70 | 3.99 | 4.34 | 4.72 |
| Conjunctivitis | 69.70 | 35.00 | 18.72 | 9.46 | 7.53 | 7.16 | 6.22 |
| Contact/allergic dermatitis | 3.03 | 6.67 | 2.44 | 1.45 | 0.00 | 0.00 | 0.00 |
| Atopic eczema/dermatitis | 0.00 | 0.83 | 20.27 | 13.34 | 7.83 | 6.52 | 7.56 |
| Rash illnesses | 0.00 | 0.00 | 0.33 | 18.27 | 4.25 | 4.92 | 4.24 |
| Dental/gum diseases | 0.00 | 0.00 | 0.22 | 0.64 | 1.23 | 1.16 | 1.56 |
| Wheezing episode | 0.00 | 0.00 | 2.66 | 4.35 | 4.75 | 4.82 | 5.75 |
| AP | 0.00 | 0.00 | 1.11 | 1.32 | 2.46 | 3.91 | 5.01 |
| Fever | 0.00 | 0.00 | 0.00 | 0.00 | 0.00 | 0.00 | 0.55 |
| AGE | 0.00 | 1.67 | 1.88 | 4.39 | 8.16 | 10.19 | 10.04 |
| Influenza | 0.00 | 0.00 | 0.00 | 0.00 | 0.00 | 0.00 | 0.500 |
| Laryngitis | 0.00 | 0.00 | 0.00 | 0.00 | 1.07 | 0.97 | 1.00 |
| Pneumonia | 0.00 | 0.00 | 0.22 | 0.09 | 0.71 | 0.60 | 0.79 |
| AOM | 0.00 | 0.00 | 1.22 | 3.49 | 8.08 | 10.13 | 9.38 |
| Common cold | 24.24 | 52.50 | 44.19 | 48.27 | 43.14 | 42.79 | 39.51 |
| Sinusitis | 0.00 | 0.00 | 0.22 | 0.17 | 0.56 | 0.41 | 0.69 |
| Viral infection | 0.00 | 0.00 | 0.00 | 0.00 | 0.00 | 0.00 | 0.32 |
Abbreviations: AGE: acute gastroenteritis; AOM: acute otitis media; AP: acute pharyngitis.
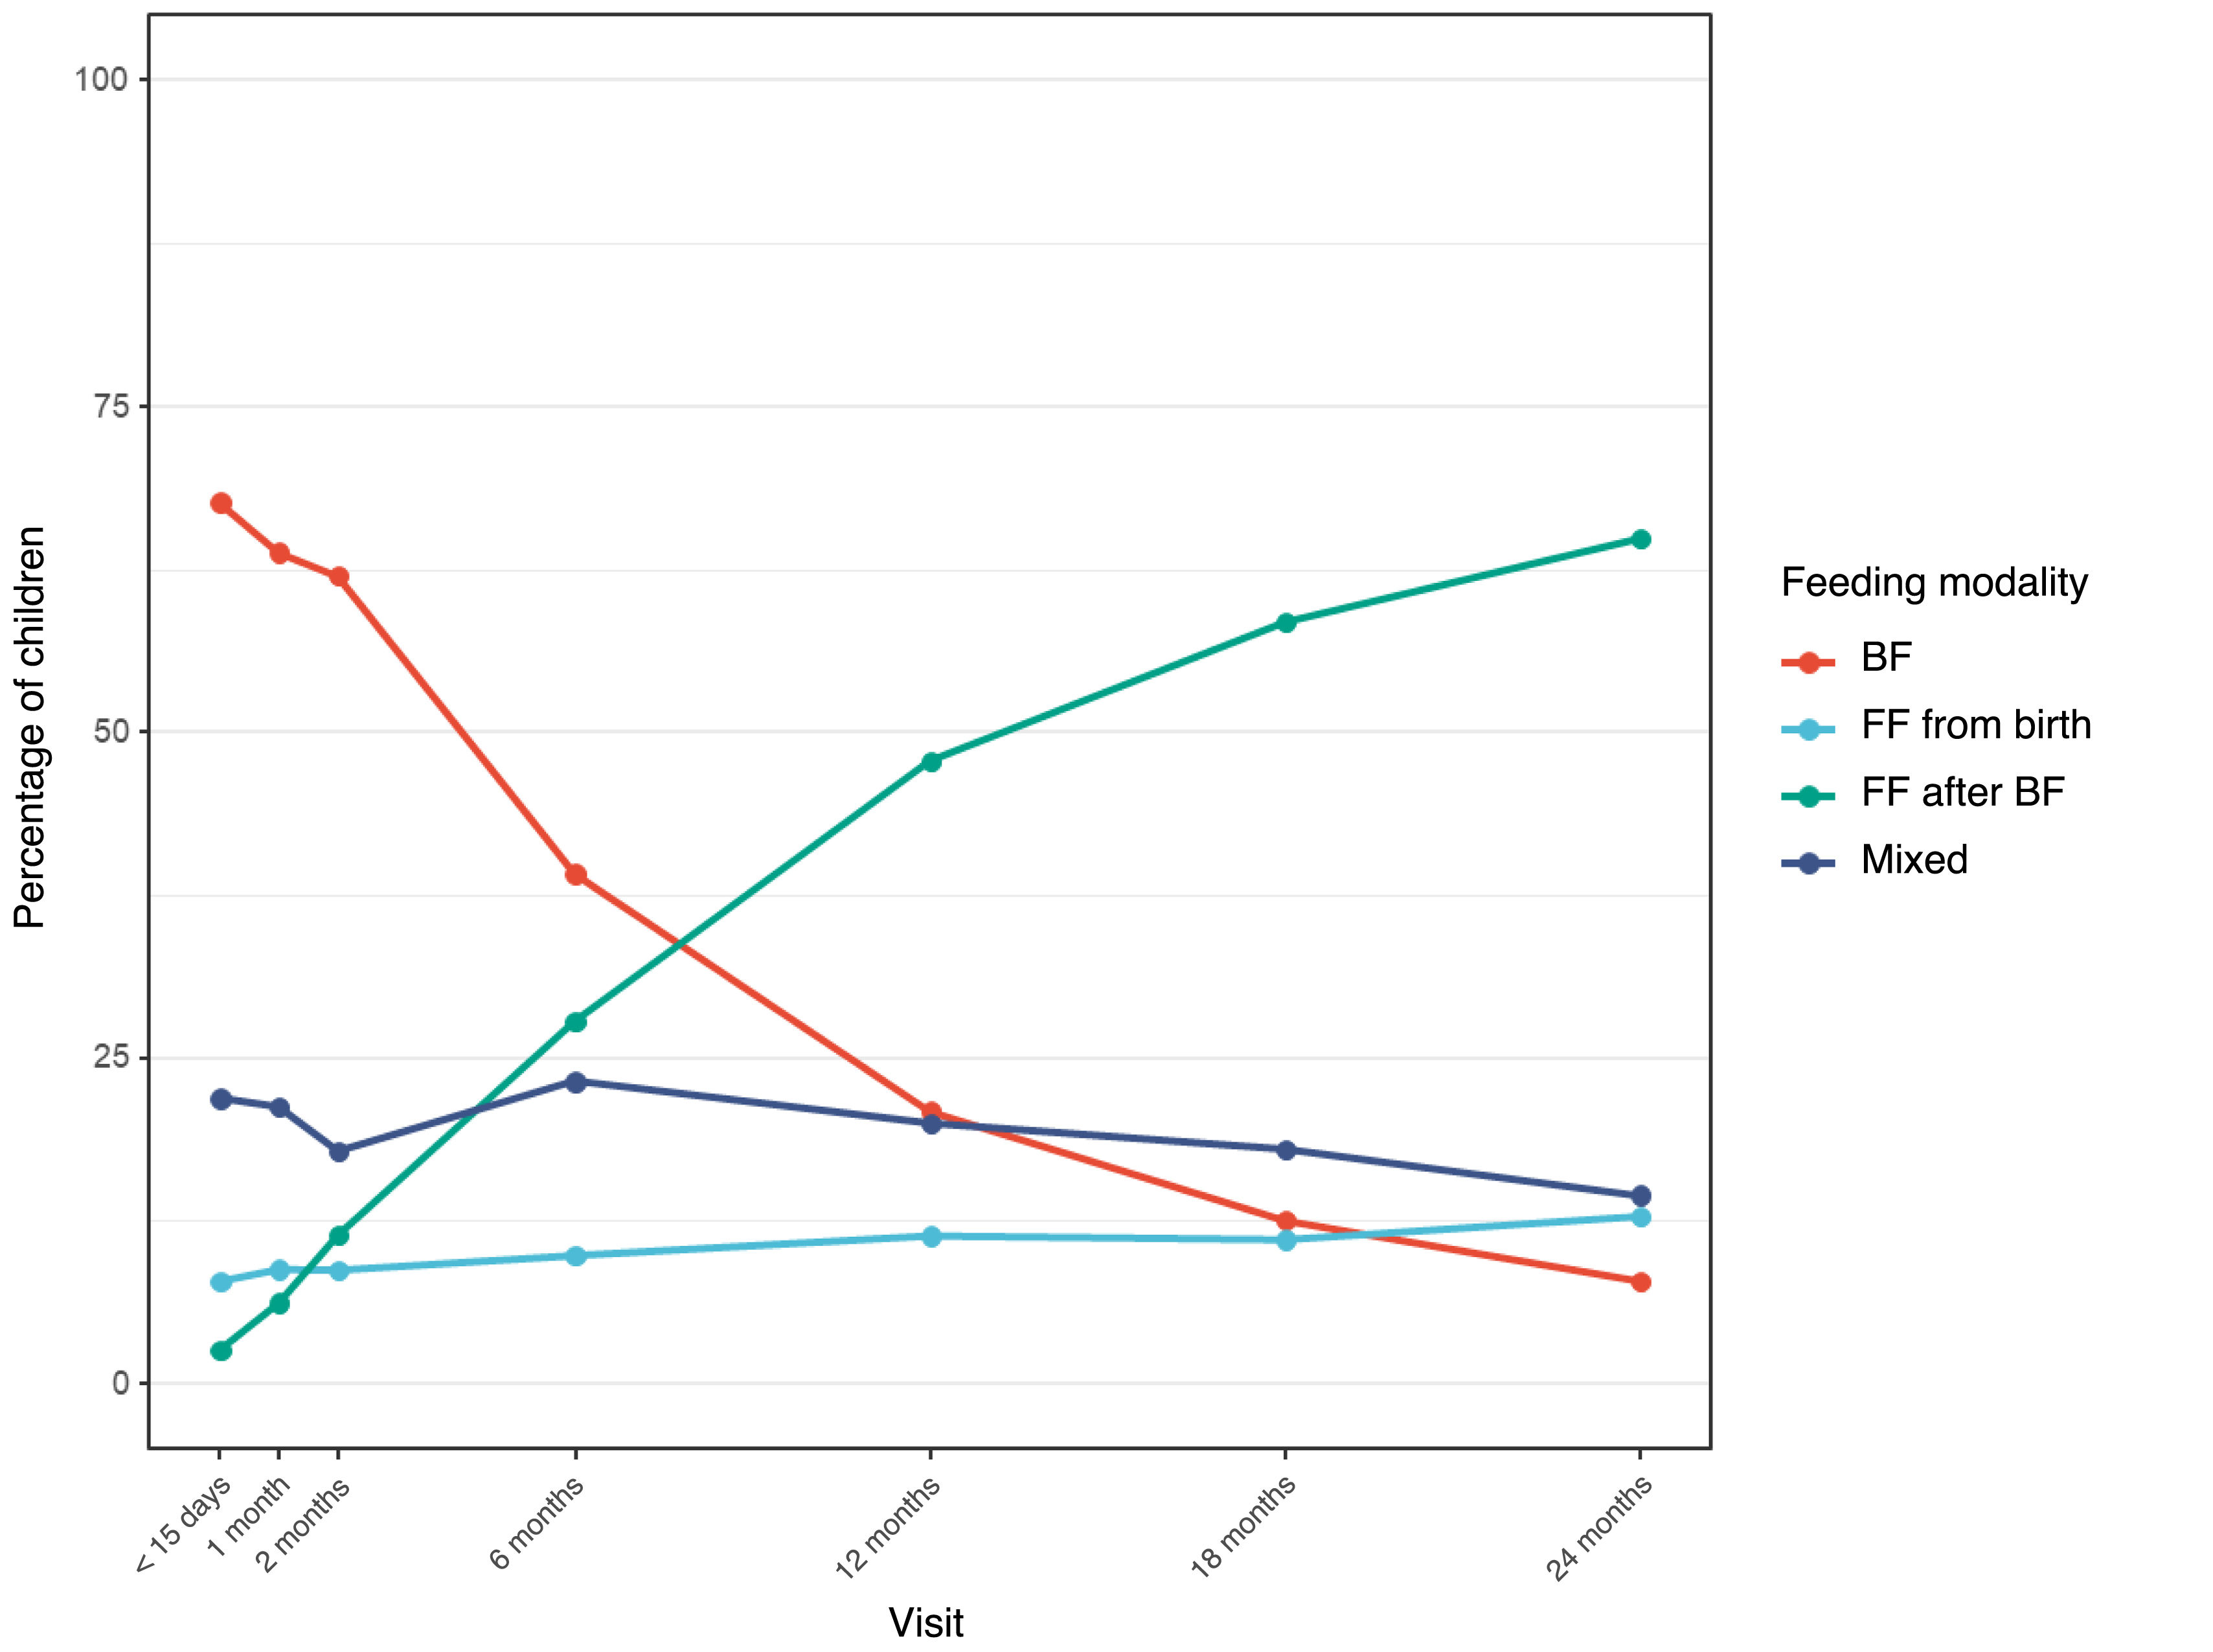
Mixed milk feeding and formula feeding from birth remained relatively stable during the follow-up period. Exclusive breastfeeding declined progressively from 2 months post birth (Fig. 1).

Before giving birth, 51.24% of mothers had expressed their intention to maintain BF for at least 6 months. At the first visit, the EBF rate was 67%, while at 6 months, the BF rate —including both EBF (39.26%) and MMF (23.29%)—remained around 62.25%. These figures were higher than expected.
MorbidityHospital admissionAt 2 months, the hospitalization rate was higher in the ever-breastfed group (FF_afterBF, 4.2%). There was a statistically significant association between hospitalization and infant feeding modality at 2 months (FF_afterBF) and at the <15-day visit (MMF).
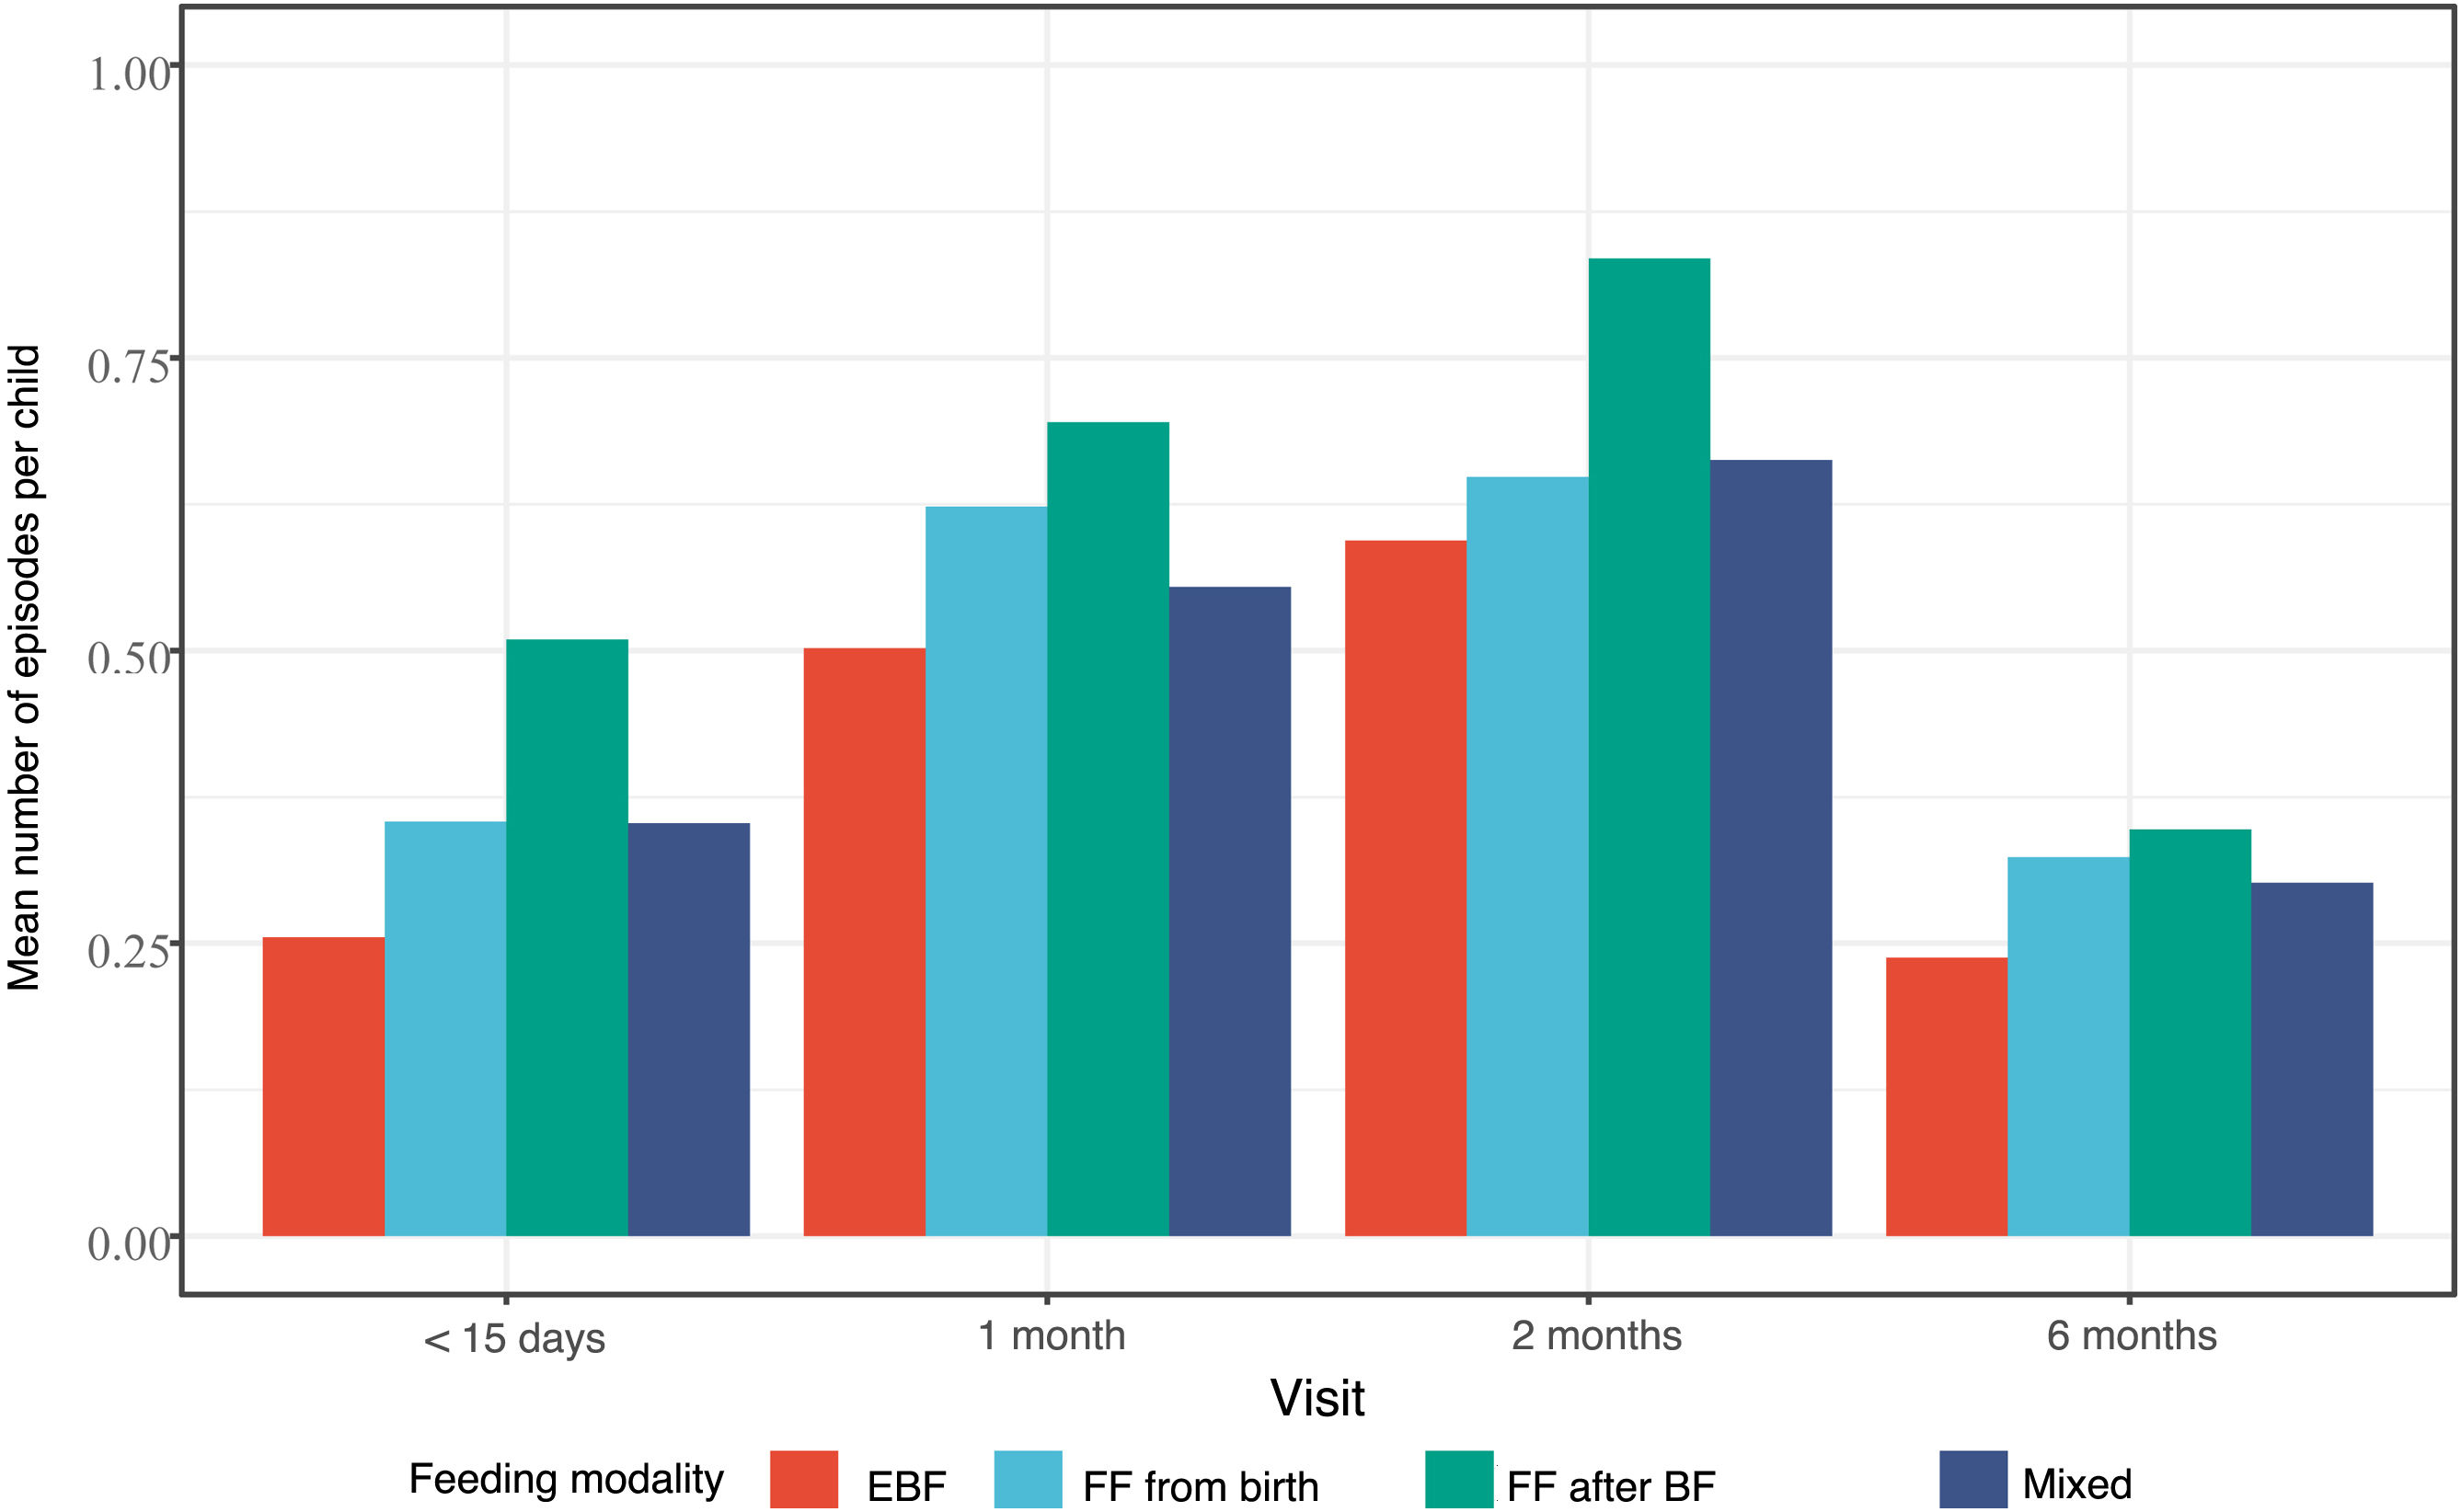
Common infant conditionsThey were more frequent in the first two months of life, with an overall protective effect of BF (Fig. 2). The most prevalent common infant conditions were colic, constipation, and regurgitation.

Exclusive BF exhibited a protective effect against colic at the <15 days, 1 month, and 2 months visits, whereas FF_afterBF acted as a risk factor at those ages (P < .001, P < .010, and P < .007, respectively), FF_frombirth at 2 months (P = .042), and MMF at < 15 days and 2 months (P = .006 and P = .001). Regurgitation was more frequent in never-breastfed infants with at age 1 month (FF_frombirth, P = .007) and ever-breastfed infants at 6 months (FF_afterBF, P = .005), compared to exclusively breastfed infants. Constipation showed a similar pattern, with EBF providing a protective effect during the first 3 visits and a higher risk associated with other feeding modalities, especially during the first 2 months (FF_frombirth: P < .001, P = .001 and P = .042; FF_afterBF: P < .001, P < .201 and P = .007; and MMF: P < .038, P < .001 y P = .01).
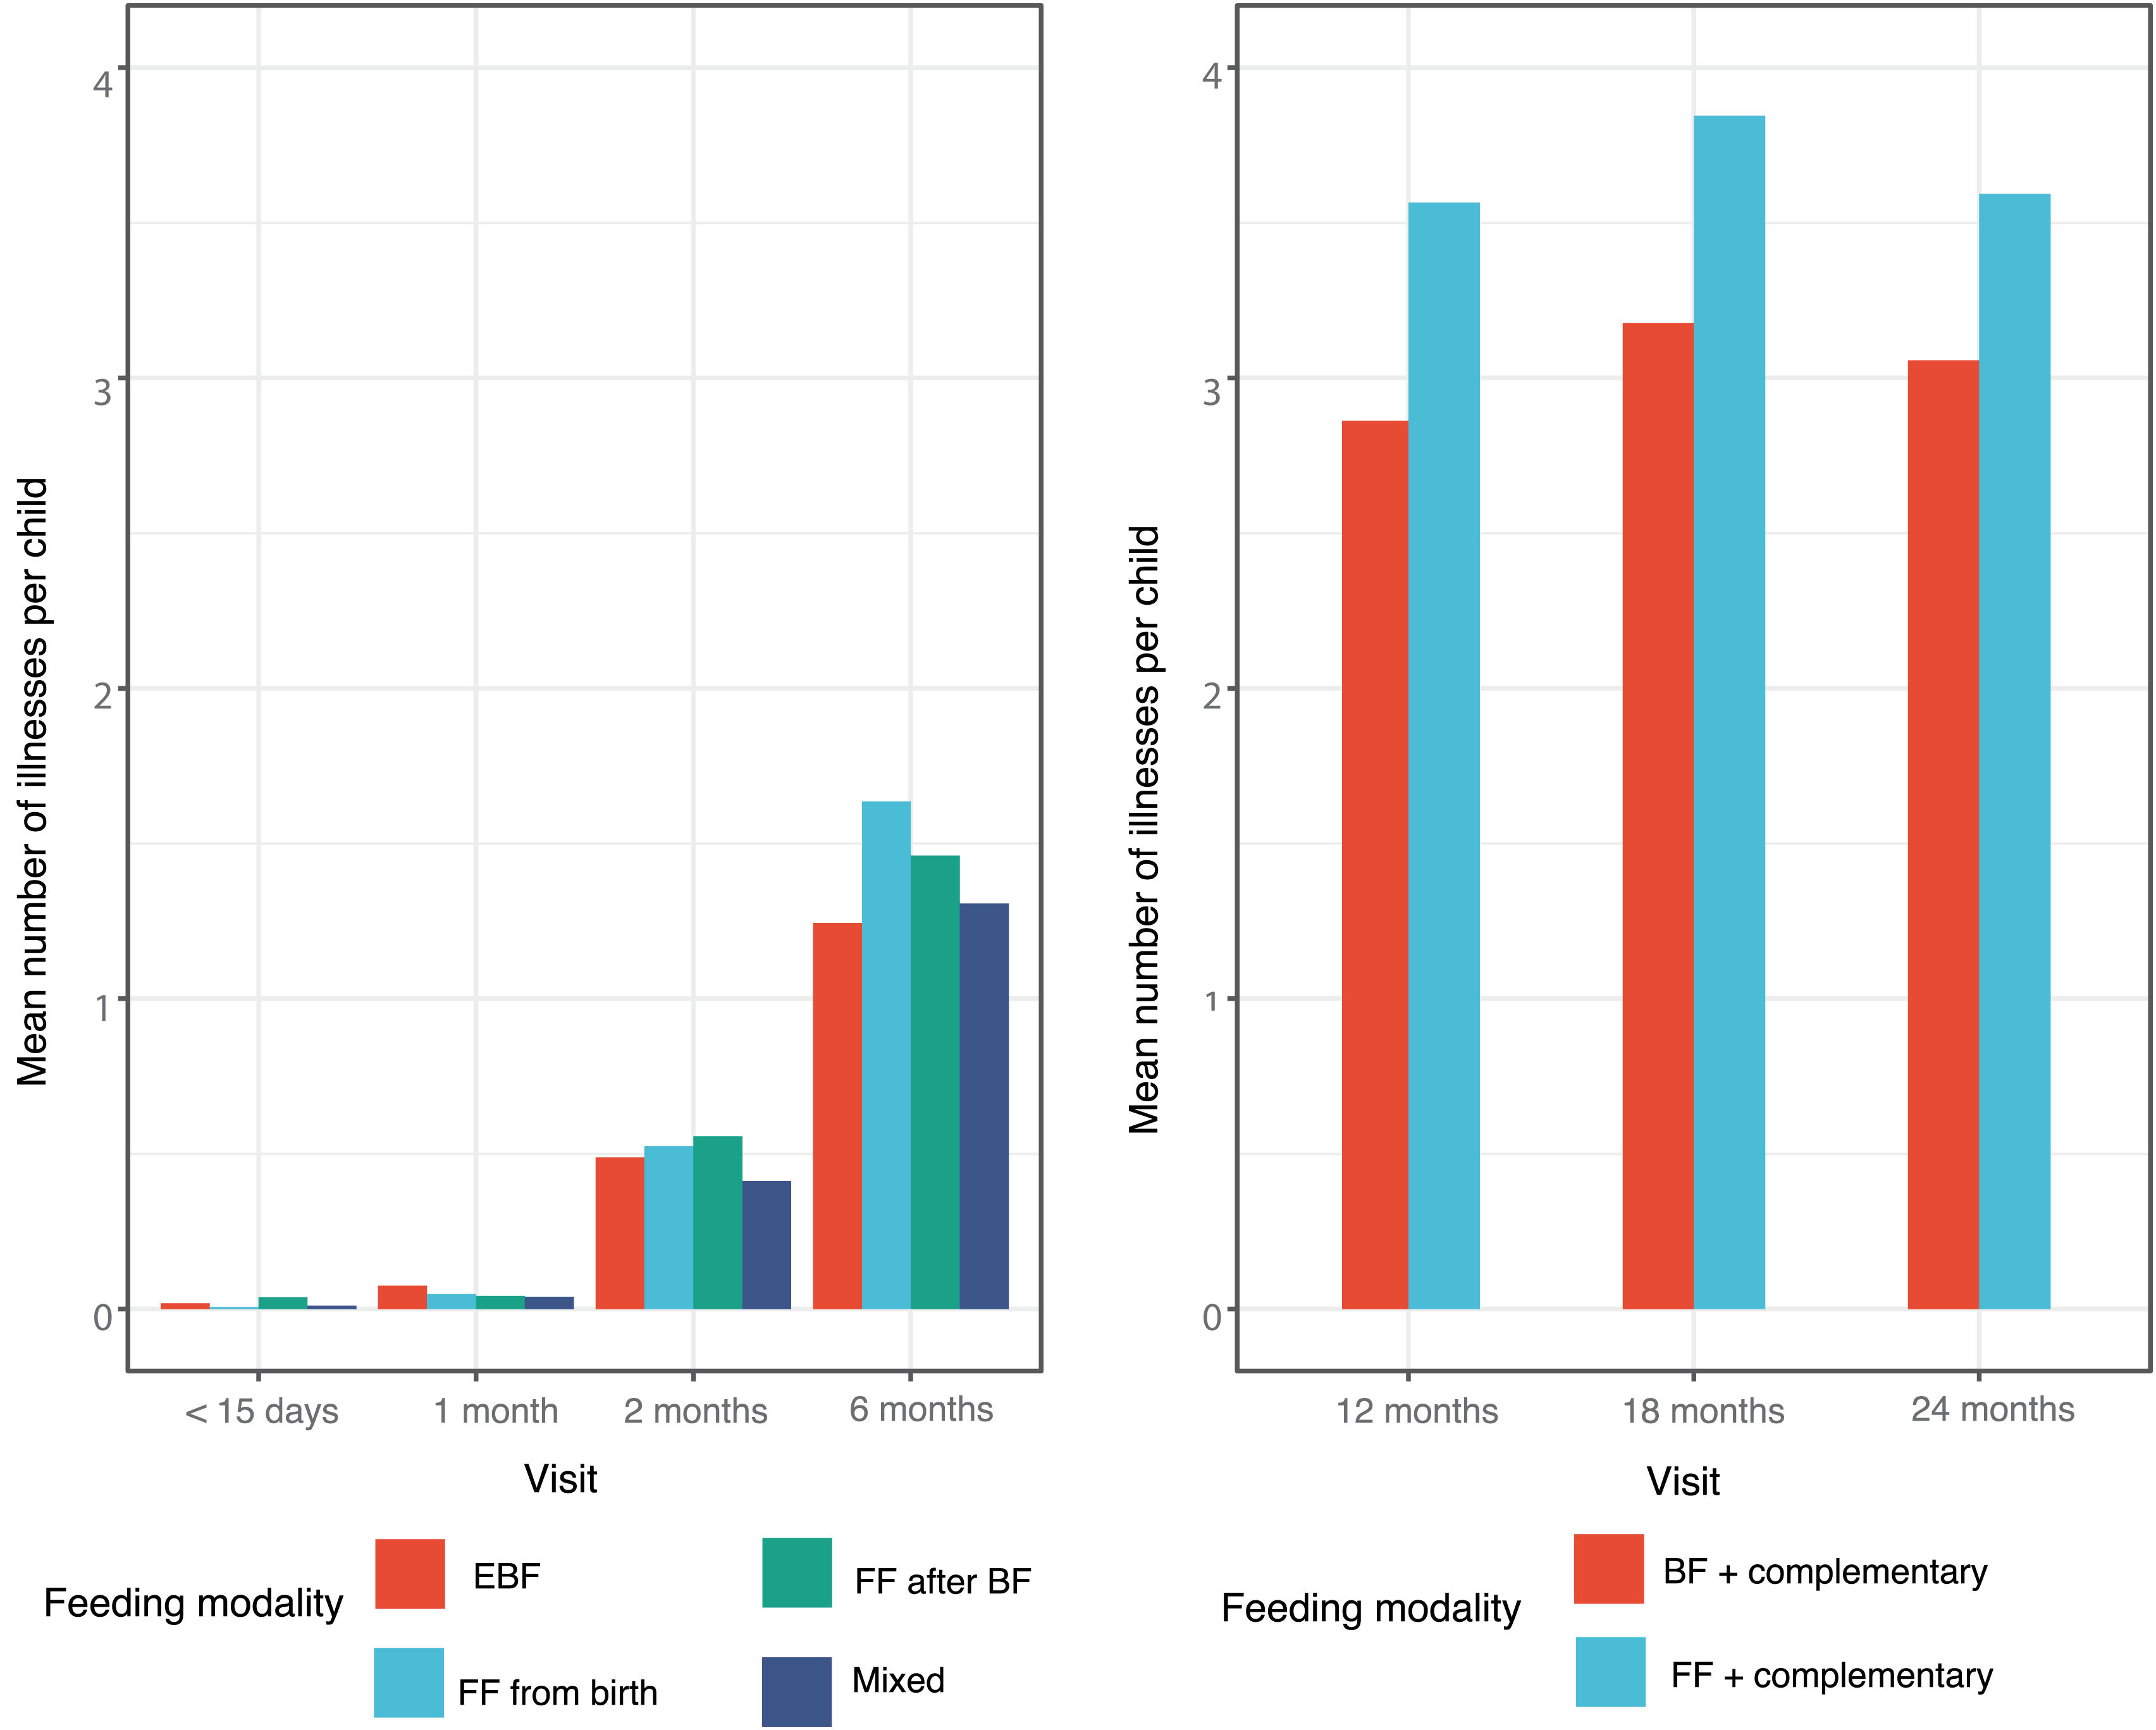
DiseaseThe prevalence of diseases increased progressively with age until age 18 months (Table 1). Starting at 6 months, the number of illness episodes per child was lower in the breastfed group (Fig. 3).

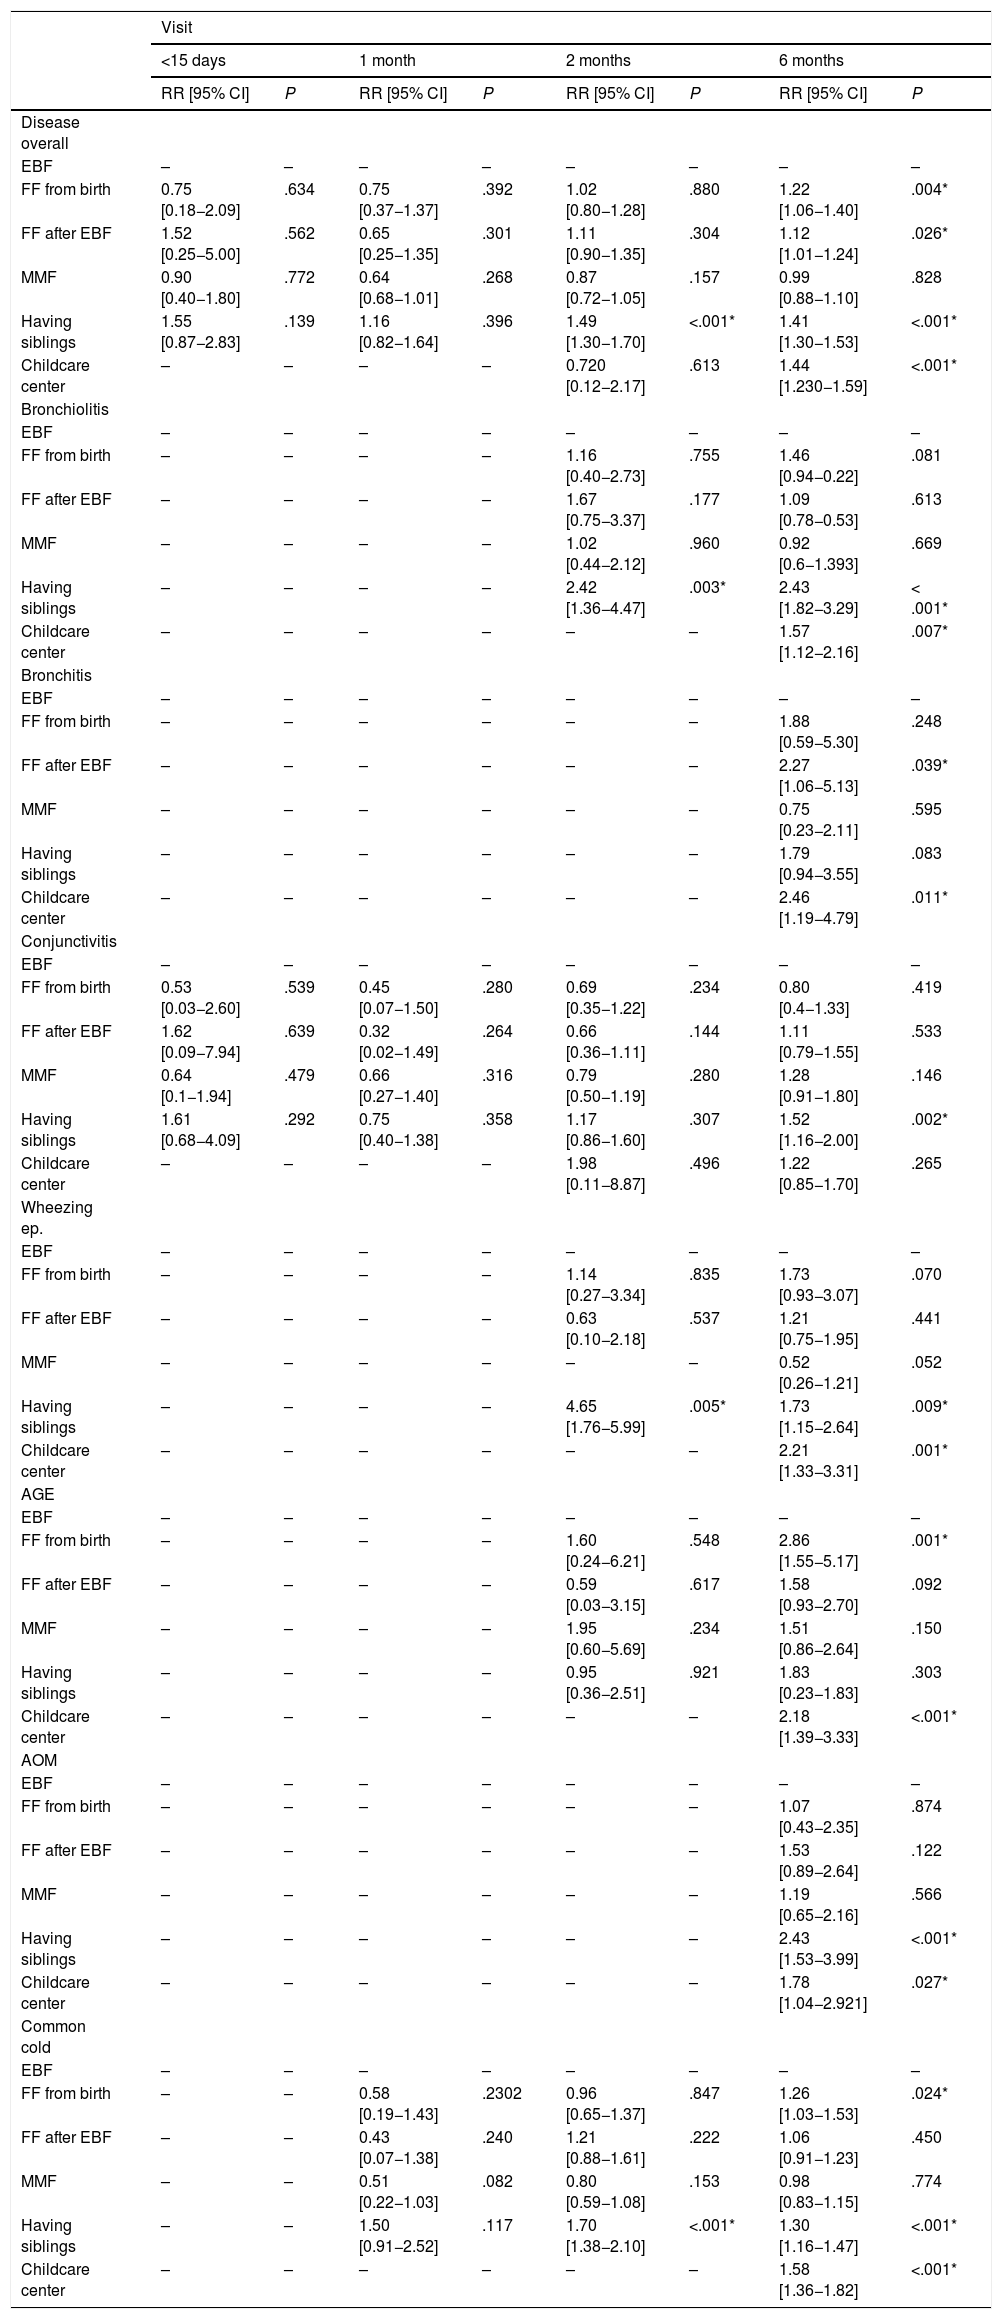
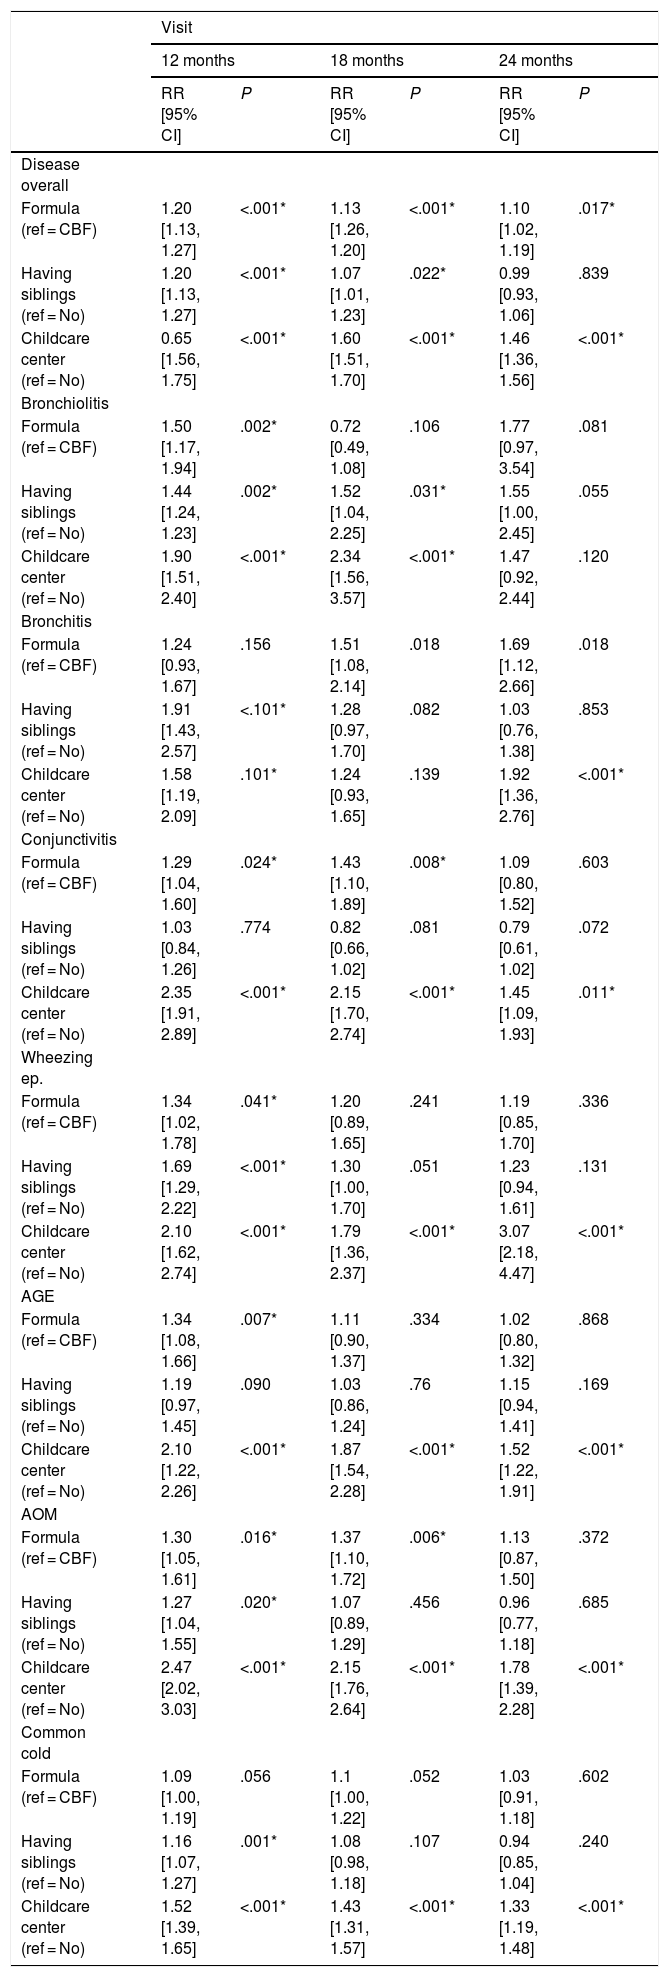
Table 2 (first 3 visits) and Table 3 (last 3 visits) present the most prevalent conditions, adjusted for infant feeding modality and confounding variables. Breastfeeding was associated with a lower risk of these diseases in every visit after age 6 months (12 months, P < .001), while FF_frombirth and FF_afterBF were risk factors at 6 months (P < .004 and P < .026, respectively) as was FF at 12, 18, and 24 months (P < .001, P < .001, and P < .017).
Frequency of disease at each visit (< 15 days–6 months) in relation to infant feeding modality and adjusted for confounding variables.
| Visit | ||||||||
|---|---|---|---|---|---|---|---|---|
| <15 days | 1 month | 2 months | 6 months | |||||
| RR [95% CI] | P | RR [95% CI] | P | RR [95% CI] | P | RR [95% CI] | P | |
| Disease overall | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | 0.75 [0.18−2.09] | .634 | 0.75 [0.37−1.37] | .392 | 1.02 [0.80−1.28] | .880 | 1.22 [1.06−1.40] | .004* |
| FF after EBF | 1.52 [0.25−5.00] | .562 | 0.65 [0.25−1.35] | .301 | 1.11 [0.90−1.35] | .304 | 1.12 [1.01−1.24] | .026* |
| MMF | 0.90 [0.40−1.80] | .772 | 0.64 [0.68−1.01] | .268 | 0.87 [0.72−1.05] | .157 | 0.99 [0.88−1.10] | .828 |
| Having siblings | 1.55 [0.87−2.83] | .139 | 1.16 [0.82−1.64] | .396 | 1.49 [1.30−1.70] | <.001* | 1.41 [1.30−1.53] | <.001* |
| Childcare center | – | – | – | – | 0.720 [0.12−2.17] | .613 | 1.44 [1.230−1.59] | <.001* |
| Bronchiolitis | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | – | – | – | – | 1.16 [0.40−2.73] | .755 | 1.46 [0.94−0.22] | .081 |
| FF after EBF | – | – | – | – | 1.67 [0.75−3.37] | .177 | 1.09 [0.78−0.53] | .613 |
| MMF | – | – | – | – | 1.02 [0.44−2.12] | .960 | 0.92 [0.6−1.393] | .669 |
| Having siblings | – | – | – | – | 2.42 [1.36−4.47] | .003* | 2.43 [1.82−3.29] | < .001* |
| Childcare center | – | – | – | – | – | – | 1.57 [1.12−2.16] | .007* |
| Bronchitis | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | – | – | – | – | – | – | 1.88 [0.59−5.30] | .248 |
| FF after EBF | – | – | – | – | – | – | 2.27 [1.06−5.13] | .039* |
| MMF | – | – | – | – | – | – | 0.75 [0.23−2.11] | .595 |
| Having siblings | – | – | – | – | – | – | 1.79 [0.94−3.55] | .083 |
| Childcare center | – | – | – | – | – | – | 2.46 [1.19−4.79] | .011* |
| Conjunctivitis | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | 0.53 [0.03−2.60] | .539 | 0.45 [0.07−1.50] | .280 | 0.69 [0.35−1.22] | .234 | 0.80 [0.4−1.33] | .419 |
| FF after EBF | 1.62 [0.09−7.94] | .639 | 0.32 [0.02−1.49] | .264 | 0.66 [0.36−1.11] | .144 | 1.11 [0.79−1.55] | .533 |
| MMF | 0.64 [0.1−1.94] | .479 | 0.66 [0.27−1.40] | .316 | 0.79 [0.50−1.19] | .280 | 1.28 [0.91−1.80] | .146 |
| Having siblings | 1.61 [0.68−4.09] | .292 | 0.75 [0.40−1.38] | .358 | 1.17 [0.86−1.60] | .307 | 1.52 [1.16−2.00] | .002* |
| Childcare center | – | – | – | – | 1.98 [0.11−8.87] | .496 | 1.22 [0.85−1.70] | .265 |
| Wheezing ep. | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | – | – | – | – | 1.14 [0.27−3.34] | .835 | 1.73 [0.93−3.07] | .070 |
| FF after EBF | – | – | – | – | 0.63 [0.10−2.18] | .537 | 1.21 [0.75−1.95] | .441 |
| MMF | – | – | – | – | – | – | 0.52 [0.26−1.21] | .052 |
| Having siblings | – | – | – | – | 4.65 [1.76−5.99] | .005* | 1.73 [1.15−2.64] | .009* |
| Childcare center | – | – | – | – | – | – | 2.21 [1.33−3.31] | .001* |
| AGE | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | – | – | – | – | 1.60 [0.24−6.21] | .548 | 2.86 [1.55−5.17] | .001* |
| FF after EBF | – | – | – | – | 0.59 [0.03−3.15] | .617 | 1.58 [0.93−2.70] | .092 |
| MMF | – | – | – | – | 1.95 [0.60−5.69] | .234 | 1.51 [0.86−2.64] | .150 |
| Having siblings | – | – | – | – | 0.95 [0.36−2.51] | .921 | 1.83 [0.23−1.83] | .303 |
| Childcare center | – | – | – | – | – | – | 2.18 [1.39−3.33] | <.001* |
| AOM | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | – | – | – | – | – | – | 1.07 [0.43−2.35] | .874 |
| FF after EBF | – | – | – | – | – | – | 1.53 [0.89−2.64] | .122 |
| MMF | – | – | – | – | – | – | 1.19 [0.65−2.16] | .566 |
| Having siblings | – | – | – | – | – | – | 2.43 [1.53−3.99] | <.001* |
| Childcare center | – | – | – | – | – | – | 1.78 [1.04−2.921] | .027* |
| Common cold | ||||||||
| EBF | – | – | – | – | – | – | – | – |
| FF from birth | – | – | 0.58 [0.19−1.43] | .2302 | 0.96 [0.65−1.37] | .847 | 1.26 [1.03−1.53] | .024* |
| FF after EBF | – | – | 0.43 [0.07−1.38] | .240 | 1.21 [0.88−1.61] | .222 | 1.06 [0.91−1.23] | .450 |
| MMF | – | – | 0.51 [0.22−1.03] | .082 | 0.80 [0.59−1.08] | .153 | 0.98 [0.83−1.15] | .774 |
| Having siblings | – | – | 1.50 [0.91−2.52] | .117 | 1.70 [1.38−2.10] | <.001* | 1.30 [1.16−1.47] | <.001* |
| Childcare center | – | – | – | – | – | – | 1.58 [1.36−1.82] | <.001* |
Abbreviations: AGE: acute gastroenteritis; AOM: acute otitis media; EBF, exclusive breastfeeding; FF, formula feeding; MMF, mixed milk feeding; RR, relative risk.
(−) Could not be evaluated due to low frequency of disease.
The 95% CI corresponds to the RR.
Diseases at each visit (12 to 24 months) in relation to infant modality and adjusted for confounding variables.
| Visit | ||||||
|---|---|---|---|---|---|---|
| 12 months | 18 months | 24 months | ||||
| RR [95% CI] | P | RR [95% CI] | P | RR [95% CI] | P | |
| Disease overall | ||||||
| Formula (ref = CBF) | 1.20 [1.13, 1.27] | <.001* | 1.13 [1.26, 1.20] | <.001* | 1.10 [1.02, 1.19] | .017* |
| Having siblings (ref = No) | 1.20 [1.13, 1.27] | <.001* | 1.07 [1.01, 1.23] | .022* | 0.99 [0.93, 1.06] | .839 |
| Childcare center (ref = No) | 0.65 [1.56, 1.75] | <.001* | 1.60 [1.51, 1.70] | <.001* | 1.46 [1.36, 1.56] | <.001* |
| Bronchiolitis | ||||||
| Formula (ref = CBF) | 1.50 [1.17, 1.94] | .002* | 0.72 [0.49, 1.08] | .106 | 1.77 [0.97, 3.54] | .081 |
| Having siblings (ref = No) | 1.44 [1.24, 1.23] | .002* | 1.52 [1.04, 2.25] | .031* | 1.55 [1.00, 2.45] | .055 |
| Childcare center (ref = No) | 1.90 [1.51, 2.40] | <.001* | 2.34 [1.56, 3.57] | <.001* | 1.47 [0.92, 2.44] | .120 |
| Bronchitis | ||||||
| Formula (ref = CBF) | 1.24 [0.93, 1.67] | .156 | 1.51 [1.08, 2.14] | .018 | 1.69 [1.12, 2.66] | .018 |
| Having siblings (ref = No) | 1.91 [1.43, 2.57] | <.101* | 1.28 [0.97, 1.70] | .082 | 1.03 [0.76, 1.38] | .853 |
| Childcare center (ref = No) | 1.58 [1.19, 2.09] | .101* | 1.24 [0.93, 1.65] | .139 | 1.92 [1.36, 2.76] | <.001* |
| Conjunctivitis | ||||||
| Formula (ref = CBF) | 1.29 [1.04, 1.60] | .024* | 1.43 [1.10, 1.89] | .008* | 1.09 [0.80, 1.52] | .603 |
| Having siblings (ref = No) | 1.03 [0.84, 1.26] | .774 | 0.82 [0.66, 1.02] | .081 | 0.79 [0.61, 1.02] | .072 |
| Childcare center (ref = No) | 2.35 [1.91, 2.89] | <.001* | 2.15 [1.70, 2.74] | <.001* | 1.45 [1.09, 1.93] | .011* |
| Wheezing ep. | ||||||
| Formula (ref = CBF) | 1.34 [1.02, 1.78] | .041* | 1.20 [0.89, 1.65] | .241 | 1.19 [0.85, 1.70] | .336 |
| Having siblings (ref = No) | 1.69 [1.29, 2.22] | <.001* | 1.30 [1.00, 1.70] | .051 | 1.23 [0.94, 1.61] | .131 |
| Childcare center (ref = No) | 2.10 [1.62, 2.74] | <.001* | 1.79 [1.36, 2.37] | <.001* | 3.07 [2.18, 4.47] | <.001* |
| AGE | ||||||
| Formula (ref = CBF) | 1.34 [1.08, 1.66] | .007* | 1.11 [0.90, 1.37] | .334 | 1.02 [0.80, 1.32] | .868 |
| Having siblings (ref = No) | 1.19 [0.97, 1.45] | .090 | 1.03 [0.86, 1.24] | .76 | 1.15 [0.94, 1.41] | .169 |
| Childcare center (ref = No) | 2.10 [1.22, 2.26] | <.001* | 1.87 [1.54, 2.28] | <.001* | 1.52 [1.22, 1.91] | <.001* |
| AOM | ||||||
| Formula (ref = CBF) | 1.30 [1.05, 1.61] | .016* | 1.37 [1.10, 1.72] | .006* | 1.13 [0.87, 1.50] | .372 |
| Having siblings (ref = No) | 1.27 [1.04, 1.55] | .020* | 1.07 [0.89, 1.29] | .456 | 0.96 [0.77, 1.18] | .685 |
| Childcare center (ref = No) | 2.47 [2.02, 3.03] | <.001* | 2.15 [1.76, 2.64] | <.001* | 1.78 [1.39, 2.28] | <.001* |
| Common cold | ||||||
| Formula (ref = CBF) | 1.09 [1.00, 1.19] | .056 | 1.1 [1.00, 1.22] | .052 | 1.03 [0.91, 1.18] | .602 |
| Having siblings (ref = No) | 1.16 [1.07, 1.27] | .001* | 1.08 [0.98, 1.18] | .107 | 0.94 [0.85, 1.04] | .240 |
| Childcare center (ref = No) | 1.52 [1.39, 1.65] | <.001* | 1.43 [1.31, 1.57] | <.001* | 1.33 [1.19, 1.48] | <.001* |
Abbreviations: AGE: acute gastroenteritis; AOM: acute otitis media; CBF, continued breastfeeding (with complementary foods); RR, relative risk.
In Table 3 (follow-up visits after 6 months), the infant feeding modalities are limited to FF and continued BF.
The analysis by disease revealed the following:
- •
Bronchiolitis: increased adjusted risk in formula-fed children at 12 months (P < .002); the identified risk factors were having siblings (at 2, 6, 12, and 18 months) and childcare attendance (at 6, 12, and 18 months).
- •
Bronchitis: greater adjusted risk associated with FF_afterBF at age 6 months (P = .039); the identified risk factors were having siblings (at age 12 months) and childcare attendance (at ages 6, 12, and 24 months).
- •
Episodes of wheezing: increased adjusted risk with formula feeding at 12 months (P = .041); the identified risk factors were also having siblings (at 2, 6, and 12 months) and childcare attendance (at 6, 12, 18, and 24 months).
- •
Acute gastroenteritis: greater adjusted risk associated with FF_frombirth at 6 months (P = .001) and with FF at 12 months (P = .007); childcare attendance increased risk at every analyzed age, but having siblings did not.
- •
Acute otitis media: greater adjusted risk associated with FF at 12 and 18 months (P < .016 and P < .006, respectively); the identified risk factors were having siblings (at ages 6 and 12 months), and childcare attendance (at 6, 12, 18, and 24 months).
- •
Acute conjunctivitis: greater adjusted risk associated with FF at 12 and 18 months (P = .002 and P < .001, respectively), having siblings did not affect risk, but childcare attendance increased risk at 6, 12, 18, and 24 months.
- •
Common cold: greater adjusted risk associated with FF_frombirth at 6 months (P = .024); having siblings was a risk factor at 2, 6, and 12 months, as was childcare attendance at 6, 12, 18, and 24 months.
- •
Atopic eczema/dermatitis: we did not identify an association with infant feeding modality or any of the confounding variables.
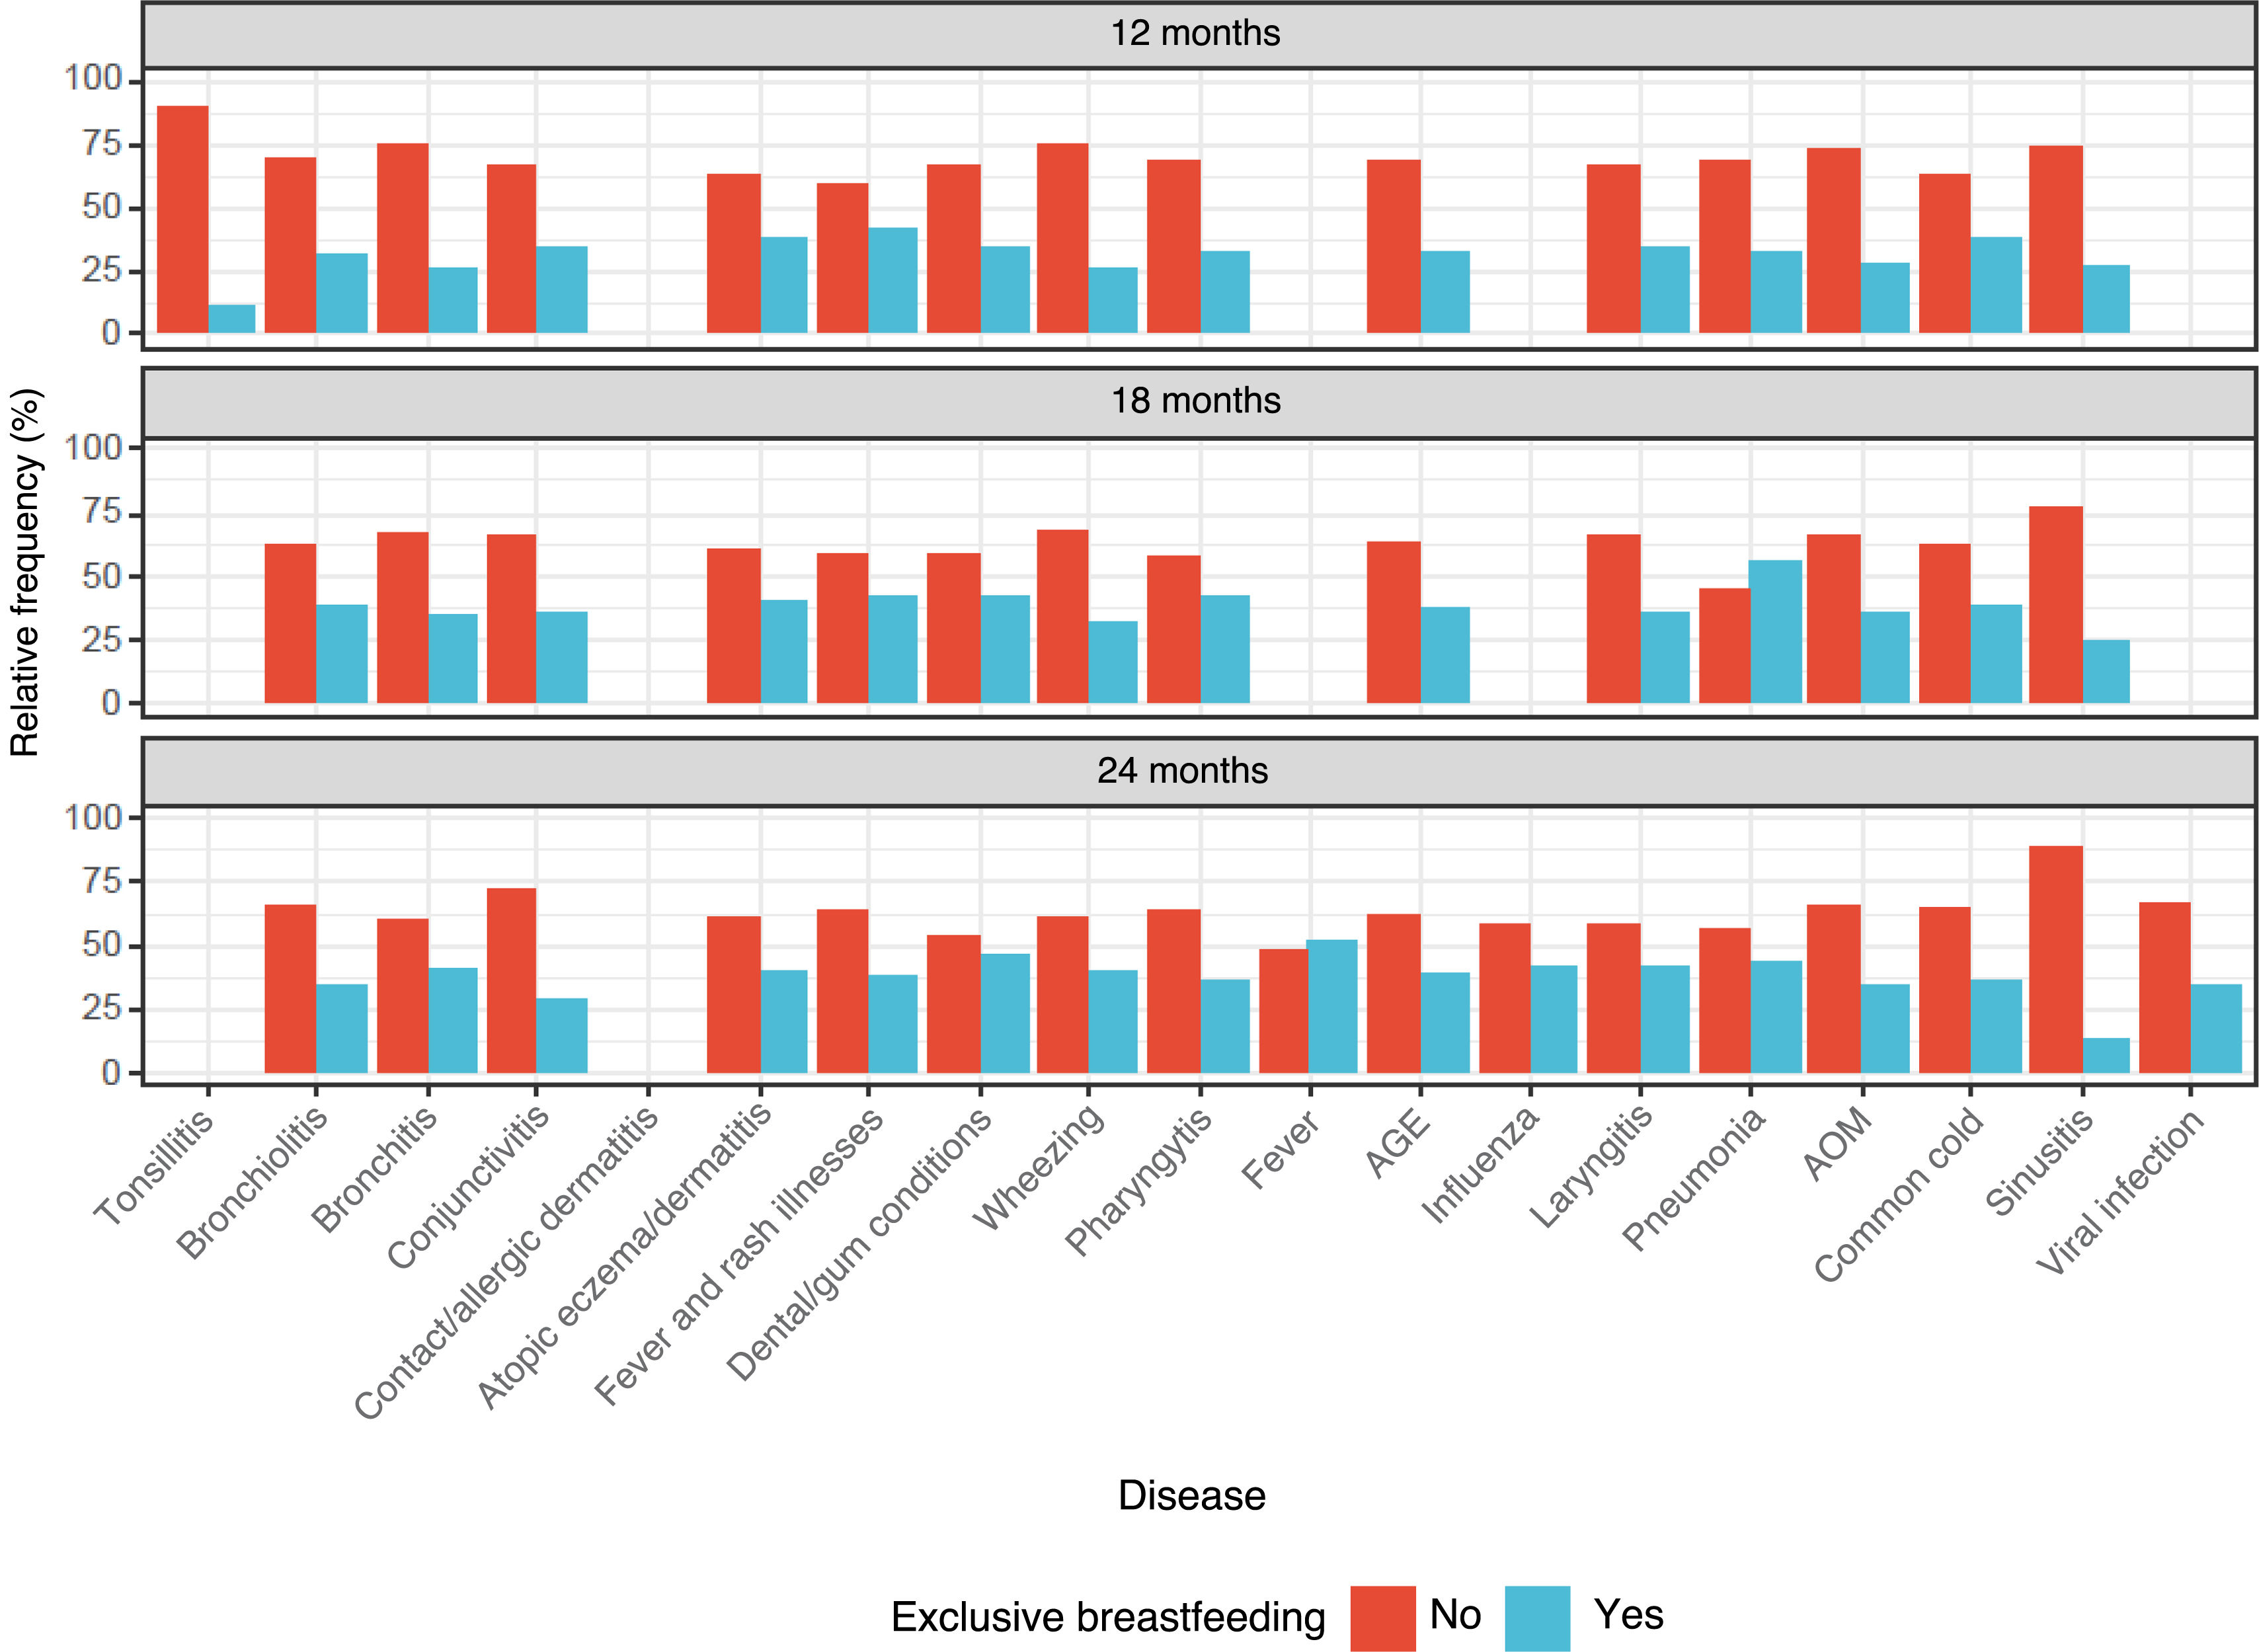
The prevalence of EBF_6m in the sample was 41.2%. The overall prevalence of disease in this group was lower (Fig. 4).

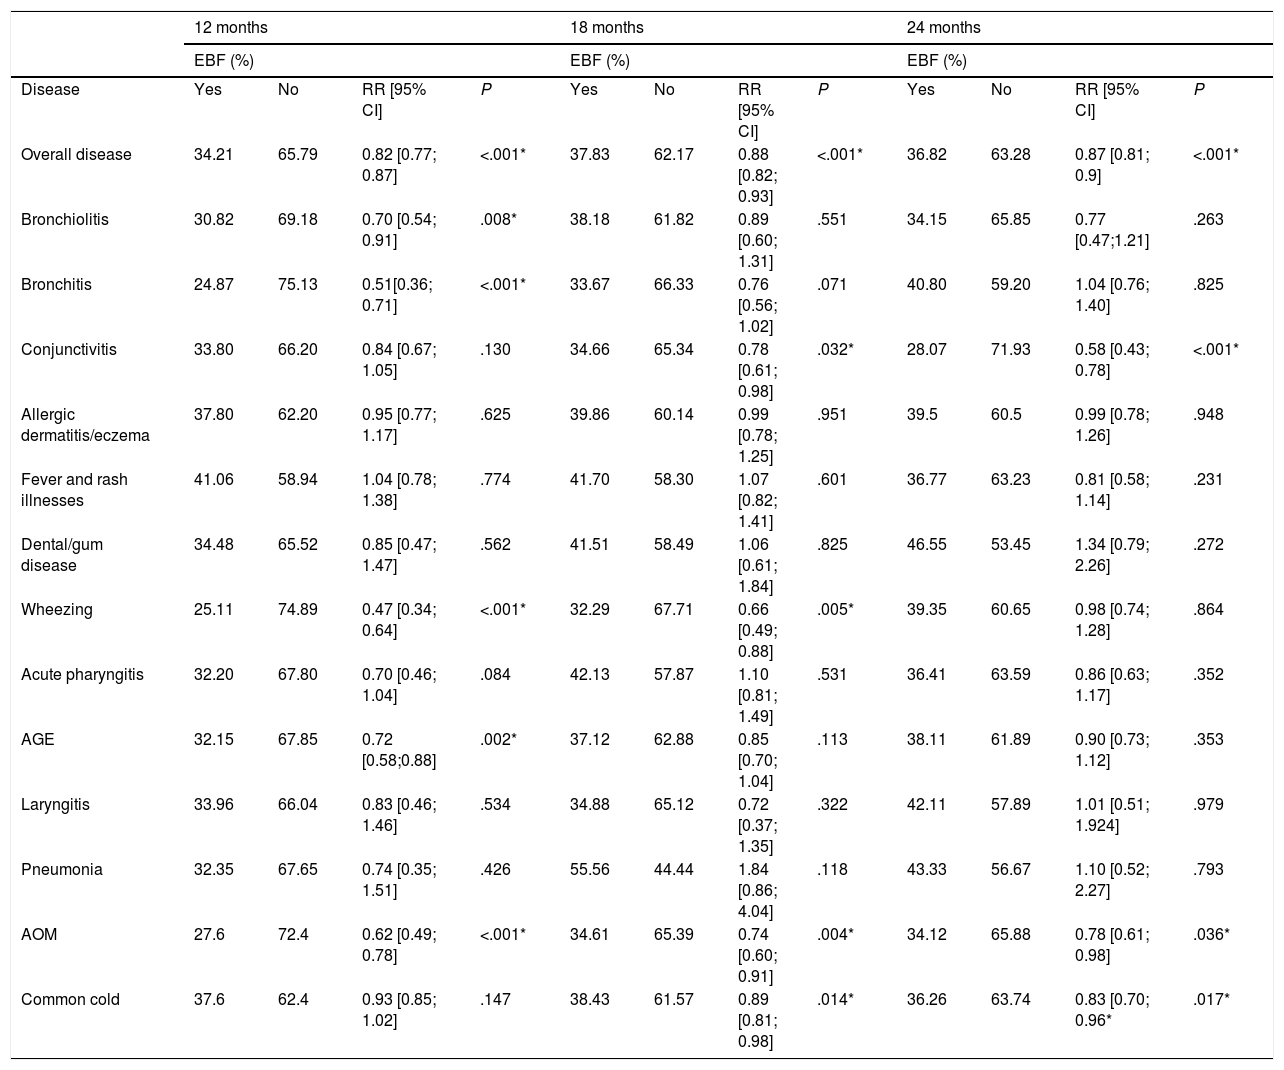
After adjusting for potential confounders, EBF_6m was associated with a lower overall risk of disease at 12, 18, and 24 months (Table 4), particularly for AOM, conjunctivitis, and the common cold (P < .001, P < .001, and P < .001 at ages 12, 18, and 24 months, respectively).
Impact of EBF on different diseases at ages 12, 18, and 24 months (adjusted for confounders).
| 12 months | 18 months | 24 months | ||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| EBF (%) | EBF (%) | EBF (%) | ||||||||||
| Disease | Yes | No | RR [95% CI] | P | Yes | No | RR [95% CI] | P | Yes | No | RR [95% CI] | P |
| Overall disease | 34.21 | 65.79 | 0.82 [0.77; 0.87] | <.001* | 37.83 | 62.17 | 0.88 [0.82; 0.93] | <.001* | 36.82 | 63.28 | 0.87 [0.81; 0.9] | <.001* |
| Bronchiolitis | 30.82 | 69.18 | 0.70 [0.54; 0.91] | .008* | 38.18 | 61.82 | 0.89 [0.60; 1.31] | .551 | 34.15 | 65.85 | 0.77 [0.47;1.21] | .263 |
| Bronchitis | 24.87 | 75.13 | 0.51[0.36; 0.71] | <.001* | 33.67 | 66.33 | 0.76 [0.56; 1.02] | .071 | 40.80 | 59.20 | 1.04 [0.76; 1.40] | .825 |
| Conjunctivitis | 33.80 | 66.20 | 0.84 [0.67; 1.05] | .130 | 34.66 | 65.34 | 0.78 [0.61; 0.98] | .032* | 28.07 | 71.93 | 0.58 [0.43; 0.78] | <.001* |
| Allergic dermatitis/eczema | 37.80 | 62.20 | 0.95 [0.77; 1.17] | .625 | 39.86 | 60.14 | 0.99 [0.78; 1.25] | .951 | 39.5 | 60.5 | 0.99 [0.78; 1.26] | .948 |
| Fever and rash illnesses | 41.06 | 58.94 | 1.04 [0.78; 1.38] | .774 | 41.70 | 58.30 | 1.07 [0.82; 1.41] | .601 | 36.77 | 63.23 | 0.81 [0.58; 1.14] | .231 |
| Dental/gum disease | 34.48 | 65.52 | 0.85 [0.47; 1.47] | .562 | 41.51 | 58.49 | 1.06 [0.61; 1.84] | .825 | 46.55 | 53.45 | 1.34 [0.79; 2.26] | .272 |
| Wheezing | 25.11 | 74.89 | 0.47 [0.34; 0.64] | <.001* | 32.29 | 67.71 | 0.66 [0.49; 0.88] | .005* | 39.35 | 60.65 | 0.98 [0.74; 1.28] | .864 |
| Acute pharyngitis | 32.20 | 67.80 | 0.70 [0.46; 1.04] | .084 | 42.13 | 57.87 | 1.10 [0.81; 1.49] | .531 | 36.41 | 63.59 | 0.86 [0.63; 1.17] | .352 |
| AGE | 32.15 | 67.85 | 0.72 [0.58;0.88] | .002* | 37.12 | 62.88 | 0.85 [0.70; 1.04] | .113 | 38.11 | 61.89 | 0.90 [0.73; 1.12] | .353 |
| Laryngitis | 33.96 | 66.04 | 0.83 [0.46; 1.46] | .534 | 34.88 | 65.12 | 0.72 [0.37; 1.35] | .322 | 42.11 | 57.89 | 1.01 [0.51; 1.924] | .979 |
| Pneumonia | 32.35 | 67.65 | 0.74 [0.35; 1.51] | .426 | 55.56 | 44.44 | 1.84 [0.86; 4.04] | .118 | 43.33 | 56.67 | 1.10 [0.52; 2.27] | .793 |
| AOM | 27.6 | 72.4 | 0.62 [0.49; 0.78] | <.001* | 34.61 | 65.39 | 0.74 [0.60; 0.91] | .004* | 34.12 | 65.88 | 0.78 [0.61; 0.98] | .036* |
| Common cold | 37.6 | 62.4 | 0.93 [0.85; 1.02] | .147 | 38.43 | 61.57 | 0.89 [0.81; 0.98] | .014* | 36.26 | 63.74 | 0.83 [0.70; 0.96* | .017* |
Abbreviations: AGE: acute gastroenteritis; AOM: acute otitis media; EBF, exclusive breastfeeding; RR, relative risk.
All coefficients adjusted for having siblings (yes/no) and childcare center attendance (yes/no).
Exclusive breastfeeding through age 6 months had a protective effect against bronchitis, bronchiolitis, wheezing and AGE at 12 months (P < .001, P = .008, P < .001, and P < .002). A similar trend was observed for wheezing at 18 months (P = .005). At 18 and 24 months, it had a protective effect against conjunctivitis (P = .032 and P < .001) and the common cold (P = .014 y P = .017) and at 12, 18, and 24 months, against AOM (P < .001, P < .004, and P < .036). Having siblings and childcare attendance increased the risk of infectious disease at 18 months, but not at 24 months.
DiscussionThis study corroborates the protective effect of BF against child morbidity during the first 2 years of life in a large, representative cohort followed up at the primary care level. The findings show that EBF through age 6 months, and any form of BF thereafter, is associated with a lower incidence of common conditions and infectious diseases in infancy and early childhood after adjusting for relevant confounding factors.
When it came to infant feeding, we found a proportion of EBF through age 6 months that was greater compared to previous reports in Spain,7 although still inferior to the target established by the WHO.8 The gradual decline in EBF rates after the first months of life was consistent with the findings of other studies conducted in developed countries, which also reported the protective effect of breastfeeding against infectious diseases,4,9,11,13–17,21,24,30 common infant conditions,14 and atopic dermatitis.31,32
Common infant conditions occurred more frequently in the first months of life, and we observed a clear protective effect of EBF against colic, regurgitation, and constipation. These findings are consistent with previous studies that reported a lower prevalence of digestive and functional disorders in breastfed children, especially in those exclusively breastfed in the first few months.14
From 6 months of age, BF was consistently associated with a fewer episodes of illness per child, chiefly on account of infectious diseases. The risk of developing bronchiolitis, bronchitis, episodes of wheezing, acute gastroenteritis, acute otitis media, conjunctivitis, and the common cold was greater among formula-fed children, results that remained significant after adjusting for having siblings and childcare attendance. Some studies conducted recently in developed countries12,16 have reported a protective effect of BF from earlier ages and stronger protection against hospitalization9,25,30,33 compared to our study.
The specific analysis of EBF through age 6 months revealed a medium-term protective effect that was observable through age 24 months, particularly for the most prevalent conditions, such as AOM, conjunctivitis, and the common cold. This finding supports the hypothesis of a persistent effect of EBF on the maturation of the immune system, as described by other authors,12,14,20,22,24,34–36 although the results varied depending on the definition and duration of BF contemplated in each study.6,9,11,13–16,19,21–23,33,37,38 The risk of AGE in never-breastfed children is high in countries with different levels of development.6,16,18 We found that EBF_6m had a protective effect against AGE in the medium term (through age 12 months), independently of continuation of BF thereafter, contrary to what has been reported by other authors,12 who found the protection against AGE to be limited to the period of BF.
The analyzed confounding variables had an independent impact on morbidity, particularly childcare attendance and, to a lesser extent, having siblings. These factors have been previously described as determinants of infectious risk in childhood, and their inclusion in the models reinforces the robustness of the observed outcomes. Previous studies have provided evidence on the role of other variables.9,12–15,17,23,24,34 In this study, we did not include maternal age in the analysis, as less than 0.2% of mothers in the sample were younger than 20 years. We also chose not to include the season of birth, since infants were recruited every month of the year, and sex, as the sex distribution of the infants was nearly uniform (50.2% male vs 49.2% female).
We did not find an association between infant feeding modality and atopic eczema or dermatitis, consistent with several previous studies.31,32 The lack of data about the family history of atopy in our cohort could explain the discrepancies with studies that describe a protective effect of EBF in specific subgroups.39,40
One of the main strengths of the study is that the participating primary care pediatricians collected data on their own patients (longitudinal follow-up). All participating providers belonged to a structured national research network, ensuring the use of homogeneous diagnostic criteria, and since pediatric primary care in Spain is generally provided by pediatricians, the sample was representative of the entire pediatric population. This health care context lends the results a high degree of external validity. Although some children were lost to follow-up, the losses were moderate and primarily due to changes of address, and too small to compromise the findings in terms of the estimated minimum sample size.
The limitations of the study include losses to follow-up, partial reliance on information provided by parents, and the inability to analyze other potential confounding variables, such as socioeconomic factors, sex, or family history. However, its prospective design and sample size, the preexisting knowledge that pediatricians had of their own patients, and the homogeneity of the diagnostic criteria partially mitigate these limitations.
Overall, the findings support the current recommendations to promote breastfeeding—especially exclusive breastfeeding through age 6 months—as an effective strategy for reducing morbidity in the first 2 years of life, even in developed health care systems.
ConclusionsBreastfeeding, and particularly EBF through age 6 months, is associated with a lower incidence of common infant conditions in the first months of life, such as colic, regurgitation, and constipation.
From age 6 months, ever-breastfed children, whether exclusively or not, have fewer health problems—primarily infectious diseases—compared to formula-fed children.
Exclusive breastfeeding through age 6 months has a protective effect in the medium term, observable up to age 24 months, against all of the 19 conditions that were studied, and particularly against the most prevalent ones, such as acute otitis media, acute conjunctivitis, wheezing, and the common cold.
These findings underscore the importance of promoting and supporting breastfeeding—especially exclusive breastfeeding during the first 6 months of life—as an effective intervention for reducing common childhood diseases in the first 2 years of life, even in developed health care systems.
FundingThe LAYDI study received a research grant from the Asociación Española de Pediatría de Atención Primaria-Fundación Pediatría y Salud (AEPap-FPS) as part of its 2017 call for research proposals.
The authors have no conflicts of interest to declare.
This study is the result of a joint effort by collaborating pediatricians and coordinators of the PAPenRED national network, whom we thank for their selfless dedication to research in primary care. Below is a list of the professionals who collaborated with the network on this study: Abad Balaguer B, Acitores Suz E, Acosta Navas B, Aguilera López L, Albaladejo Beltrán S, Albañil Ballesteros MR, Alcaraz Quiñonero M, Álvarez Bueno E, Angulo Moreno ME, Anllo Lago J, Aparicio Rodrigo M, Arana Cañedo-Argüelles C, Arranz Sanjuan R, Arroyo Úbeda R, Asensi Monzo MT, Astiz Blanco MI, Azor Martínez E, Balaguer Martínez JV, Baliela García BC, Barea García JJ, Barrios González EM, Batalla Fadó L, Bejarano López MA, Belda García MT, Benítez Rubio MR, Bercedo Sanz A, Bernad Usoz JV, Biosca Pàmies M, Blesa Baviera LC, Bombín Granado JM, Bonet Garrosa A, Botella Serrano B, Bravo Acuña J, Bretón Peña AI, Burgaleta Sagaseta AM, Cairó Corominas S, Calvo Lorenzo MT, Canadell Villaret D, Carballal Mariño M, Carmona Cedrés N, Carrera Polanco M, Carretero Carretero L, Casado Sánchez MI, Casares Alonso I, Castillo Marcalain A, Caubet Busquet I, Cayuela Guerrero C, Ciriza Barea E, Coto Fuente MM, Cruz Navarro I, De Haro López MA, De La Serna Higuera PM, Del Castillos Aguas G, Del Toro Calero C, Diaz Cirujano AI, Díaz Pedrouzo A, Díez Zaera O, Domínguez Aurrecoechea B, Duelo Marcos M, Edo Jimeno MJ, Elorz Ibáñez AC, Escanciano García Y, Escribano Romero MJ, Esparza Olcina MJ, Espinazo Ramos O, Espínola Docio B, Esquivel Ojeda JN, Fabregat Ferrer E, Fernández Francés M, Fernández León A, Fernández López FJ, Fernández Pastor F, Fernández Rodríguez M, Fernández Segura ME, Ferrándiz Cerdá B, Flores Erro U, Galán Calvo MJ, Galán Rico J, Galardi Andonegui MS, Gallego Iborra A, Garach Gómez A, García Arroyo I, García Lara GM, García Mérida MJ, García Merino A, García Pérez R, García Rebollar CA, García Santiago M, García-Onieva Artázcoz M, García Vera C, Garnelo Suarez L, Garrido Redondo M, Gatell Carbo A, Gil Alexandres I, Giribet Folch M, Gómez Casares R, Gómez Sorrigueta P, González Marcos MI, González Rodríguez MP, Gracia Alfonso MA, Grau García AI, Gutiérrez Abad C, Heras Galindo JA, Hernández Ortiz MY, Hernando Helguero P, Herrero Rey S, Iribarren Udobro I, Jaramillo Hidalgo D, Jiménez Alés R, Jiménez Hereza JM, Jové Naval J, Juanes De Toledo B, Ledesma Albarrán JM, Lobera Navaz P, López Alonso R, López Vilar P, Lorente García-Mauriño A, Manero Oteiza A, Marco Puche A, Marfil Olink S, Márquez Moreno MD, Martín Carballo G, Martín Cuesta B, Martín Ibáñez I, Martín Peinador Y, Martín Rial S, Martínez Espligares L, Martínez Moral N, Martínez Rubio MV, Martínez Ruiz MM, Menéndez Bada T, Menéndez González N, Mengual Gil J, Merino Villeneuve I, Mínguez Verdejo R, Miranda Berrioategortua I, Moneo Hernández I, Monje C, Montañés Sánchez AM, Montes Peña M, Montoro Romero MS, Monzón Bueno AI, Morell Bernabé JJ, Muñoz García NP, Muñoz Hiraldo ME, Mustieles Moreno C, Navarro Cabañas G, Navas Heredia CM, Nóvoa García E, Oliva Alfonso A, Olmos García JM, Ordoñez Alonso MA, Padilla Esteban ML, Padilla Sánchez MC, Palomares Gimeno MJ, Palomino Urda N, Panizo Santos MB, Parejo Carranza R, Pavía Lafuente M, Pavo García MR, Peix Sambola MA, Peñarroja Peirats S, Pérez Candás JI, Pérez de Saracho Taramona M, Pérez Gavilán J, Puig García C, Puyuelo Del Val P, Quintanilla Sánchez MM, Ramos Zugasti M, Rey Del Castillo C, Ribera Sirvent C, Ripoll Lozano A, Rivas Abraldes N, Riveros Huckstadt MP, Robles García J, Rodríguez Delgado J, Rodríguez Fernández MM, Rodríguez Fernández-Oliva CR, Rodríguez Pérez EG, Rodríguez Santana Y, Rodríguez-López Márquez GA, Rodríguez-Salinas Pérez E, Rojo Portolés P, Rubio Remiro O, Ruiz-Cuevas García P, Ruiz Chércoles E, Sáenz de Urturi Sánchez A, Sáez de Lafuente Arriazu A, Salcedo Pacheco I, Sánchez Almeida E, Sánchez Andrés MT, Sánchez Calderón M, Sánchez Cordero N, Sánchez Díaz MD, Sánchez Echenique M, Sánchez Fuentes V, Sánchez González B, Sánchez Jiménez MC, Sánchez Pina C, Sánchez Precioso S, Sánchez-Prieto Emmanuel I, Sancho Madrid B, Satrústegui Gamboa F, Serna Saugar MC, Servera Ginard CI, Suárez Vicent E, Surribas Murillo C, Torres Álvarez de Arcaya ML, Valerio Hernández E, Vaquerizo Pollino MJ, Vega Pérez MS, Velasco Guijarro O, Viar Urieta M, Villafruela Álvarez C, Villaizán Pérez C, Viver Gómez S.



