



The chimeric monoclonal antibody infliximab, which targets tumor necrosis factor alpha (TNF-α), plays a central role in the management of arthritis, effectively reducing inflammation and clinical symptoms. It is administered intravenously as an infusion every 4 to 8 weeks following induction therapy.
Drug desensitization protocols aim to induce temporary tolerance to drug antigens. Rapid drug desensitization is an essential procedure that allows the maintenance of first-line therapies and has demonstrated good safety and efficacy.
Desensitization protocols for infliximab in adults have been described, based on standardized three-solution or single-solution protocols, with satisfactory outcomes.1–3 In the pediatric population, drug desensitization has become an increasingly common procedure and several studies have described intravenous desensitization protocols with sequential infusion of three bags of solution.1,3,4 One-bag desensitization protocols have been reported for tocilizumab.5 Additionally, two pediatric cases involving children aged 9 and 10 years have been described, in which desensitization to infliximab was successfully performed using an 11-step protocol without premedication, starting at a concentration of 1 mg/mL and progressively increasing doses from 2 µg to 80 mg.2,6
We report a successful 15-step one-bag infliximab desensitization protocol in a patient aged 4 years who experienced a severe immediate anaphylactic reaction. We obtained written informed consent from the parents to publish this case.
The patient was a boy aged 4 years with a diagnosis of arthritis associated with proliferative synovitis, steroid dependence, and refractoriness to adalimumab and etanercept. Due to a partial response to treatment, persistent impairment in quality of life, and ongoing steroid dependence, off-label infliximab was prescribed at a dose of 8.3 mg/kg (100 mg) every 2 weeks to achieve disease control. Immediately after the start of the third infusion, at a rate of 80 mL/hour, the patient developed vomiting, dyspnea, cyanosis and hypoxemia (oxygen saturation of 90%). The infusion was immediately discontinued, and oxygen therapy was administered until symptoms resolved. Reinitiation of the infusion at a slower rate (40 mL/hour) resulted in pruritus and urticaria, leading to permanent discontinuation of infliximab. The patient was treated with dexchlorpheniramine, acetaminophen, and intravenous fluids.
Due to the severity of the reaction, the clinical improvement with infliximab, and the lack of response to other treatments, the patient was referred to the allergy department for further evaluation.
Written informed consent from the parents was obtained prior to skin testing, which was performed three weeks after the reactions to minimize the likelihood of false-negative results. Skin prick testing with infliximab (10 mg/mL) and intradermal testing (10 mg/mL and 1 mg/mL) were both negative. Considering the severity of the previous reaction and the lack of therapeutic alternatives, desensitization to infliximab was proposed.
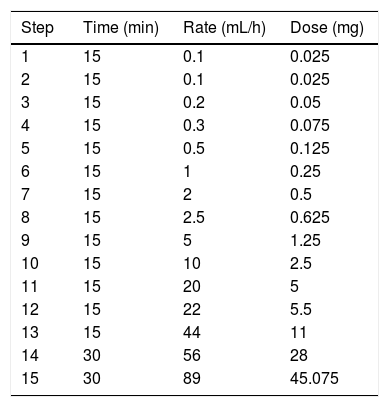
A single-bag, 15-steps desensitization protocol was performed, starting at 0.025 mL and gradually increasing the infusion rate every 15 minutes until a cumulative dose of 100 mg was delivered (Table 1). Pretreatment included aspirin and montelukast, initiated 48 hours before the procedure, and premedication with prednisolone, dexchlorpheniramine, acetaminophen, aspirin, montelukast, and famotidine administered 30 minutes prior to infusion. The desensitization was completed without incident. A second identical cycle was also well tolerated; however, treatment was subsequently discontinued due to therapeutic failure.
Desensitization protocol for infliximab. Desensitization schedule for 1 mg/mL concentration.
| Step | Time (min) | Rate (mL/h) | Dose (mg) |
|---|---|---|---|
| 1 | 15 | 0.1 | 0.025 |
| 2 | 15 | 0.1 | 0.025 |
| 3 | 15 | 0.2 | 0.05 |
| 4 | 15 | 0.3 | 0.075 |
| 5 | 15 | 0.5 | 0.125 |
| 6 | 15 | 1 | 0.25 |
| 7 | 15 | 2 | 0.5 |
| 8 | 15 | 2.5 | 0.625 |
| 9 | 15 | 5 | 1.25 |
| 10 | 15 | 10 | 2.5 |
| 11 | 15 | 20 | 5 |
| 12 | 15 | 22 | 5.5 |
| 13 | 15 | 44 | 11 |
| 14 | 30 | 56 | 28 |
| 15 | 30 | 89 | 45.075 |
This case demonstrates the feasibility and safety of rapid infliximab desensitization in a pediatric patient with severe arthritis and limited therapeutic alternatives. The clinical presentation was consistent with an immediate type I hypersensitivity reaction. Despite negative skin test results, desensitization was justified given the severity of the reaction and the need to continue the only effective therapy.
This case expands current evidence by demonstrating that a 15-step one-bag infliximab desensitization protocol, including premedication, can be safely performed in a very young pediatric patient.
The one-bag desensitization protocol represents a practical, efficient, and well-tolerated strategy that enables the continuation of first-line therapy in selected patients.5 Compared to previously reported cases, our approach differs in the younger age of the patient, the longer protocol, and the use of premedication. Further studies are needed to standardize pediatric desensitization protocols and to better define predictors of success and long-term outcomes.
This case highlights that rapid infliximab desensitization using a one-bag protocol is a useful and safe option for selected pediatric patients with no therapeutic alternatives.
CRediT authorship contribution statementMaría José Peñalver: investigation, conceptualization, formal analysis and initial draft of the manuscript; Celine Galleani: review and editing; Ruth Barranco: review and supervision; Jesús F. Crespo: review and supervision.
FundingThe study did not receive any form of funding.
The authors have no conflicts of interest to declare.



