






The lack of evidence, which would serve as a structure for a legal framework for the implementation of first aid (FA) training in the school setting, justifies this systematic review. The aim was to analyze the effectiveness of learning methods in improving FA knowledge and skills in children aged 3–12 years.
Patients and methodsSystematic review and meta-analysis. A literature search was conducted in MEDLINE, EMBASE and Web of Science. The risk of bias was assessed through the Cochrane and Joanna Briggs Institute tools. The probability of acquiring knowledge in each of the outcomes was analyzed through relative risks, which were calculated for each different type of training methodology as an estimate of effect size (ES). We used the DerSimonian and Laird random-effects method to calculate pooled ES estimates with the corresponding 95% confidence intervals (CI).
ResultsSix studies, with 1038 schoolchildren from 5 to 12 years, were included. The targeted knowledge areas included emergency recognition and call, quality of cardiopulmonary resuscitation, foreign body airway obstruction, injury, or bleeding. The ES for innovative training on emergency call (correct information), compared to control group, was 1.28 (95% CI, 1.10–1.47). On emergency call, compared to traditional training, it was 1.18 (95% CI, 1.08–1.28).
ConclusionsInnovative methodologies appeared to be equally or more effective than traditional training in teaching FA to schoolchildren aged 3–12 years, especially with age-appropriate resources. Still, the heterogeneity of the applied methodologies and the lack of robust evidence call for further studies which could elucidate the identified gaps in knowledge.
La ausencia de evidencia, que serviría como estructura para la implementación reglada del entrenamiento en primeros auxilios (PPAA) en escolares, justifica este estudio. El objetivo fue analizar la efectividad de métodos de aprendizaje en la mejora del conocimiento y habilidades en PPAA en niños de 3–12 años.
Pacientes y métodosRevisión sistemática y metaanálisis. Estrategia de búsqueda en MEDLINE, EMBASE y Web of Science. Riesgo de sesgo evaluado mediante las herramientas Cochrane y del Instituto Joanna Briggs. La probabilidad de adquirir conocimientos en cada resultado se analizó mediante riesgos relativos, que se calcularon para cada tipo de metodología docente diferente como una estimación del tamaño del efecto (ES). Se utilizó el método de efectos aleatorios de DerSimonian y Laird (intervalos de confianza -IC- 95%).
ResultadosSeis estudios, con 1038 escolares de 5–12 años, fueron incluidos. Las áreas de conocimiento abordadas incluyeron el reconocimiento y la llamada de emergencia, la calidad de la reanimación cardiopulmonar, obstrucción de vía aérea por cuerpo extraño, lesiones o hemorragias. El ES para metodologías docentes innovadoras en la llamada de emergencia (información correcta), en comparación con el grupo control, fue 1.28 (IC 95%: 1.10, 1.47). En la llamada de emergencia, en comparación con la formación tradicional, fue 1.18 (IC 95%: 1.08, 1.28)
ConclusionesLas metodologías innovadoras parecen mostrar una efectividad mayor o igual que las tradicionales en la enseñanza de PPAA a niños de 3–12 años, aunque la heterogeneidad expuesta requiere la realización de estudios futuros que permitan dilucidar las lagunas de conocimiento observadas.

In recent years, there has been an increase in the strategy of first-aid training due to the huge clinical and socioeconomic burden of the main adverse events, such as out-of-hospital cardiac arrest (OHCA) or foreign body airway obstruction (FBAO).1–3 The associated morbidity and mortality demand a continuous research effort in order to elucidate the optimal strategies to both increase survival rates and reduce the incidence of neurologic sequelae.1–3 In this sense, the European Resuscitation Council (ERC) recommends training in both FA and the basic life support (BLS) protocol, which includes the recognition of OHCA or FBAO, the performance of cardiopulmonary resuscitation (CPR), the use of an automated external defibrillator (AED), the recovery position, or bleeding control, among other skills.4–6
Since children can witness an emergency and it is during the school-age period that they develop social competences and a sense of responsibility, helping behaviors and psychomotor and cognitive skills, and in accordance with the Kids Save Lives declaration,7 launched by the ERC, several training strategies have been designed aimed at school-aged children and adolescents8–10 and the general population.11 However, despite the broad range of available training strategies, the optimal design, in terms of the selected methodology, duration, contextualization and use of technologies, has yet to be ascertained.12
The existing variability could limit the development of practical recommendations to guide FA training in the different educational stages.13,14 Therefore, it is necessary to establish effective FA learning methodologies that could help to standardize first-aid teaching in schools worldwide, guiding the development of a curriculum framework and evidence-based educational legislation.13 Thus, the aim of this study was to analyze the effectiveness of different learning methods in improving FA knowledge and skills in children aged 3–12 years.
MethodsThis systematic review and meta-analysis adhered to both the Cochrane Collaboration Handbook15 and the Preferred Reporting Items for Systematic Review and Meta-Analyses (PRISMA) guidelines (PRISMA checklist, Table S1, supplementary data).16 It was also registered in the International Prospective Register of Systematic Reviews (PROSPERO) (registration number CRD420251030243).
Search strategyWe carried out a comprehensive literature search was carried out in MEDLINE (via PubMed), EMBASE (via Scopus) and Web of Science, from their inception until April 1, 2025. The following relevant terms, including MeSH terms and free-text keywords, were combined through Boolean operators: ‘school’, ‘junior’, ‘middle’, ‘elementary’, ‘primary’, ‘child’, ‘kindergarten’, ‘teachers’, ‘cardiopulmonary resuscitation’, ‘basic life support’, ‘first aid’, ‘wound’, ‘bleeding’, ‘airway’, ‘obstruction’, ‘choking’, ‘Heimlich maneuver’, ‘emergency’, ‘treatment’, ‘early’, ‘intervention’, ‘helping’, ‘teach’, ‘train’, ‘instruct’, ‘course’, ‘learn’, ‘education’, ‘curriculum’.
In addition, we screened the references cited in the selected studies and the grey literature to identify additional sources. We contacted authors from original studies to retrieve missing information. The articles were imported and managed using Mendeley Reference Manager. The search strategy can be consulted in the supplementary material (Table S2).
Selection criteriaWe selected randomized control trials (RCTs) and quasi-experimental studies that analyzed the effectiveness of training methods in improving FA knowledge, attitudes and skills in schoolchildren aged 3–12 years. In accordance with the PICO strategy, the inclusion criteria were: (a) Population: children aged 3–12 years; (b) Intervention: training methodology aimed at improving FA knowledge, skills, attitudes and/or helping behavior; (c) Comparison: studies with a control group; and (d) Outcome: effectiveness of training methodology, which was measured by at least one of the following outcome variables: recognition of emergency, safe lateral positioning, calling 112, and management of airway obstruction.
Studies were excluded when: (a) the participants were students with disabilities; (b) the study did not include the age or academic year of the participants; (c) the design was pre-post without a control group. No language restrictions were applied.
Data extractionOriginal studies were screened to extract the following relevant data: (a) authors and publication year; (b) country; (c) design; (d) total sample and age of participants; (e) characteristics of intervention (methodological structure by groups, frequency, duration and designated teacher); (f) main measured outcomes (emergency recognition, recovery position, calling the emergency telephone number and airway obstruction); and (g) assessment tool.
Methodological quality assessmentThe risk of bias of the included RCTs was assessed through the revised Cochrane risk of bias tool for RCTs (RoB-2), which is structured in five domains that assess the potential bias stemming from the randomization process, deviations from the intended interventions, missing outcome data, measurement of the outcome and selection of reported result. The studies were classified as (i) “low risk of bias”, if all domains were classified as “low risk”, (ii) “some concerns”, if at least one domain was classified as “some concerns”, considering that any domain was judged as “high risk of bias”, and (iii) “high risk of bias”, if at least one domain was classified as high risk of bias or multiple domains were classified as “some concerns”.17
We also used the revised Joanna Briggs Institute critical appraisal tool to assess the risk of bias in quasi-experimental studies.18 This tool consists of nine items that assess the bias related to temporal precedence, selection/allocation, confounding factors, intervention, outcomes (assessment, detection and measurement), participant retention, and statistical conclusion validity.
Two reviewers (C.B-M and C.J-S) conducted the search, study selection, data extraction, and methodological quality assessment independently. Disagreements were solved by consensus, and a third researcher was consulted when consensus could not be reached (S.M-I).
Data analysisThe probability of acquiring knowledge in each outcome was assessed through relative risks, which were calculated for each different type of training methodology as an estimate of effect size (ES). We used the DerSimonian and Laird random-effects method19 to compute pooled ES estimates with their respective 95% confidence intervals (CIs). The heterogeneity across studies was evaluated using the I2 statistic, which was interpreted as not important (0%–40%), moderate (30%–60%), substantial (50%–90%) and considerable (75%–100%), also considering the corresponding P values.20
The ES was calculated using unadjusted models reported by the original articles, comparing the acquisition of knowledge for each training outcome in participants who had received innovative training (reference) versus, in one hand, controls who had not received any training and, on the other hand, those who had been trained with traditional methodology. Innovative training was defined as the use of teaching resources based on strategies tailored to the age of the participants, incorporating recreational, audiovisual, or game-based elements, and differing from the traditional lecture-style class, defined as the presentation of theory with or without practical exercises on a mannequin. When a study included two or more innovative methodologies, each one was included in the meta-analysis and compared with the control group independently. Positive ES values indicate a higher probability of knowledge acquisition in favor of innovative training compared to traditional methodology and no training.
We carried out sensitivity analyses by removing the included studies from the pooled analysis one by one, with the aim of assessing the robustness of the summary estimates and determining whether any single study accounted for a large proportion of the variance. In addition, we assessed publication bias by means of a funnel plot, according to the method proposed by Egger et al.21
All the analyses were conducted using the Stata SE software, version 17 (StataCorp).
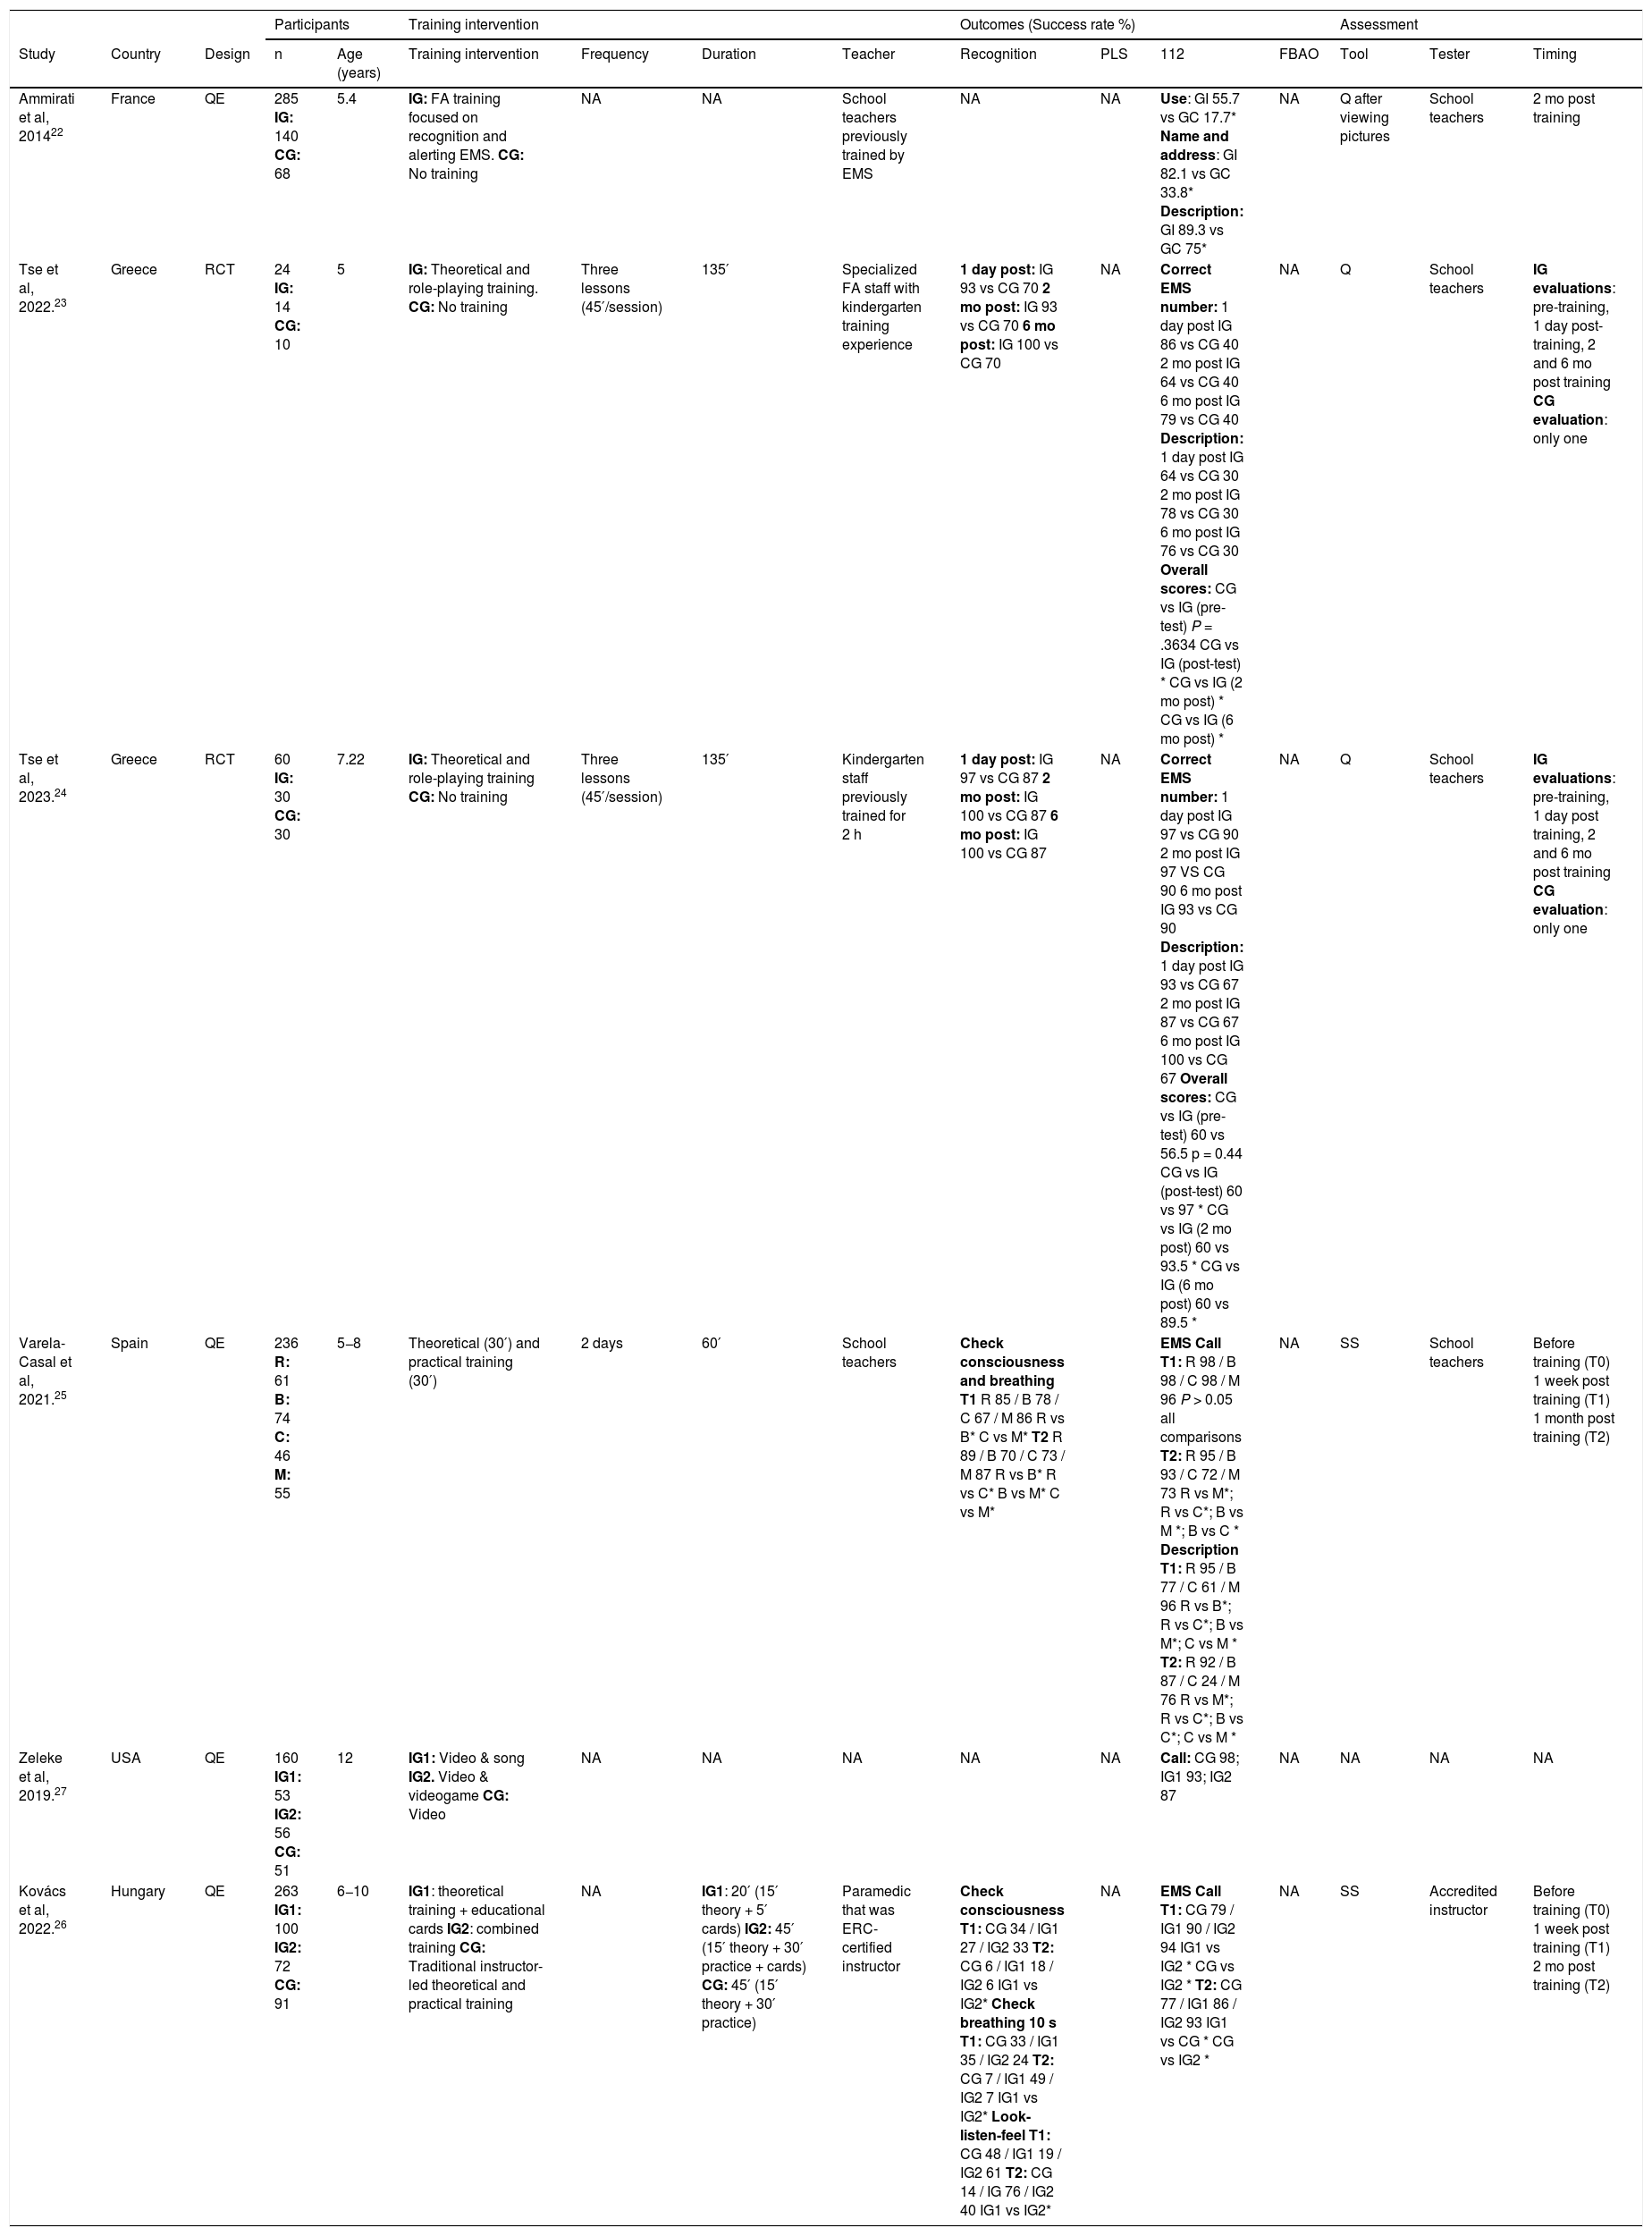
ResultsSix studies were included in this systematic review and meta-analysis (Fig. 1). Table 1 summarizes the main characteristics of these studies. All were published between 2014 and 2023, and they were conducted in France,22 Greece,23,24 Spain,25 Hungary26 and the United States.27 The total sample size across the six studies was 1038 schoolchildren. In two studies,23,24 the sample included fewer than 150 participants, and individual study samples ranged from 2423 to 285 children.22 Regarding participant characteristics, the age of the schoolchildren ranged from 5 years22,23,25 to 12 years.27 We did not find any studies including participants aged 3–5 years. Of the included studies, four had a quasi-experimental design,22,25,27 and two applied randomization. All studies included a control group, in 50% of the studies, the intervention was compared with a single intervention group,22,23,26 while the remaining studies made comparisons with two groups24,27 or three groups.25

Main characteristics of included studies.
| Participants | Training intervention | Outcomes (Success rate %) | Assessment | ||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Study | Country | Design | n | Age (years) | Training intervention | Frequency | Duration | Teacher | Recognition | PLS | 112 | FBAO | Tool | Tester | Timing |
| Ammirati et al, 201422 | France | QE | 285 IG: 140 CG: 68 | 5.4 | IG: FA training focused on recognition and alerting EMS. CG: No training | NA | NA | School teachers previously trained by EMS | NA | NA | Use: GI 55.7 vs GC 17.7* Name and address: GI 82.1 vs GC 33.8* Description: GI 89.3 vs GC 75* | NA | Q after viewing pictures | School teachers | 2 mo post training |
| Tse et al, 2022.23 | Greece | RCT | 24 IG: 14 CG: 10 | 5 | IG: Theoretical and role-playing training. CG: No training | Three lessons (45′/session) | 135′ | Specialized FA staff with kindergarten training experience | 1 day post: IG 93 vs CG 70 2 mo post: IG 93 vs CG 70 6 mo post: IG 100 vs CG 70 | NA | Correct EMS number: 1 day post IG 86 vs CG 40 2 mo post IG 64 vs CG 40 6 mo post IG 79 vs CG 40 Description: 1 day post IG 64 vs CG 30 2 mo post IG 78 vs CG 30 6 mo post IG 76 vs CG 30 Overall scores: CG vs IG (pre-test) P = .3634 CG vs IG (post-test) * CG vs IG (2 mo post) * CG vs IG (6 mo post) * | NA | Q | School teachers | IG evaluations: pre-training, 1 day post-training, 2 and 6 mo post training CG evaluation: only one |
| Tse et al, 2023.24 | Greece | RCT | 60 IG: 30 CG: 30 | 7.22 | IG: Theoretical and role-playing training CG: No training | Three lessons (45′/session) | 135′ | Kindergarten staff previously trained for 2 h | 1 day post: IG 97 vs CG 87 2 mo post: IG 100 vs CG 87 6 mo post: IG 100 vs CG 87 | NA | Correct EMS number: 1 day post IG 97 vs CG 90 2 mo post IG 97 VS CG 90 6 mo post IG 93 vs CG 90 Description: 1 day post IG 93 vs CG 67 2 mo post IG 87 vs CG 67 6 mo post IG 100 vs CG 67 Overall scores: CG vs IG (pre-test) 60 vs 56.5 p = 0.44 CG vs IG (post-test) 60 vs 97 * CG vs IG (2 mo post) 60 vs 93.5 * CG vs IG (6 mo post) 60 vs 89.5 * | NA | Q | School teachers | IG evaluations: pre-training, 1 day post training, 2 and 6 mo post training CG evaluation: only one |
| Varela-Casal et al, 2021.25 | Spain | QE | 236 R: 61 B: 74 C: 46 M: 55 | 5−8 | Theoretical (30′) and practical training (30′) | 2 days | 60′ | School teachers | Check consciousness and breathing T1 R 85 / B 78 / C 67 / M 86 R vs B* C vs M* T2 R 89 / B 70 / C 73 / M 87 R vs B* R vs C* B vs M* C vs M* | EMS Call T1: R 98 / B 98 / C 98 / M 96 P > 0.05 all comparisons T2: R 95 / B 93 / C 72 / M 73 R vs M*; R vs C*; B vs M *; B vs C * Description T1: R 95 / B 77 / C 61 / M 96 R vs B*; R vs C*; B vs M*; C vs M * T2: R 92 / B 87 / C 24 / M 76 R vs M*; R vs C*; B vs C*; C vs M * | NA | SS | School teachers | Before training (T0) 1 week post training (T1) 1 month post training (T2) | |
| Zeleke et al, 2019.27 | USA | QE | 160 IG1: 53 IG2: 56 CG: 51 | 12 | IG1: Video & song IG2. Video & videogame CG: Video | NA | NA | NA | NA | NA | Call: CG 98; IG1 93; IG2 87 | NA | NA | NA | NA |
| Kovács et al, 2022.26 | Hungary | QE | 263 IG1: 100 IG2: 72 CG: 91 | 6−10 | IG1: theoretical training + educational cards IG2: combined training CG: Traditional instructor-led theoretical and practical training | NA | IG1: 20′ (15′ theory + 5′ cards) IG2: 45′ (15′ theory + 30′ practice + cards) CG: 45′ (15′ theory + 30′ practice) | Paramedic that was ERC-certified instructor | Check consciousness T1: CG 34 / IG1 27 / IG2 33 T2: CG 6 / IG1 18 / IG2 6 IG1 vs IG2* Check breathing 10 s T1: CG 33 / IG1 35 / IG2 24 T2: CG 7 / IG1 49 / IG2 7 IG1 vs IG2* Look-listen-feel T1: CG 48 / IG1 19 / IG2 61 T2: CG 14 / IG 76 / IG2 40 IG1 vs IG2* | NA | EMS Call T1: CG 79 / IG1 90 / IG2 94 IG1 vs IG2 * CG vs IG2 * T2: CG 77 / IG1 86 / IG2 93 IG1 vs CG * CG vs IG2 * | NA | SS | Accredited instructor | Before training (T0) 1 week post training (T1) 2 mo post training (T2) |
Abbreviations: B, endless book; C, cuddly; EMS, emergency medical services; ERC, European Resuscitation Council; FA, first aid; M, manikin; mo, months; NA, not available; Q, questionnaire; QE, quasi-experimental; R, Rescube; RCT, randomized control trial; SS, simulation scenario.
*Statistically significant association (P < .05).
Of the six studies, three compared different educational resources,25–27 while the remaining three analyzed specific methodological aspects.22–24 The targeted knowledge areas included: emergency recognition,23,25 emergency call procedures,22–26 CPR sequence,25–27 quality of chest compressions22 and other FA skills such as the management of FBAO, injury, or bleeding.23,24 In terms of specific methodological characteristics, only three studies reported detailed information. The duration of the interventions ranged from a single 45-minute session26 to three 45-minute sessions, totaling 135 min.23,24 Instruction was provided either by schoolteachers22,24 or by professional instructors, such as paramedics26 or certified FA specialists.27 The assessment methods included knowledge questionnaires23,24 and practical skill evaluations.22,25–27 Half of the studies implemented both pre- and post-intervention assessments,23,24,26 and the post-intervention assessments were performed at different times during the follow-up: one month,25,26 two months,23,24 six months,23,24 or an unspecified time point.22
Methodological quality assessmentAccording to the RoB-2 tool, the overall risk of bias in the two RCTs included in this systematic review was classified as “high” for one and “some concerns” for the other.23,24 Both studies were classified as “low risk” of bias in the domain concerning missing outcome data (Table S3, Figure S1). For the quasi-experimental studies, the mean overall agreement of the items of the revised Joanna Briggs Institute critical appraisal tool was 58.35%, ranging from 22.2%27 to 77.8%.25,26 All quasi-experimental studies fulfilled both the temporal precedence and selection/allocation items (Table S4).
Meta-analysesThe ES of innovative training compared to control for the emergency call (correct information), was 1.28 (95% CI, 1.10–1.47; P = .680; I2 = 0.0%) (Fig. 2B). The estimated ES of innovative training compared to traditional training for the emergency call was 1.18 (95% CI, 1.08–1.28; P = .263; I2 = 23.7%) (Fig. 2C). We did not find significant differences in the ES for the emergency call (Fig. 2A) or, compared to traditional training methods, in the emergency call (correct information) (Fig. 2D) and emergency recognition (Fig. 2E).
Sensitivity analyses and publication bias
The sensitivity analyses showed a difference in the pooled ES estimates for emergency call (correct information) (ES = 1.32; 95% CI, 0.94–1.69) after excluding the study by Ammirati et al.,22 which had the largest sample size (Supplemental material).
Funnel plot asymmetry (supplemental material, Tables S5-S9, Figures S2-S6) and the Egger tests (P < .05) indicated the presence of publication bias in the models.
DiscussionThis systematic review with meta-analysis synthesizes the available evidence on the methodologies and teaching resources used for FA training in schoolchildren aged 3–12 years. We analyzed six studies that explored the knowledge and skills acquired by schoolchildren and comparing training methods and/or resources, depending on the study. The findings showed increased effectiveness with the use of specific and age-appropriate materials, compared to other resources, as well as improvement in knowledge and skills when schoolchildren received training. We ought to highlight the relevance of the analysis of the methodological design of the studies included in the review, as it revealed critical aspects that had to be taken into account in the interpretation of results. Notwithstanding, all studies included a control group, randomization was limited and, in some cases, the authors did not clearly describe the study protocol. In this sense, the methodological quality of the studies calls for caution in the interpretation of their findings, underscoring the need for further research to elucidate the controversial aspects.
The implementation of FA training programs for school-aged children has become particularly relevant after the promotion of the international Kids Save Lives initiative by the ERC in 2015.28 Since then, the evidence has grown substantially, highlighting the importance of including mandatory contents in school curricula,29 whilst De Buck et al.14 suggested developing a program for schoolchildren with contents and competencies adapted for each age group. Despite this, the inclusion of these contents in school curricula does not guarantee their actual teaching, appropriateness or effectiveness. Thus, some countries, like Spain, have incorporated first aid training in its educational legislation, but without necessarily following evidence-based recommendations.13
Despite some heterogeneity, the analyzed studies mostly addressed key contents that were appropriate for the age of the students. The studies included in this review focused on contents suggested by De Buck et al.,14 such as the activation of the emergency system, which are taught in the early stages of education.22–26 Others studies included topics like the recovery position, the CPR sequence and the management of FBAO, wounds or bleeding in early education cycles.23,24 The implementation of BLS and FA training within the school curriculum, as suggested by the International Liaison Committee on Resuscitation (ILCOR),29 with topics and competencies adapted to the physical and cognitive development of students, will enable the transition towards a systematic and structured learning model.
One of the main findings of our review is the remarkable heterogeneity in the objectives of the studies, although the assessed contents were the same. Child-specific and child-friendly learning resources that could be manipulated,25 low-cost materials as cards,26 and combinations of videos with songs and video games27 were compared with conventional CPR training, with evidence of improvements in learning25 or at least noninferior outcomes.26 Studies also compared learning outcomes in schoolchildren trained with role-playing,24 outcomes in trained versus untrained schoolchildren,22 our outcomes according to the professional that trained the children.23
The assessment of FA learning in the pediatric population raises major methodological challenges. The analyzed studies used a variety of questionnaires applied at different timepoints to assess knowledge and practical skills through simulation scenarios. In this regard, one the models most widely used for assessment of learning outcomes in the health sciences is the Miller’s Pyramid, which classifies competencies in four hierarchical levels: (1) knows, (2) knows how, (3) shows and (4) does.30 However, there was heterogeneity in the levels used in the studies included in our review. Thus, 66.6% of the studies22,25–27 assessed at level 3 (shows), and 33.3%23,24 at level 1 (knows).
Regarding the timing of assessment, we found significant heterogeneity in the assessment timepoints, especially in the median- and long-term follow-up.10,31 Although most of the studies only assessed learning outcomes immediately after intervention, there is insufficient evidence to determine the optimal timing for assessing learning outcomes in this population. Some researchers suggest that retention of knowledge and practical skills wanes over the years, and that the age of the child could influence this decline in performance.10
LimitationsThis systematic review and meta-analysis provides an updated and relevant synthesis of the available evidence, although it has some limitations that must be considered in interpreting its results: (i) the limitations inherent to the development of systematic reviews and meta-analyses, such as publication and selection bias and the limited information reported by the original studies. The number of included studies was small, which could limit the generalization of the findings and reduce the statistical power of the quantitative analyses. Additionally, the statistical power of the Egger test was limited due to the small number of studies. Although the literature search was exhaustive and no language restriction was applied, the possibility of publication bias could not be ruled out; (ii) we found no studies that assessed participants aged 3–5 years, so further studies addressing the impact of different methodologies on this age group are necessary; (iii) the included studies did not report the data disaggregated by sex, which limits the possibility of conducting analyses that incorporate a gender perspective (iv) there was substantial methodological heterogeneity between the studies. The differences in the methodological design, the instructor profile and the methods for assessment limit direct comparisons between studies; (v) a lot of studies did not report medium and long-term outcomes, so that the retention of the acquired knowledge and skills was not evaluated. Moreover, in some cases, the assessment instruments lacked previous feasibility and validity studies, which could compromise the internal validity of the results. These limitations underscore the need of further studies with robust designs, standardized measures and longitudinal follow-up to allow progress towards effective, sustainable and adapted FA training in schoolchildren (Table S10).
ConclusionThere is preliminary evidence suggesting that methodologies and resources used for FA training in schoolchildren aged 3–12 years are effective in improving knowledge and the correct execution of technical skills, particularly when the content and resources are innovative and age-appropriate. Innovative methodologies could be as effective as traditional approaches, and sometimes even more. The variety of methodologies used for instruction and assessment demands further structured studies to elucidate the knowledge gaps identified in this study.
AuthorshipSantiago Martínez-Isasi and Carlos Berlanga-Macías: study conceptualization, methodology, writing of original draft. Cristina Jorge-Soto and José Alberto Martínez-Hortelano: data curation, software, formal analysis, validation. Santiago Martínez-Isasi, Carlos Berlanga Macías, and Cristina Jorge-Soto: supervision. Lidia Lucas-de la Cruz, Montserrat Solera-Martínez and Cristina Jorge-Soto: visualization, investigation, writing, reviewing and editing. All authors have approved the final version of the manuscript as submitted and assume responsibility for all aspects of the work.
FundingThis study was funded by the Department of Education, Culture, and Sports of the Regional Government of Castilla-La Mancha and the European Regional Development Fund (ERDF) (SBPLY/23/180225/000060). The funding source was not involved in the meta-analysis.
Data availabilityThe data that has been used is confidential.
Data will be made available on request.
The authors declare that they have no conflicts of interest.
The authors thank Laura García Olmedo, worker of the Junta de Comunidades de Castilla-La Mancha for her enthusiasm and collaboration in revising the English language during the writing of the manuscript.
The following are Supplementary data to this article:




